Categories
Hospital Finances Medical Economics

The Disadvantage Of Medicare Advantage Plans

Three events happened in the past week that should be concerning to all physicians and hospitals that take care of patients on Medicare Advantage Plans. First, the U.S. Congress Joint Economic Committee issued a brief concluding that Medicare Advantage Plans overcharge Medicare and cost 120% of traditional Medicare per enrollee. Second, Aetna was fined $117 million because of Medicare Advantage Plan false claims. And third, a study in JAMA found that in 2026, 10% of enrollees in Medicare Advantage Plans are being dropped from coverage. These three events will have a direct impact on medical practices.

When a U.S. citizen turns age 65, they have a choice – either enroll in traditional Medicare or enroll in a Medicare Advantage Plan. Traditional Medicare includes Part A and Part B. Part A is free and funded by payroll taxes. Seniors pay a monthly premium for Part B with the rest of Part B funded by federal income tax. Most people with traditional Medicare will purchase a separate Medigap policy through a commercial health insurance company that helps cover deductibles, co-pays, and other healthcare expenses not covered by traditional Medicare. Additionally, most people with traditional Medicare will purchase a Medicare Part D policy to cover outpatient medications that are not covered by traditional Medicare.

A Medicare Advantage Plan (also known as Medicare Part C), is an all-inclusive health insurance policy sold by commercial insurance companies that bundles Medicare Part A, Medicare Part B, Medigap coverage, and usually a Medicare Part D plan. In addition, many Medicare Advantage Plans also provide perks that are not available to seniors on traditional Medicare such as gym memberships, dental insurance, or vision insurance. Medicare Advantage Plans are usually less expensive than the combined cost of traditional Medicare Part B plus a Medigap plan plus a Medicare Part D plan. For this reason, the Medicare Advantage Plans are very popular. Currently, 54% of Medicare beneficiaries are enrolled in a Medicare Advantage Plan and only 46% are enrolled in traditional Medicare.

Medicare Advantage Plans are inexpensive because commercial insurance companies have tactics to control costs that Medicare lacks. These include:

  • Prior authorization. By requiring many services, procedures, and referrals to get prior authorization, insurance companies can impose strict authorization criteria that must be met before a physician or hospital can perform a procedure or service. This is done under the guise of preventing unnecessary procedures and services. However, many insurance companies have very strict criteria that can create a barrier for procedures or services that are actually needed by patients. In addition, the prior authorization process is onerous, requiring time and expense for doctors and hospitals to call the insurance company and negotiate with an insurance representative. Because this is such a hassle, many physicians find the path of least resistance to be to forgo a certain test or procedure rather than have to deal with another tedious prior authorization, even if they believe that the test or procedure is needed for optimal care of the patient.
  • Denials. Frequently, there is no time to get prior authorization, for example, for an emergency hospital admission or for an urgently needed outpatient CT scan. In these situations, the Medicare Advantage Plan insurance company can retrospectively deny payment for the hospital admission or CT scan if the insurance company decides that there was insufficient indication for that hospital admission or CT scan. Physicians and hospitals can appeal those denials but the appeals require a great deal of time and paperwork. As a result, many of these services and procedures are written off because of the cost and effort necessary to appeal. Thirty years ago, a claims worker for one of the major health insurance companies told me that their company’s policy was to randomly deny every 20th claim because many physicians and hospitals would not bother to appeal them, ultimately saving the insurance company millions of dollars every year.
  • Provider networks. With traditional Medicare, a beneficiary can see any physician or hospital in the country that takes Medicare. Because nearly all doctors and hospitals that provide care to adults accept Medicare, this means that the person with traditional Medicare can see any doctor he or she wants. Each Medicare Advantage Plan insurance company will have its own limited number of in-network doctors and hospitals. Beneficiaries have to pay steep extra costs to see a doctor who is out-of-network or go to a hospital that is out-of-network. This is sometimes unavoidable, for example, if a person needs a surgery done by an in-network surgeon but the anesthesiologist is out-of-network. In the past, insurance companies had no motivation to keep their list of in-network physicians current. Indeed, they were actually incentivized to let those lists become out of date with “ghost doctors”, physicians who had retired or moved and were no longer practicing in the area. By making it harder for enrollees to find a doctor in a particular specialty, it reduced the chances that the enrollee would eventually see a specialist and thus avoided having to pay for expensive services or procedures. A recent class action lawsuit has resulted in Medicare Advantage Plans now being required to ensure that their lists of in-network physicians is current.
  • Favorable selection. Since Medicare Part B pays the Medicare Advantage Plan commercial insurance company on a per-enrollee basis, the more healthy enrollees the insurance company can attract, the less that insurance company will have to pay for healthcare services and procedures. The average amount paid by Medicare Part B this year is $9,739 per beneficiary. If a commercial insurance company can attract a group of enrollees that will on average generate less than $9,739 in healthcare expenses per year, then the insurance company stands to make a profit. There are several tactics that insurance companies use to preferentially attract healthier patients. Zero premium Medicare Advantage Plans often appeal to healthier seniors who do not require frequent, costly healthcare. Perks such as gym memberships attract more active, healthier seniors. Targeted advertising can reach seniors who are likely to have lower healthcare costs – this could include targeting geographic areas or demographic groups that are likely to have lower healthcare requirements. Provider network design can emphasize primary care providers with limited access to specialists, thus selectively appealing to seniors with no medical conditions requiring specialist care. The bottom line is that the more healthy people a Medicare Advantage Plan can enroll, the more profitable that plan will be for the commercial insurance company.
  • Upcoding. Medicare pays commercial insurance companies administrating Medicare Advantage Plans based on the number of enrollees and how medically complex those enrollees are. The more medical problems an enrollee has, the more Medicare will pay the commercial insurance company for that particular enrollee. Therefore, the insurance companies are incentivized to exaggerate the number and severity of medical illnesses for every enrollee. When I first enrolled in a Medicare Advantage Plan, the insurance company kept wanting to send out a nurse to my home to do a “wellness visit”. That nurse’s real job was to find and document as many medical conditions as possible. If the nurse finds that the enrollee’s blood pressure is 1 mm Hg above normal, the insurance company can claim that the enrollee has hypertension and charge Medicare more. If the nurse weighs the enrollee with all of their clothes and shoes on and the enrollee’s weight is 1 pound above the threshold for morbid obesity, then the insurance company can document morbid obesity and charge Medicare more. Needless to say, I refused the wellness visits.

On March 10, 2026, the Joint Economic Committee of the U.S. Congress issued a brief stating that Medicare Advantage Plans are overpaid, resulting in an increase in Medicare premiums for all Medicare beneficiaries. The original intention of the Medicare Advantage Plans was to decrease cost of care by reducing unnecessary medical services and procedures and by substituting private insurance company efficiency for Medicare government bureaucratic inefficiency. The original projection was that Medicare Advantage would cost 95% of what traditional Medicare costs per beneficiary. The reality is that Medicare Advantage costs 120% of what traditional Medicare costs per beneficiary. In other words, rather than saving money, Medicare Advantage Plans are costing Americans more money. MedPAC estimates that this year, commercial insurance companies will be over-charging Medicare by $76 billion because of upcoding. This ends up costing Medicare beneficiaries more in Part B premiums and costing American taxpayers more in income taxes.

Medicare Part B covers outpatient healthcare services and doctors’ charges. By statute, 25% of Medicare Part B is covered by monthly Medicare premiums charged to all Medicare enrollees (both traditional Medicare and Medicare Advantage Plan enrollees). The annual Medicare Part B premiums are based on income with $2,435 per year for most Medicare enrollees. Higher income enrollees pay as much as $8,279 per year. The other 75% of the cost of Medicare Part B is covered by income taxes paid by working Americans. Because Medicare Part B pays the Medicare Advantage Plan insurance companies on a per-enrollee basis, the more the insurance companies charge per-enrollee, the more Medicare Part B has to pay. This increases the overall cost of Medicare Part B and that increase in cost results in higher Medicare Part B premiums for enrollees and more money from federal income taxes.

Over the next 9 years, Medicare Part B premiums are projected to double to approximately $5,000 per year in 2035 for most Americans. Of this amount, $450 will result from Medicare Advantage Plan overpayments. Commercial health insurance companies are for-profit corporations and as such, they are incentivized to charge as much money as possible – because the Medicare Advantage Plans are paid by Medicare, they are incentivized to charge Medicare (i.e., the federal government) as much money as possible. The temptation to upcode is just too great.

Aetna is owned by CVS Health and has the 4th largest number of Medicare Advantage Plan enrollees (after UnitedHealthcare, Humana, and Blue Cross/Blue Shield affiliates). The U.S. Attorney’s office in Philadelphia announced last week that Aetna agreed to pay $117.7 million to settle federal charges of false claims of billing. The allegation is that Aetna added diagnosis codes in an attempt to upcode Medicare Advantage Plan enrollees to make them appear to be sicker than they actually are. $11.5 million of the penalty went to a whistleblower who alleged that Aetna added inaccurate diagnosis codes for morbid obesity.

A study published in JAMA last week found that 10% of Americans enrolled in Medicare Advantage Plans were forcibly disenrolled in 2026. Disenrollment happens when a commercial insurance company stops offering its Medicare Advantage Plan in a certain geographic location. The main reason that a Medicare Advantage Plan leaves a local market is financial – they lose money in that particular market area. Prior to 2025, the annual disenrollement was less than 1% per year. In 2025, disenrollment increased to 6.9% and in 2026, increased further to 10.0%.

Disenrollees were more likely to have been in smaller Medicare Advantage Plans, in plans with a lower Medicare star rating, and in rural areas. Seven states had very high disenrollment rates (>40%): Vermont, New Hampshire, Maryland, North Dakota, South Dakota, Wyoming, and Idaho. Vermont is particularly notable with 92.2% of Medicare Advantage Plan enrollees in Vermont being disenrolled in 2006.

The good news is that most of these Medicare Advantage Plan enrollees were able to switch to a different Medicare Advantage Plan insurance company. However, this often results in patients needing to switch doctors when their previous doctor is not in-network for their new Medicare Advantage Plan. This can also affect hospitals that are not in-network for the new plan. Even for those doctors and hospitals that remain in-network for their patient’s new Medicare Advantage Plan, it can mean re-submitting prior authorization applications for upcoming services or procedures.

The recent uptick in Medicare Advantage Plan disenrollments is a sign that commercial insurance companies are finding some areas of the United States to be unprofitable. For disenrollees, the only option to enrolling in a different Medicare Advantage Plan is to go back to traditional Medicare. But switching to traditional Medicare can be fraught with hazard.

When a person turns 65-years-old, that person can choose to either enroll in traditional Medicare or a Medicare Advantage Plan. For a Medicare beneficiary who is already enrolled in a Medicare Advantage Plan, there are two times each year that they can change back to traditional Medicare: either during the Medicare Open Enrollment period (October 15 – December 7) or during the Medicare Advantage Open Enrollment period (January 1 – March 31).

But there is a catch. Most people on traditional Medicare will also have a Medigap policy to cover the out of pocket healthcare expenses not covered by traditional Medicare. When you are 65 and first enroll in Medicare, commercial insurance companies offering Medigap policies have to accept everyone, regardless of pre-existing medical conditions. But once you are enrolled in a Medicare Advantage Plan, if you go back to traditional Medicare, the insurance company can deny you a Medigap policy if you have pre-existing conditions such as cancer, diabetes, or heart disease. In other words, if you have a significant pre-existing medical condition, once you go on a Medicare Advantage Plan, you realistically cannot go back to traditional Medicare because you won’t be able to get a Medigap policy. And if a Medicare Advantage Plan has upcoded diagnoses in your insurance record, you may find yourself ineligible for a Medigap policy because the number or severity of your medical problems was exaggerated by the Medicare Advantage Plan insurance company.

With greater public awareness of the practice of upcoding by Medicare Advantage Plans, we can expect more whistleblowers and more prosecutions such as occurred last week with Aetna. If commercial insurance companies dial back their upcoding efforts, they will need to look to other ways of ensuring Medicare Advantage Plan profitability. That is likely to mean ramping up their prior authorization requirements, further restricting the number of in-network providers, and increasing denials.

In anticipation of this, doctors should ensure that their chart documentation is complete and accurate to reduce retrospective denials. We should be sure that the diagnoses associated with test and procedure orders are correct and complete to reduce prior authorization phone calls. And we should check every patient’s current insurance at every visit in order to avoid denials for being unexpectedly out-of-network.

Hospitals should ensure that their revenue cycle departments are fully staffed with personnel to handle prior authorizations and denials. There should be robust processes in place to distinguish observation hospital stays versus inpatient admissions. And patients’ current insurance should be checked at every visit since the prior authorization for an elective hip surgery obtained in March may not be honored when the surgery is actually performed in April if the patient had to switch to a different Medicare Advantage Plan in the interim.

We should have all seen this coming. The Medicare Advantage Plans were supposed to reduce healthcare costs by substituting the streamlined efficiency of private industry for the bloated inefficiency of the federal government’s Medicare operations. But it turns out that Medicare is actually more cost-effective than commercial insurance companies because unlike UnitedHealthcare for example, Medicare isn’t required to turn a profit each year, didn’t have to pay a CEO $26 million in salary last year, and didn’t have to pay shareholders $8 billion in dividends last year. When it comes to making a profit, businesses will always find a way. Even if that way results in higher Medicare Part B premiums to all seniors and increased income tax burden on all American taxpayers.

March 17, 2026

Categories
Medical Economics

American Healthcare Financing: where the money came from and where it went

This month, the Center for Medicare and Medicaid Services (CMS) released the most recent report on U.S. healthcare financing. This covers calendar year 2024 and shows us how we pay for healthcare in the United States. Additionally, CMS has projected how we will be spending our healthcare dollars over the next 8 years.

Americans spend more on healthcare than citizens of any other country. In 2024, we spent $15,474 per person on healthcare. That works out to 18.1% of the country’s entire gross domestic product! Not only is healthcare more expensive in the U.S., but it has also been increasing at a faster pace than any other country. The graph below based on data from the OECD shows expenditures on healthcare as a percentage of GDP from 1980 to 2021. United States in the green line shows that our healthcare expenditures are increasing much faster than any other developed country.

The CMS data shows that healthcare expenditures increase dramatically with age. In 2020, healthcare for those under age 18 only costed an average of $4,217 per person but for those over age 85, the average healthcare expenditures were $35,995 per person. Importantly, the most recent CMS data on age-related expenditures is from 6 years ago, in 2020. In that year, the average U.S. per capita healthcare expenditure was $12,637 and increased 22% by 2024. Based on the recent 7.2% annual healthcare cost inflation rate, we can estimate that in 2025, the cost of healthcare for Americans over age 85 was approximately $46,500 per year. This is roughly twice the amount of the average retired American’s annual Social Security benefit.

So, why is it that Americans spend so much for healthcare compared to the rest of the world? Inevitably, any discussion about U.S. healthcare finances leads to finger pointing at individual healthcare costs: drug costs, hospital charges, physician charge, nursing home costs, etc. But the reality is that we pay a lot for all of the various healthcare costs. The figure below from the recent CMS report shows how Americans spent money on healthcare in 2024.

The largest expense was for hospital care at 31% of total healthcare expenditures or $1.64 trillion. The next largest was for physician and other clinical services at 21% or $1.11 trillion. Prescription drugs accounted for 9% of healthcare expenditures and nursing home expenditures only accounted for 4% of the total. In contrast, 7% of healthcare expenditures went toward the administrative costs of insurance companies and Medicare – that was a total of $370 billion in 2024.

The types of healthcare expenditures that Americans pay for has not changed appreciably over the past 24 years. The table below shows the percent of types of healthcare expenditures on a per capita basis. There has only been a 1 – 2 percentage point change in each of these categories between 2000 and 2024. In other words, all types of healthcare services and products have increased similarly since 2000.

Private health insurance companies were the largest source of healthcare funding at 31%, followed by Medicare at 21% and Medicaid at 17%. Out of pocket expenditures accounted for 11% which works out to an average out of pocket cost per American of $1,700.

The CMS report also includes projections of healthcare expenditures through 2033. The report anticipates a per capita 4.7% to 5.2% annual increase in healthcare expenditures. As a result, in 2033, the average American’s healthcare expenditure will be $24,200. That equates to an increase to 20.3% of the nation’s gross domestic product in 2033.

CMS projects that all types of healthcare expenditures will increase with hospital care continuing to be the largest healthcare expenditure in 2033.

Not all types of healthcare expenditures are projected to increase at the same rate, however. The greatest increase between 2025 and 2033 is projected to be in home health (71% increase) and private insurance company administrative costs (69%). At the other end of the spectrum, public health is only projected to increase by 21% from 2025 to 2033. In contrast, the Congressional Budget Office projects that the consumer price index will increase by 19.8% from 2025 to 2033, indicating that all types of healthcare costs will substantially outpace the general inflation rate over the next 8 years.

One implication of these projections is that home healthcare will be a growth opportunity over the next 8 years and hospitals would be well advised to invest in home health delivery.

The other implication is that commercial health insurance company administrative cost increases will outpace increases in other healthcare expenditures and increase nearly twice as much as governmental insurance administrative costs, such as Medicare. There are several reasons why this will likely occur. With the steady growth in Medicare Advantage Plans (Medicare Part C), commercial insurance companies will increasingly assume administrative costs previously incurred by Medicare when in the past, a majority of Medicare beneficiaries were covered under traditional Medicare, rather than Medicare Part C. In addition, insurance company CEO pay has increased more than other healthcare costs with an increase of 27% between 2023 and 2024 alone. Collectively, the CEOs of the six major national health plans earned $159.4 million in total compensation in 2024.

However, this also indicates a financial vulnerability of American healthcare – dozens of individual commercial health insurance companies all have redundant administrative costs, such as employment of company-specific actuaries, CEOs, underwriters, contract analysts, and sales staff. From a macro national healthcare economic standpoint, these redundant costs add considerably to what Americans pay for healthcare and represent opportunities for policy changes that could lower future costs.

From all of the above data, it is clear that there is no simple way to reign in U.S. healthcare costs. We cannot reduce per capita healthcare expenditures by simply reducing prescription drug costs. Nor by simply reducing physician reimbursement. Nor by reducing payments to nursing homes. The problem with the cost of American healthcare is that all types of healthcare expenditures are increasing and they are all increasing faster than the general inflation rate.

But there is reason to hope. Other countries have been able to provide as good or better healthcare to their citizens for a fraction of the cost in the United States. And although healthcare expenditures as a percent of GDP are increasing in all countries, all other developed countries have been able to control the rate of increase in expenditures more effectively than the U.S. If other countries have been able to do it, we should be able to as well.

January 25, 2026

Categories
Medical Economics Outpatient Practice

Telemedicine Ends For Most Americans In January 2026 (…maybe)

Until 5 years ago, telemedicine was only reimbursed for patients in rural locations where long-distance travel for patients to get to a doctor’s office was difficult. Medicare required these patients to go to a rural health facility and the telemedicine encounter with a remote physician would then be conduced with the patient physically at the rural health facility. At the beginning of the COVID pandemic, Congress expanded telemedicine in order to allow patients to continue to receive outpatient services without having to physically go to a doctor’s office. This protected patients from exposure to contagious diseases in the waiting room, protected medical staff from exposure to contagious patients, and helped conserve personal protective equipment (PPE). The expansion of telemedicine was supposed to be a temporary measure with the intention that it would go away as the pandemic receded. But it turns out that both patients and doctors like telemedicine and now the onus is on Congress to make telemedicine permanent.

The temporary telemedicine expansion was set to expire on October 1, 2025. It had been anticipated that Congress would pass legislation to extend telemedicine beyond that date but with the government shutdown, Congress did not meet to pass any new legislation. Thus, as October 1st came and went, physicians largely stopped providing telemedicine because Medicare no longer paid for it. When the government shutdown ended, Congress passed a stopgap legislation to temporarily continue telemedicine coverage by Medicare until January 30, 2026. Without new legislation, telemedicine coverage will revert to the pre-pandemic restrictions of rural-only coverage.

At the beginning of the COVID pandemic, telemedicine was hugely popular with both patients and physicians. Office staff revised their workflows with many staff able to work from home. Physicians added cameras to their computer workstations to permit video conferencing with patients. Clinic parking lots became empty. The percent of Medicare patients using telemedicine shot up with 47% of them having a telemedicine visit in the second quarter of 2020 alone. As the pandemic waned, use of telemedicine fell but even this year, about 12% of Medicare patients have a telemedicine visit in any given quarter as shown from a graph below from a November 2025 CMS report.

Race and ethnicity. CMS reports that Hispanic and Asian Americans on Medicare are most likely to currently use telemedicine whereas White and Native Americans are least likely to use telemedicine. A household pulse survey by the U.S. Census Bureau about telemedicine utilization between July 2021 to August 2022 found similar differences in race/ethnicity utilization of telemedicine in all Americans and not just those on Medicare. However, the Census Bureau’s survey also found that White Americans were significantly more likely to use video telemedicine than Hispanic, Black, or Asian Americans; the latter were more likely to use audio-only telemedicine.

Medicare versus Medicaid. According to the CMS report, patients who are dually eligible for both Medicare and Medicaid are more likely to use telemedicine than those with Medicare alone. Dual eligible patients are more likely to be poor or disabled.

Age. The CMS report found that patients’ age also influenced telemedicine utilization with Medicare patients under age 65 twice as likely to use telemedicine as those over age 65. However, most Americans under age 65 are covered by commercial health insurance rather than Medicare unless they qualify for Medicare because of disability or end-stage renal disease. Commercially-insured patients were not included in the CMS report. So the data from the graph below may reflect use of telemedicine by disabled Americans on Medicare who have mobility and transportation barriers to coming to physician offices, and not reflect age effects per se. The Census Bureau survey that included Americans with commercial insurance found that older patients were more likely to use telemedicine than younger patients, although older persons are more likely to have any kind of physician visit than younger persons so the Census Bureau data may simply reflect the higher utilization of outpatient medical care in older persons.

Gender. Throughout the pandemic and extending to the present, women on Medicare are slightly more likely to utilize telemedicine than men.

Rural versus urban. Before the pandemic, only rural Medicare patents were eligible for telemedicine visits. However, since the onset of the pandemic, telemedicine is more likely to be used by urban Medicare recipients than rural Medicare recipients. This suggests that the distance a patient must travel to get to a doctor’s office is less of a predictor of telemedicine utilization than other factors.

Reason for Medicare qualification. There are three main ways a person can qualify for Medicare benefits: age over 65, disability, or end-stage renal disease (ESRD). Those qualifying for Medicare because of disability are most likely to use telemedicine, followed by those with ESRD. This likely reflects mobility and transportation barriers faced by disabled persons and those with ESRD.

Other factors. The Census Bureau report included other demographic variables not reported in the CMS report. Specifically, the Census Bureau report found that income correlated with telemedicine utilization with lower income persons more likely to use telemedicine than higher income persons. The Census Bureau report also found that telemedicine utilization varied by a person’s type of insurance with 26.8% of persons on Medicaid, 25.5% of those on Medicare, 19.2% of those with commercial insurance, and 9.0% of uninsured having a telemedicine visit within the previous 4 weeks. It is unclear whether income and insurance type independently affect utilization or whether patients with lower income and those on Medicaid are more likely to have disability or mobility barriers to traveling to physician offices for in-person visits.

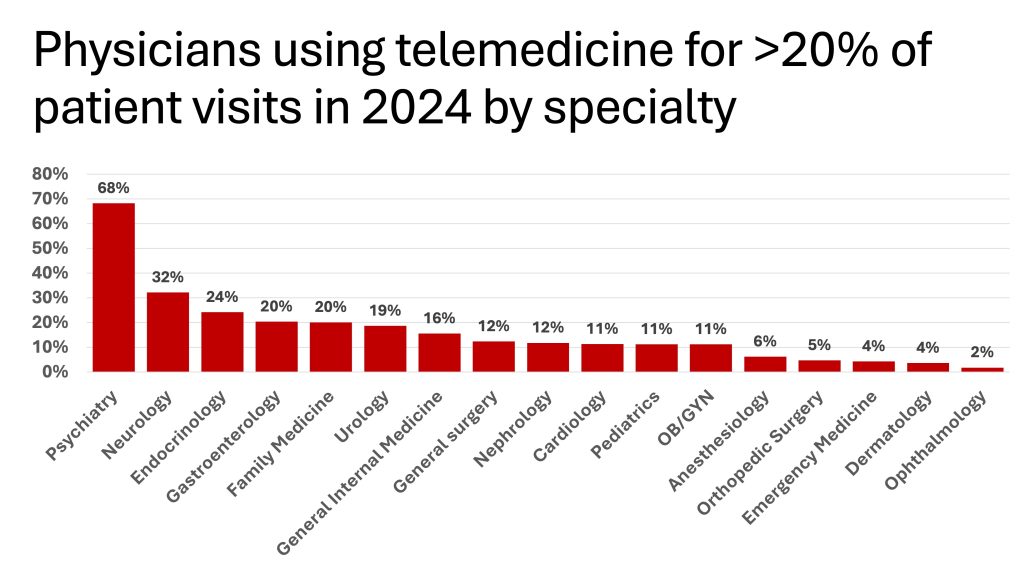
Physicians practicing specialties where a large part of the encounter is devoted to counseling use telemedicine more than those in specialties that require an in-person physical examination. A report by the American Medical association found that psychiatrists were the most likely to utilize telemedicine with 68% of psychiatrists using telemedicine for more than 20% of patient encounters. At the other extreme, only 4% of dermatologists and 2% of ophthalmologists utilize telemedicine for >20% of patient encounters, reflecting the necessity of direct physical examination of the skin and eyes to complete these encounters. Notably, 32% of neurologists use telemedicine for >20% of encounters – many neurology patients have mobility barriers that make coming to the neurologist’s office for an in-person visit difficult.

On the surface, it may seem surprising that telemedicine is utilized as much as it is in gastroenterology (20% using telemedicine for more than 20% of encounters), urology (19% using telemedicine for more than 20% of encounters), and general surgery (12% using telemedicine for more than 20% of encounters). However, these procedure-based specialties often schedule post-procedure follow-up encounters to discuss pathology results with patients and these encounters primarily consist of counseling which lends itself very well to telemedicine. In addition, many post-surgical follow-up visits are bundled into the procedure code for the initial surgery and are thus not reimbursed separately. These post-op visits are often used primarily for symptom reporting which can be done by audio telemedicine or simple examination of an incision which can be done by video telemedicine.

Early in the pandemic, both primary care physicians and specialty physicians mostly billed low-complexity encounters for telemedicine. A study from a New York City health system found that primary care physicians billed low complexity E/M codes for most of their new and return telemedicine encounters. On the other hand, as the pandemic progressed, specialty physicians billed moderate complexity E/M codes for most of their new and return telemedicine encounters. Primary care physicians rarely billed high complexity telemedicine E/M codes but specialists billed a significant number of telemedicine encounters as high complexity (albeit fewer than moderate or low complexity).

Unless Congress passes new legislation in the next month, telemedicine will no longer be covered by traditional Medicare for most Americans who are not living in rural parts of the country with access to a local rural health facility that participates in telemedicine with physicians located elsewhere. Behavioral health telemedicine will continue to be covered as this was made permanent by Congressional legislation in 2021 (of note, behavioral health patients must have an initial new patient in-person visit and an annual return in-person visit). Given the popularity of telemedicine, particularly among those with disability, mobility, and transportation limitations, it is hopeful that Congress will pass new legislation to extend traditional Medicare coverage for telemedicine or make telemedicine coverage permanent. Even if Congress fails to pass an extension, many Medicare Advantage Plans (Medicare Part C) may continue to cover telemedicine since these plans are administered by commercial insurance companies that have the freedom to cover or not cover telemedicine at their own discretion. Similarly, state-specific Medicaid plans and regular commercial health insurance plans may elect to continue telemedicine coverage for their enrollees.

This could result in a patchwork of telemedicine coverage with some patients within a medical practice being eligible for telemedicine coverage and others not eligible. Physician practices will then need to decide if they will offer telemedicine to those patients who do have insurance telemedicine benefits. This would require schedulers to determine whether or not each individual patient is eligible for telemedicine based on their specific health insurance coverage. Some practices may find that it is simpler to just not offer telemedicine to any patients rather than risk denials of bills for telemedicine encounters if a particular patient’s insurance plan no longer covers telemedicine after January 30, 2026.

Even if Congress lets Medicare telemedicine coverage expire in January 2026, patients in certain rural areas will still be eligible for telemedicine coverage based on the pre-pandemic telemedicine rules. However, these rural patients would now be required to go to a local rural health facility for their telemedicine encounter instead of having the telemedicine encounter in their own home. In addition, telemedicine could still be used for post-procedure and post-surgical follow-up encounters when those encounters are bundled into the procedure CPT code and not billed separately.

For now, physicians should not schedule telemedicine encounters for patients with traditional Medicare beyond January 30, 2026. Patients with Medicare Advantage Plans, with state-specific Medicaid plans, and with commercial health insurance policies should be scheduled on an individual basis, depending on whether or not their specific insurance carrier has agreed to continue telemedicine coverage after the telemedicine provisions for traditional Medicare expire. Uninsured patients can continue to be scheduled for telemedicine encounters since these patients pay out of pocket (or do not pay at all) and are thus not subject to Medicare telemedicine coverage rules. Post-procedure telemedicine encounters can continue to be scheduled for all patients if those encounters are bundled into the procedure CPT code, unless the specific code dictates that an in-person post-procedure visit is mandated. Neurologists and endocrinologists will be particularly impacted since these specialties have the greatest penetrance of telemedicine in their practices.

All physicians who use telemedicine should advocate for Congress to make Medicare telemedicine coverage permanent since telemedicine has become particularly beneficial for patients who are disabled and who otherwise have mobility and transportation barriers to in-person office visits.

December 27, 2025

Categories
Medical Economics

What Patients (and doctors) Need To Know About IRMAA

When I turned 65-years-old, I anticipated my healthcare insurance costs would go down as I went on Medicare. After all, I had been paying into Medicare in the way of payroll taxes for decades. But my annual health insurance premiums (medical, vision, and dental) instead went up from $5,736 per year to $6,924 per year. The reason was IRMAA, the Income-Related Monthly Adjustment Amount rule used by Medicare to calculate monthly Part B and Part D premiums.

To understand IRMAA and how it affects Medicare recipients, we first need to understand the basics of the various Medicare Parts:

  • Part A – this covers inpatient hospital care, skilled nursing facilities, hospice, and some home health services. It is free for all Americans over age 65-years-old who have paid payroll taxes for at least 10 years. However, Medicare enrollees are responsible for the cost of various co-pays and deductibles.
  • Part B – this covers outpatient care, physician charges, and medical supplies. It is partially paid for by payroll taxes but Medicare enrollees must also pay a monthly premium.
  • Part C – also called “Medicare Advantage Plans”, seniors eligible for Medicare can opt to enroll in Part C instead of Parts A & B. These plans are administered by commercial health insurance companies that contract with Medicare to cover everything that Medicare Parts A & B cover, with additional coverage for medications and often for dental care, vision care, or fitness centers. They also have deductibles and co-pays but these are typically less than the deductibles and co-pays of traditional Medicare. Think of Part C plans as a bundle of Parts A, B, and D plus a Medigap plan. The downside of these plans is that they have stricter prior authorization requirements for medical services, greater denial of coverage for services, and limit coverage to in-network physicians and hospitals.
  • Part D – these are Medicare drug plans that are administered by commercial health insurance companies. They charge monthly premiums that vary in amount based on the extent of coverage of medications. Part C Medicare Advantage Plans usually incorporate Part D coverage in the plans.
  • Medigap – this is “Medicare supplemental insurance” sold by commercial health insurance companies to help cover the deductibles and co-pays of Parts A & B. They will generally also help cover healthcare costs if hospitalization or skilled nursing facility stays exceed the limit of days covered by Medicare. They can also cover foreign healthcare costs when traveling outside of the U.S. since these costs are not covered by Medicare Parts A & B.

Medicare premiums are complex. Part A is free and has no premiums associated with it but it does come with an annual $1,736 deductible for inpatient hospital care for 2026. Part B has a base monthly premium of $202.90 and has an annual deductible of $283. Part D plan premiums vary among the various commercial insurance companies that offer these plans with each of these plans providing different degrees of coverage for specific medications and different co-pays for medications. Part D plan monthly premiums range from $0 to $123.40 with annual deductibles ranging from $0 to $615. Medigap plan monthly premiums vary among the commercial insurance companies sponsoring Medigap policies and range from $36 to $798 based on age, gender, and health status.

But the base premiums for Medicare Part B and Part D only apply to Medicare enrollees with low annual incomes. The cost of the premiums goes up as enrollee income increases and these additional costs are the Income-Related Monthly Adjustment Amount, or IRMAA. Medicare uses the “modified adjusted gross income” calculated from federal income tax returns to determine the amount of IRMAA. The modified adjusted gross income is calculated by:

  • First, determine your total annal taxable income, found on line 9 of the 1040 income tax form.
  • Next, subtract all of your annual adjustments (deductibles), found on line 10 of the 1040 income tax form.
  • The result is your adjusted gross income, found on line 11 of the 1040 income tax form.
  • Next, calculate the modified adjusted gross income by adding back amounts of certain types of deductions, non-taxable income, and tax credits including:
    • Child tax credit
    • Lifetime learning tax credit
    • American opportunity tax credit
    • Student loan interest deduction
    • Employer-provided adoption benefits
    • Foreign earned income
    • Foreign housing deduction
    • Tax-exempt interest income
    • Non-taxable Social Security benefits
    • IRA contribution deduction
    • U.S. Savings Bond interest

The modified adjusted gross income (MAGI) does not appear on the IRS 1040 income tax form and has to be calculated separately. However, each year, Social Security will calculate your modified adjusted gross income for you, based on your income tax returns from two years previously. Seniors get a letter from Social Security in late November each year notifying them of their modified adjusted gross income. So, letters were sent out this week reporting the 2024 modified adjusted gross income and from that determining the 2026 IRMAA amounts for every Medicare enrollee. The tables below show how IRMA affects monthly premiums for Medicare Part B and Part D.

Single, Head of Household, or Qualifying Surviving Spouse:

2024 MAGI2026 monthly Part B IRMAA2026 monthly Part B premium2026 monthly Part D IRMAA
< $109,000$0$202.90$0
$109,000 – $137,000$81.20$284.10$14.50
$137,000 – $171,000$202.90$405.80$37.50
$171,000 – $205,000$324.60$527.50$60.40
$205,000 – $500,000$446.30$649.20$83.30
> $500,000$487.00$689.90$91.00

Married filing jointly:

2024 MAGI2026 monthly Part B IRMAA2026 monthly Part B premium2026 monthly Part D IRMAA
< $218,000$0$202.90$0
$218,000 – $274,000$81.20$284.10$14.50
$274,000 – $342,000$202.90$405.80$37.50
$342,000 – $410,000$324.60$527.50$60.40
$410,000 – $750,000$446.30$649.20$83.30
> $750,000$487.00$689.90$91.00

Married filing separately:

2024 MAGI2026 monthly Part B IRMAA2026 monthly Part B premium2026 monthly Part D IRMAA
< $109,000$0$202.90$0
$109,000 – $391,000$446.30$649.20$83.30
> $391,000$487.00$689.90$91.00

Because the Medicare Part D premiums vary depending on which Part D plan each Medicare enrollee choses, the total monthly Part D premium will be the base price of the specific Part D plan plus the amount of the Part D IRMAA. Because Medicare Advantage Plans include drug coverage, Medicare recipients who elect to enroll in Medicare Part C will also pay the Part D IRMAA amounts.

IRMAA is not paid to the various commercial insurance companies that sponsor Part D and Part C plans, instead, IRMAA is paid directly to Medicare, along with the usual monthly Medicare Part B premium.

The total amount that any given Medicare enrollee pays for healthcare insurance per year will thus vary based on their annual income, whether or not they purchase a Medigap plan coupled with traditional Medicare, whether they opt for a Part C plan instead of traditional Medicare, and whether they opt for a Part D plan. The least amount paid would be for an individual with a modified adjusted gross income of less than $109,000 who chooses a $0 monthly premium Part D plan and no Medigap plan who would pay $2,435 per year. The highest amount would be for an individual with a modified adjusted gross income of more than $500,000 who opts for the most expensive Part D plan plus the most expensive Medigap plan who would pay $20,428 per year.

Approximately 18% of Medicare enrollees also receive Medicaid and Medicaid will cover some or all of the costs of Part B premiums, Medicare co-pays, Medicare deductibles, and medications. Other government programs that help low-income individuals pay for Medicare premiums, co-pays, deductibles, and medications include the Supplemental Security Income program, Medicare Savings Programs, and the Extra Help program.

Healthcare costs in the United States are the highest in the world and those costs increase as Americans get older. CMS estimates that the total annual cost of healthcare for Americans over age 65-years-old was $22,356 per person in 2020. Because of inflation, those costs have increased to approximately $28,000 today. Even with the IRMAA increases to Medicare premiums, American seniors pay less for their healthcare than they actually spend for health insurance, deductibles, and co-pays after age 65 – all because they are supplemented by workers who are currently paying payroll taxes today.

The additional monthly IRMAA costs that are added to monthly Medicare Part B and Part D premiums often come at a surprise to retirees. For a married couple, this can be many thousands of dollars a year that they had not budgeted to spend in their retirement. As physicians, it is important that we understand IRMAA and educate our patients about its costs before our patients retire in order to avoid unexpected health insurance bills that could jeopardize their retirement plans.

November 24, 2025

Categories
Hospital Finances Medical Economics

When Setting Physician And Nurse Salaries, Factor In Your State’s Cost Of Living

I had a hospital-employed physician ask me for a raise because he had an offer from a Florida hospital that would have paid him several thousand dollars more than his current salary with us in Central Ohio. The problem is that an equal salary in Florida buys you considerably less than in Ohio. When determining salaries for your hospital’s doctors and nurses, you have to consider your state’s specific cost of living. And there is a huge variation between different states.

Salary reports, such as the annual AAMC Faculty Salary Report, break down average physician salaries by geographic region in the country. To some degree, this accounts for differences in the cost of living in one region of the country versus another. But even within a single region, there can be significant differences in the cost of living from one state to another. In order to offer competitive salaries, hospitals must be aware of the cost of living in their state compared to other states. And hospitals must use that information to educate physicians and nurses during contract negotiations.

One of the best sources for state-specific cost of living data comes from the Missouri Economic Research and Information Center. They derive a cost of living index for each state by averaging the indices of cities and metropolitan areas that participate in the Council for Community & Economic Research (C2ER) survey. Individual indices of six groups of costs are considered: grocery, housing, utilities, transportation, health, and miscellaneous. From these six, a composite cost of living index is determined with 100 being the U.S. average. States with an index above 100 have a higher than average cost of living and states with an index below 100 have a lower cost of living. As an example, a state with a cost of living index of 125 indicates that the cost of living in that state is 25% higher than the national average. Importantly, this data is derived from cities and metropolitan areas and not rural areas – in general, the cost of living is lower in rural areas than nearby urban areas, primarily due to lower housing costs in rural areas. The C2ER maintains individual metropolitan area cost of living data available for purchase if you want data that is more granular than an entire state. This can be particularly useful if a cardiologist at your hospital in Indianapolis gets a job offer from a hospital in Philadelphia and you need to create a counter offer in order to keep him/her. The cost of living index for the fifty states, Puerto Rico, and the District of Columbia are show in the table below:

With a composite cost of living index of 186.9, the most expensive state is Hawaii due to a very expensive housing index (310.0) as well as high indices for all of the other groups of costs. At the other end of the spectrum is West Virginia with a composite cost of living index of 84.1, due primarily to very low housing cost index (59.9).

So, when the physician asked our hospital to match his salary offer from Florida, I could show him that the cost of living in Florida (index = 102.8) is 8.6% higher than the cost of living in Ohio (index = 94.2). That means that the same salary would buy him better housing, more groceries, more utilities, more healthcare, and more gasoline in Ohio than it would in Florida.

Becker’s Hospital Review recently published an analysis of registered nurse cost of living-adjusted hourly wages by state. They found that the average total annual R.N. salary is $93,390. The hourly cost of living-adjusted wage in most states is $43.65 per hour. But the state with the second highest total annual R.N. salary was Hawaii at $123,720 that paradoxically had the lowest cost of living-adjusted hourly wage at $31.82/hour. This is because Hawaii’s cost of living is so extremely high compared to the rest of the states. By contrast, in West Virginia, the average total annual salary for an R.N. is $80,650 but the cost of living-adjusted hourly wage is $46.10. The implication is that the annual salary in Hawaii is 50% higher than in West Virginia but that salary buys the nurse 50% less stuff than the salary of a nurse in West Virginia.

The reality is that most nurses in Hawaii are willing to accept a much lower cost of living-adjusted hourly wage than in any other state in the nation because of the non-monetary benefits of living in Hawaii (i.e., living in paradise). But when it comes to comparing states with similar non-monetary attractiveness, knowing the cost of living index is essential in salary contract negotiations. For example, Pennsylvania has an index of 95.1 compared to its bordering neighbor Maryland with an index of 115.3. A hospital in Pennsylvania can pay its doctors and nurses lower salaries than a hospital in Maryland but the purchasing power of those salaries will be equal to (or greater than) the purchasing power of the higher salaries in Maryland. Conversely, if a hospital in Maryland sets the salaries for its doctors equal to the salaries at a hospital in Pennsylvania, then the Pennsylvania hospital can recruit doctors from the Maryland hospital by showing them that thae same salary has 20% more purchasing power in Pennsylvania.

Obviously, there is more than just the local cost of living in salary determination. Productivity expectations, the robustness of the electronic medical record, collegiality of the medical staff, local recreational opportunities, the quality of local schools, the crime rate, etc. all affect how much a hospital has to pay a doctor or nurse. But cost of living is an important factor and using that information strategically can help a hospital’s recruitment efforts. This is especially true for hospital-based physicians such as hospitalists, anesthesiologists, radiologists, emergency medicine physicians, and critical care physicians. Unlike outpatient physicians who need to build a patient practice or develop a referral network, hospital-based physicians are very mobile and can more easily re-locate to a different city or state and still have a full schedule of patients on the first day of practice at a new hospital. Know your region’s cost of living index before you negotiate a contract with your hospitalist group or the nursing union.

April 6, 2025

Categories
Medical Economics

Medicare Can Be Fixed But Do Any Politicians Have The Courage To Do It?

Medicare is running out of money. This is nothing new, we’ve known this for years. The basic reason why is simple: there is less money going into the Medicare Trust Fund than is going out of the Medicare Trust Fund. Many Americans incorrectly believe that when they pay payroll taxes during their working years, the federal government puts that money into some kind of savings account so that they can draw from it for their Medicare bills. The reality is that those Americans’ payroll taxes went to pay for the Medicare benefits of the people who were on Medicare back then. Similarly, when an American retires, their Medicare benefits are paid by the people who are currently working and paying payroll taxes.

When Medicare was introduced in 1965, this set up worked well because there were 4 American workers paying payroll taxes for every 1 American receiving Medicare benefits. Over the past 60 years, the U.S. birth rate has been dropping and the U.S. life expectancy has been increasing. As a result, there are now only 2.7 American workers for every 1 American Medicare beneficiary. This ratio of workers to Medicare beneficiaries is not sustainable and the Medicare Trust Fund is expected to be depleted in 2036. To understand why, it is first necessary to understand how Medicare is funded.

Medicare Part A is funded by the Hospital Insurance Trust Fund. This fund has four sources:

  1. Payroll taxes. This is the overwhelmingly largest source of funds for Part A, accounting for 88% of funding.
  2. Interest earned on money held in the Hospital Insurance Trust Fund. Most of this is in the form of U.S. Treasury bonds and accounts for 8% of Part A funding.
  3. Income tax on Social Security benefits. Currently, Americans have to pay income tax on the money they receive from Social Security. Unlike income tax paid on all other sources of income, Social Security income tax goes to Medicare Part A. This is a minor source of Part A funding.
  4. Part A premiums. Most Americans get Medicare Part A for free, as long as they (or their spouse) have worked and paid payroll taxes for at least 10 years. Americans who do not have a 10-year work history can buy Medicare Part A by paying premiums, just like you would for any other insurance plan. This is a relatively minor source of Part A funds.

Medicare Part B is funded by a totally different fund called the Supplementary Medical Insurance Trust Fund. This fund has three sources:

  1. U.S. Government general funds. This is the largest component of Part B funding, accounting for 71%. These are authorized by Congress and generally derived from regular federal income taxes. Because Part B is partially derived from income taxes, Congress can adjust the income tax contribution to the trust fund each year, preventing it from being depleted.
  2. Medicare Part B Premiums. This is the second largest source of Part B funding, accounting for 27%. Unlike Medicare Part A, Americans have to pay monthly premiums for Medicare Part B. These premiums are income-based and range from $185/month to $629/month, depending on one’s annual income.
  3. Interest earned on money held in the Supplementary Medical Insurance Trust Fund. Similar to Part A, this is usually in the form of interest from U.S. Treasury bonds held by the trust fund. This is a minor source of Part B funding.

Because of the different sources of funds for the Part A and Part B trust funds, only Part A is in danger of being depleted. There are only two basic ways of preventing Part A from becoming depleted: increase money coming into the Part A Hospital Insurance Trust Fund or decrease the money being paid out in Part A benefits.

Politicians have several options to increase annual contributions to the Part A Hospital Insurance Trust Fund:

  1. Increase the payroll tax rate. Currently, payroll taxes are set at 12.4% of annual income (6.2% paid by the employer and 6.2% paid by the employee). By increasing this tax rate, money going into the Part A trust fund will increase. Who would get hurt? All employers who have to pay more in payroll taxes and all workers who also have to pay more in payroll taxes.
  2. Increase the maximum taxable income for payroll taxes. For 2025, payroll taxes are only paid on the first $176,100 of income each year. By increasing this threshold, the annual amount of payroll taxes going into the Part A trust fund will increase. Who would get hurt? Wealthy Americans who have incomes above $176,100/year.
  3. Charge premiums for Medicare Part A. This would provide an additional source of revenue for the Part A trust fund other than payroll taxes. Who would get hurt? Seniors over age 65 who will have their monthly Medicare premiums increase.
  4. Change the law regarding Part A funding sources. Currently, Congress can use federal general funds that are derived from income taxes to pay any shortfall in Medicare Part B but cannot use income tax revenue for Medicare Part A. Congress could pass a law permitting general funds (i.e., federal income taxes) to be used for Part A. However, this would require Congress to increase the federal income tax rate. Who would get hurt? Any American who pays federal income tax.
  5. Increase the number of legal immigrants. Since the fundamental reason that Medicare Part A is running out of money is the drop in the ratio of workers:Medicare beneficiaries from 4:1 in the 1960’s to 2.7:1 today, we can increase that ratio by bringing immigrants into the U.S. who are here legally and pay payroll taxes. The other option is to significantly increase the American birth rate but this would not increase the ratio of workers:Medicare beneficiaries for at least 20-30 years. Who would get hurt? Anyone who dislikes immigrants.
  6. Raise the Medicare eligibility age above the current age of 65-years-old. This would result in Americans retiring later in life so that the ratio of workers:Medicare beneficiaries would increase. An argument often used for this approach is that Americans are living longer and the price of a longer life should be a longer working career. Who would get hurt? Americans younger than 65 who are going to have to work more years before they can retire (or have to buy commercial health insurance if they choose to to retire before the Medicare eligibility age.

Once again, there are several ways of reducing Medicare Part A expenditures:

  1. Raise the Medicare eligibility age above the current age of 65-years-old. This is also listed as a way of increasing money coming into Part A by increasing the working Americans and thus increasing the retirement age. But it also would reduce Medicare expenditures because when the Medicare eligibility age increases, the number of Americans receiving Medicare benefits decreases. In other words, there is a double benefit to increasing the eligibility age by both increasing money going into Medicare via payroll taxes and decreasing money spent by Medicare by decreasing the number of Medicare beneficiaries. Raising the eligibility age can be justified because Americans are living longer. Medicare began in 1965 at which time the U.S. life expectancy at age 65 was 12.9 years for men and 16.3 years for women. Today, the life expectancy at age 65 has increased to 17.0 years for men and 19.8 years for women. In other words, men live 4.1 years longer and women live 3.5 years longer than they did when Medicare first rolled out. Who would get hurt? Americans younger than 65 who are going to have to wait until later in life before they are eligible for Medicare.
  2. Increase deductibles on Part A charges. Currently, there is a Part A deductible limit of $1,676 per hospital stay. People with original Medicare often purchase Medicare Supplemental Insurance (Medigap policies) from commercial insurance companies that pay for deductibles. By increasing the deductible limit, Medicare Part A expenditures would decrease. Who would get hurt? Medicare beneficiaries.
  3. Increase co-pays on Part A charges. Currently, there is no co-pay for the first 60 days of hospitalization and 20 days of skilled nursing facility (SNF) care. After those numbers of days, there are daily co-pay charges. After 150 days of hospitalization or 100 days of skilled nursing facility care, you are responsible for all daily charges. By adding co-pays for all hospital or SNF days, Medicare Part A expenditures would decrease. Alternatively, the number of hospital or SNF days without a co-pay could be reduced from their current numbers. Who would get hurt? Medicare beneficiaries.
  4. Move some Part A services to Part B. This is the sleight of hand approach. By moving services such as home health care or hospice care from Medicare Part A to Medicare Part B, there will be fewer Part A expenditures that have to be covered by payroll tax receipts. Instead, they would be covered by federal government general funds, derived from regular income tax. Who would get hurt? Everyone who pays federal income tax.
  5. Change funding for Medicare Part C. Currently, Medicare Advantage Plans (Medicare Part C) is funded from three sources: Part A funds, Part B funds, and monthly premiums paid by covered individuals. The result is that the commercial insurance company offering a Medicare Advantage Plan then becomes responsible for any Medicare charges that would have otherwise been covered by Part A or Part B in traditional Medicare. Most Medicare Advantage Plans also cover prescription medications (Part D). Medicare Advantage Plans are popular and currently, more than half of Medicare beneficiaries are in a Medicare Advantage Plan instead of traditional Medicare Parts A & B. Congress could change the funding mechanism for Medicare Advantage Plans by making Medicare Part C funded entirely through federal general funds rather than the current mechanism of through both payroll taxes (the Part A component) and general funds (the Part B component). Who would get hurt? Anyone who pays federal income tax since ultimately federal general funds come from income tax revenue.
  6. Change the definition of inpatient hospitalization. “Observation” hospital stays are considered to be outpatient care and thus paid for by Medicare Part B. In 2013, Medicare introduced the “2-midnight rule” that defined an observation stay as any hospitalized patient who was in a hospital bed for a period of time less than 2 midnights. This was a clever way of shifting those short hospital stays from Medicare Part A to Medicare Part B while reducing overall Medicare expenditures by requiring patient co-pays attendant to Part B services. By increasing the 2-midnight rule to 3 or 4 midnights, more hospitalizations would be reclassified as observation stays and thus moved to Medicare Part B. Alternatively, all elective surgical admissions could be redefined as observation stays (currently hospital stays for some surgical procedures are classified as observation stays covered by Part B and others are classified as inpatient stays covered by Part A). Who would get hurt? Medicare beneficiaries who would now be responsible for Part B co-pays and hospitals that are paid less for observation stays than for inpatient hospitalizations.
  7. Reduce DRG payment amounts and SNF daily rates. Hospitals are paid a fixed amount from Medicare Part A based on a patient’s diagnosis, regardless of how many days that patient is in the hospital; this is know a the diagnosis related group (DRG). Skilled nursing facilities are paid based on Medicare’s SNF daily rate that is adjusted based on the types of therapy the patient receives in the SNF. By reducing the amount that Medicare pays hospitals per DRG and the daily rate amount that Medicare pays SNFs, Part A expenditures will drop. Who would get hurt? Hospitals and skilled nursing facilities. Hospitals and SNFs would have to make up the financial loss by charging more to commercial insurance companies, thus raising commercial heath insurance premiums to working Americans. Many skilled nursing facilities would likely go out of business.
  8. Eliminate Medicare coverage for certain medical conditions. Medicare covers just about any medical illness that a person over age 65 has. Part A expenditures could be reduced by eliminating hospitalization coverage for preventable diseases such as COVID in a person who is unvaccinated or smoking-related disease in a person who is an active smoker. This would require controversial social judgements and undoubtedly result in lots of lawsuits from the ACLU and other patient advocacy groups. Who would get hurt? Smokers and anti-vaxxers who would have to pay the cost of treating preventable diseases.
  9. Get rid of Medicare. Possibly one of the most draconian ways to reduce Medicare expenditures is to eliminate it completely. The result would be that lower income retirees would be eligible for Medicaid and wealthier retirees would have to purchase commercial health insurance. This would get the government out of the healthcare entitlement business but still keep Medicaid there as a safety net for the poorest retired Americans. Who would get hurt? Middle class and upper class Americans making more than the Medicaid income threshold. Each state has different Medicaid income requirements but they are typically for individuals making less than about $16,000/year or couples making less than $21,000/year.
  10. Medicare for all. The opposite approach to eliminating Medicare is to make it available to all Americans of all ages. One of the problems with Medicare compared to commercial health insurance plans is that Medicare covers the elderly whereas commercial insurance plans cover Americans younger than 65. Younger people incur less healthcare expenses than older people and consequently, commercial health insurance companies cover the healthiest Americans with the lowest annual healthcare costs whereas Medicare covers the least healthy Americans with the greatest annual healthcare costs. Currently, working Americans and their employers together pay both 12.4% of income for payroll taxes (for Social Security plus Medicare) and an average of $8,500/individual/year for commercial health insurance premiums. For family coverage, those premiums increase to $24,000/year. Since the average annual income in the U.S. is $40,000, the average American worker and their employer is already paying $12,500 per year just for individual healthcare coverage (plus Social Security coverage) and that goes up to $29,000 for family coverage. Medicare for all would be overall less expensive because it would eliminate several costly layers of health insurance bureaucracy. Who would get hurt? Commercial insurance companies that would all go out of business except for those that sell Medigap policies and Medicare Advantage plans. Pharmacy benefits management companies would go out of business. Pharmaceutical companies would have to reduce drug prices.

If I was a politician and was worried about re-election, I would choose a sleight of hand approach and move some services currently covered by Medicare Part A into Medicare Part B. That immediately reduces Part A expenditures and transfers them to Part B where they would be funded by federal government general funds. Eventually, those general fund expenditures would require increasing federal income tax rates, however.

If I was a politician and was not running for re-election, I would gradually increase the Medicare eligibility age from 65 to 67. This has the double effect of (1) increasing the U.S. worker:Medicare beneficiary ratio with an attendant increase in payroll tax revenue while also (2) decreasing Part A expenditures by reducing the total number of Medicare beneficiaries. The justification would be that the Medicare eligibility age has remained at 65-years-old since the inception of Medicare in 1965 whereas the U.S. life expectancy has increased by about 4 years since that time. The cost of being able to live 4 more years is that you have to work a another 2 more years (or at least have buy your own health insurance for a few years if you retire before that age).

There are solutions to the impending Medicare funding crisis, it is just that there are no easy solutions.

March 13, 2025

Categories
Medical Economics

What People Who Run Governments Can Learn From People Who Run Hospitals

Hospitals and governments have a lot in common. They are big organizations; they provide a large number of different services; they employ lots of people; the public depends on them; and Americans love to complain about them. After 40 years of working in hospitals, I’ve seen a lot of management mistakes and learned how to avoid those mistakes. Our political leaders can learn a lot from them as well. Here are some of my thoughts.

When there are budget cuts and you need to reduce staff, the path of least resistance is often to fire all of the newest employees. Physicians and most other hospital professional staff have a 6 or 12-month probationary period before they become full members of the medical or nursing staff. During the probationary period, it is pretty easy to fire them with minimal justification but once they become full members of the medical or nursing staff, it is much more difficult to let them go.

There are several problems with this approach to staffing reductions. First, the newest employees are generally the lowest paid employees and getting rid of them does not save you nearly as much money as getting rid of senior employees.

Second, you end up firing some of your best employees, leaving you with an overall lower caliber workforce. At the Ohio State University, everything is phrased as an analogy to football. Let’s say that the president of the university decided that the football program was too expensive so he directed the coach to cut all of the freshman players. The first year, this will have relatively little impact because most of those freshman would not have been put into games anyway. But the second year, the previous seniors would have graduated so you are dependent on a roster that includes players who would otherwise have just been back-up players and now have to become starters. The team that you put on the field is nowhere near as good. The net result is that the Buckeye football team loses games to all of the other Big 10 teams that did not cut their freshman players the previous years. The same thing happens when governments fire all of their probationary government workers – within a few years, incompetent senior workers get promoted to managerial positions because some of the junior workers who would have made great managers were all fired. In other words, firing all of your probationary workers is a sure way to mediocracy.

Third, it makes it hard to recruit to quality workers in the future. If the best candidates for jobs perceive that there is a strong possibility that there could be future indiscriminate culling of all of the probationary workers, those most qualified candidates will seek jobs elsewhere for better job security purposes. What you are left with is lower quality job candidates who can’t find jobs elsewhere and are willing to risk mass firings during their probationary period because they don’t have other options.

At our hospital, most of the housekeeping staff are immigrants to the United States – especially Somali immigrants. This is because U.S. born citizens don’t want to work in housekeeping and given the current historically low unemployment rate, you can’t keep U.S. born staff in housekeeping because they can get jobs elsewhere that they don’t have to clean toilets and change soiled bed linen. Immigrants do the hospital work that you can’t get anyone else to do. And for the most part, they show up to work every day and are hard workers because they don’t have other work options.

In the larger U.S. economy, immigrants also do the jobs that U.S. born citizens won’t do. They are roofers, painters, cleaning service workers, nannies, and farm workers. I challenge anyone to find 20 U.S. born citizens who will pick tomatoes in your 100 acre tomato farm and show up for 8 hours in the field every day for 3 months out of the year, rain or shine.

When hospitals need to downsize staff, the last people you want to fire are all of those in your accounts receivable department. They are the ones that ensure that the patients and insurance companies that owe you money actually pay. When you let go of too many of your revenue cycle department staff, there is not enough staff left to work denials, collect co-pays, or even know who has and has not paid for their hip replacement surgery.

The IRS is the accounts receivable department for the U.S. government. Yes, it is true that no American likes paying income taxes; but it is also true that Americans do not like paying expensive healthcare bills. If you don’t like high healthcare prices, you don’t blame it on the hospital accounts receivable workers – they are only trying to collect what you knew upfront that you would owe for a healthcare service. Same with the IRS staff – they are just enforcing the tax laws passed by congress.

Wealthy people like to complain that they are disproportionately targeted by IRS audits. Well… duh, of course they are! In our hospital, the accounts receivable employee is going spend an hour to go after the patient who didn’t pay for a $30,000 heart bypass surgery before they will spend an hour to go after the patient who didn’t pay for a $20 flu shot. To extend the analogy, would your local police department put as many detectives to find the person who shoplifted a candy bar as they would to find the person who robbed two million dollars from a bank?

At our hospital, the doctors had to fill out a document every year detailing all of their accomplishments during the past year. We call it the annual “Justify your existence form” and was used to determine promotions, determine salary raises, and justify firings. It took hours to complete and I absolutely hated doing it. For me personally, I had to fill it out in the evenings and weekends because I was too busy doing actual doctoring during the day. The doctors who put the most time into completing the form were those who didn’t have enough work to keep them busy during the day so they had plenty of free time during the workday to embellish their forms. The medical directors and department chairmen who reviewed those forms had dozens and sometimes hundreds of forms to review and so they often just judged them on how many pages of accomplishments a doctor would list rather than the actual content of the document. Consequently, some of the more unproductive doctors would basically list every little thing they did, from individual grand rounds they attended, to the titles of journal articles that they read, to the number of tweets about medicine that they tweeted, and to the number of hours that they volunteered as their kid’s little league baseball coach. Furthermore, people would lie. I had medical directors under my supervision who would list their involvement in hospital committees that I chaired and knew full well that they never showed up for a single meeting all year.

Deciding which federal government workers to fire based on their responses to weekly emails to list all of their accomplishments in the past week makes absolutely zero sense to me. To extend the football analogy, it is like deciding which of your five quarterbacks to start in the big game based on an email asking each one of them to list what they accomplished in practice last week. The person in the best position to judge an employee’s performance is the employee’s supervisor. Coaches are the best judges of football players and officers are the best judges of soldiers.

“A cheap tool is an expensive tool” is one of those things that just about every father tells his kids. The meaning is that if you buy the cheapest hammer at the hardware store, it won’t work as well as the more expensive hammer and it will only last half as long as the more expensive hammer. In other words, in the long run, you’ll end up spending more money if you buy inexpensive, poorly made tools than if you buy expensive but well made tools.

At the hospital, we were required to base equipment purchases on competitive bids. Once, a suture company came in with a very low cost suture and the hospital leadership saw that the hospital could save thousands of dollars a year by switching to this inexpensive suture. The problem was that the suture was difficult to tie, broke easily, and often caused tissues to tear. The result was that the operative times increased, the surgeons had to use twice as many packets of suture than in the past because they had to throw so much of it out, and patients complained about ugly surgical scars. A cheap suture is an expensive suture.

Government efficiency watchdogs love to shout out about the Pentagon buying $20,000 toilets. But those watchdogs better make sure that the $50 toilet that they want to buy from Home Depot instead actually flushes when it is installed in a $10 billion nuclear submarine. The bottom line is that governments, like hospitals, should not make purchase decisions on price alone.

People twist financial reporting and statistics to mean whatever they want them to mean. For example, I had a manager claim that his department was able to reduce expenses by 75% while increasing revenue by 60% over the previous year. Well… that was because that department bought an expensive new MRI machine last year so that they were able to do lots of lucrative MRI procedures this year. He had attributed the entire cost of the MRI machine to that previous year whereas he should have depreciated the cost over the next 10 years. When analyzing cost savings, be sure that there was careful attention to depreciation.

Same goes for revenue. If there were 5 faculty members listed on a $1 million NIH grant, each of the five of them would claim that they were responsible for a million dollars worth of grants. So that’s $5 million, right? …wrong! Similarly, everyone claimed “downstream revenue”. If the transplant surgery department claimed $10 million in clinical revenue for heart transplants the previous year, the cardiology division would also claim that they were responsible for the $10 million in revenue because they referred the patients with heart failure to the surgeons. And the family practice department would claim the $10 million in revenue because they referred those patients to the cardiologists in the first place. Suddenly, that $10 million in revenue looks like $30 million when every department’s spreadsheets are added up.

A number of years ago, our hospital hired a consulting company to identify cost savings measures that we could implement to reduce expenses. The total amount of money that they identified that we could save was breathtaking and the hospital administration pounced on it and hired the consultants for a year to implement all of the cost savings measures. The consulting company promptly advertised to other potential future clients that they were able to save our hospital millions of dollars. But we found out that the cost savings were way, way overinflated. They claimed savings by closing nursing units that were already planned to close, by reducing staff expenses for staff that were planning on retiring anyway (and not including the cost to replace them), by having physicians double up to share offices (that usually only had room for 1 desk), and by eliminating secretary transcriptionists causing the doctors to spend valuable time typing up all of their referral letters. Ultimately, the actual savings at the end of the day were less than the cost of the consultants. Consultants are the worst offenders when it comes to exaggerating the cost savings that they claim they alone can recover.

Once, we had a physician who was in a leadership position in the hospital and had a rival in a different department who he blamed for impeding his academic success. So, that physician went to a local malpractice attorney and told the attorney about some surgeries that the other physician had performed that had complications… and then told that attorney that he would be willing to be a paid expert witness in any malpractice suits agains the surgeon. It was the physician’s way of getting retribution for unrelated grievances. The battle between the two physicians was ugly and costly to the hospital.

I’ve seen division directors take away research lab space from researchers who criticized them. I’ve seen department chairs reassign physicians to dingy offices in the hospital basement because they just didn’t like those physicians. I’ve seen OR directors reassign surgeons to the unpopular Friday afternoon operating room block schedule so that the OR director could himself take the more desirable Tuesday morning OR block. Several years ago, a newly hired division director used her first division faculty meeting to tell the physicians that none of them would we working here one year from now. A medical school dean I knew once told me proudly that he had fired 13 department chairmen in his first year as a dean (he himself was then fired by the university board of trustees and it took the medical school years to recover its academic stature).

When hospital leaders use their position of authority to get revenge on physicians that they perceive have harmed the leaders’ reputations, there is inevitably collateral damage to the hospital. It results in lawsuits that cost the hospital money and time. It creates a hostile workplace environment that is an impediment to physician recruitment and retention. And it damages the hospital’s reputation when word of vindictive acts gets to the local newspaper reporters (as it inevitably does). Vindictive government leaders are no different.

  • If you need to downsize the organization, eliminate staff based on competency and productivity, not on how recently they were hired.
  • Our immigration problem is not that we have too many immigrants, it is that too many of our immigrants are not here legally and thus not paying income taxes and payroll taxes. We need more legal immigrants.
  • Don’t excessively cut the IRS budget unless you are a proponent of a larger federal deficit.
  • Emails demanding federal workers justify their jobs is unproductive and will not identify incompetent or unproductive workers.
  • Sometimes using cost as the primary decision making determinant in federal expenditures in the name of improving efficiency actually creates greater inefficiency.
  • All federal government statements claiming cost savings must be independently fact-checked and audited. It is human nature to exaggerate and lie in order to justify whatever it is that they are doing.
  • When an organization’s leaders use their position of authority to get revenge on others, the entire organization suffers.

March 6, 2025

Categories
Medical Economics

How To Keep Medicare From Running Out Of Money

Time is running out but there is still an opportunity to save the Medicare trust fund and prevent it from running out of money in 2036. This is the 4th in a series of posts about Medicare funding. The first post demonstrated why the COVID pandemic extended the Medicare trust fund depletion date from 2031 to 2036. The second post provided an overview of the complex way Medicare is funded. The third post outlined the reasons why the Medicare trust fund will become insolvent in 2036. To summarize, the Medicare Hospital Insurance (HI) trust fund that covers Medicare Part A will become depleted due to a combination of health care inflation and a reduced ratio of current American workers to Medicare beneficiaries. The Medicare Supplementary Medical Insurance (SMI) trust fund that covers Medicare Parts B and D is not in danger of depletion.

Unlike the SMI trust fund, the HI trust fund (Medicare Part A) is mainly funded by payroll taxes that are paid by Americans who are currently employed. The SMI trust fund is mainly funded by income taxes and Medicare premiums. Here are the options that policy makers must choose from to address the impending depletion of the Medicare HI trust fund.

If the HI trust fund becomes depleted, it will only be able to cover 89% of inpatient hospital care, nursing home care, and hospice care. It would then up to Medicare beneficiaries to pay for 11% of that care themselves, either out of pocket or by purchasing supplemental health insurance. This would increase costs to Medicare beneficiaries and would be a particular hardship on the elderly who depend on relatively low fixed incomes.

Currently, Medicare Part A pays for inpatient hospitalization, skilled nursing facilities, some home health care, and hospice care. Medicare Part C (Medicare Advantage plans) covers health care services from both Part A and Part B. The current expenditures from Medicare Parts A, B, and D are shown in the table below.

One of the simplest solutions to prevent the HI trust fund from becoming depleted is to simply move all home health care that is currently under Part A ($6 billion) into Part B in 2025. This will briefly delay the trust fund’s depletion. By then moving hospice care ($26 billion) from Part A into Part B in 2033, Part A should remain solvent for the foreseeable future.

Of course, this does nothing to reduce overall Medicare expenditures, it is just a sleight of hand movement to a different funding mechanism. The result is that all home health care and hospice care would be funded by income taxes rather than payroll taxes. Ultimately, congress would need to increase income taxes to cover the increased federal general funds used to cover home health and hospice care in Medicare Part B.

There is some precedent for this option. When Medicare created the “2-midnight rule”, it decreed that any patient requiring a hospitalization of less than 2 midnights would be declared an outpatient hospitalization rather than an inpatient hospitalization. This moved all of these so-called observation hospital stays from Medicare Part A into Medicare Part B, thus improving the financial status of the Medicare HI trust fund.

Since Medicare’s inception in 1965, the age of Medicare eligibility has remained unchanged at 65 years old. However, by 2019, life expectancy from age 65 has increased by 5.3 years for men and 4.5 years for women compared to life expectancy from age 65 in 1965 (these numbers fell in 2021 and 2022 due to COVID). But Americans are not working more years, instead these extra years of life expectancy are being spent in retirement. It can be argued that the price of living a lot longer should be working a little longer.

There is some precedent for this option, also, In the 1950’s the Social Security retirement age was 65. Today, the Social Security full retirement age is 67, although people can opt to retire as early as 62 with reduced benefits. Increasing the Medicare age to 67 would seem to be logical and keep it in line with the Social Security full retirement age.

This would undoubtedly anger Americans who are close to retirement who would be faced with having to work 2 years longer than they had planned. A compromise could be offered to allow those between age 65 and 67 to purchase Medicare Part A by paying premiums for it.

Currently, Medicare’s portion of the payroll tax is 2.9% for most Americans and 3.8% for those making more than $200,000 ($250,000 if married). Health care costs have risen much faster than worker wages over the past 40 years and thus health care inflation has risen faster than payroll tax contributions to Medicare Part A. It can be argued that the cost of Americans having better health and living longer should be paying for the health care that they are using and this would require increasing the Medicare payroll tax to keep up with health care inflation.

There is precedent for this option. When Medicare was rolled out in 1966, the Medicare payroll tax was only 0.35%. This was gradually increased until 1986 when it reached the current value of 2.9%. The higher payroll tax rate of 3.8% on high income earners went into effect in 2013.

Another way of making up the shortfall in payroll taxes to cover Medicare Part A costs would be to charge Medicare beneficiaries premiums for Part A coverage. Currently, Medicare Part A is free to all Americans over age 65 who have worked and paid payroll tax for at least 10 years.

Medicare beneficiaries already pay monthly premiums for Medicare Part B and Part D. The problem with charging all beneficiaries premiums for Part A is that many elderly who are living on fixed incomes from Social Security benefits would not be able to afford to pay more in Medicare premiums than they had originally budgeted when they retired. One option to address this would be to charge Part A premiums based on income. For example, leaving Medicare Part A as being free for those with a modified gross income less than $25,000 and then charging premiums that increase with higher incomes.

The U.S. fertility rate has fallen from 3 live births per woman in 1960 to 1.62 live births per woman today. Without immigration, this would result in negative population growth with a shrinking population. For Medicare Part A to remain solvent, there must be more workers paying payroll tax than there are Medicare beneficiaries in any given year. Historically, that ratio was 4 workers per Medicare beneficiary but the ratio has fallen since 2000 and is currently only 2.8 workers per Medicare beneficiary. The falling U.S. fertility rate means that the U.S. cannot rely on children born to U.S. citizens to provide a sufficiently large workforce to support Medicare Part A from payroll taxes. Ideally, immigration should prioritized to children and young adults. Because payroll taxes are a fixed percentage of modified adjusted gross income, regardless of how high that income is, immigrants who will contribute the most in payroll taxes are those who would be expected to have the highest incomes in the United States. In other words, those immigrants with college or graduate degrees.

There are currently about 11 million undocumented immigrants living in the United States and 95% of those are over age 16. As undocumented immigrants, they cannot get Social Security numbers and consequently they do not pay any payroll taxes since payroll taxes are linked to Social Security numbers. Neither are they eligible to get Medicare when they turn 65. However, our nation’s hospitals are legally required to provide emergency medical care in the ER or in the hospital to everyone so undocumented immigrants are already getting medical treatment that is ultimately paid for by American taxpayers. We would be far better off if we converted undocumented immigrants to immigrants with work visas or citizens so that we can start collecting payroll taxes on the work that they are already doing but just getting paid under the table.

The fundamental problem with the Medicare HI trust fund is that it depends almost entirely on payroll taxes whereas the Medicare SMI trust fund derives its money from income taxes and Medicare premiums. Congress could change the law to use federal general funds to cover the Medicare HI trust fund shortfall. However, since general funds are derived from income taxes, this option would have the downstream effect of requiring congress to increase income taxes.

The problem with taxes is that nobody wants to pay them. Consequently, the U.S. has created an incredibly complex tax system that taxes different things in different ways. There is payroll tax that taxes wage-earning workers. Consumption taxes, such as sales tax and gasoline tax, are paid by consumers. There is capital gains tax that taxes investors. There is income tax that taxes wages, some investments, pensions, and tax-deferred retirement plan withdrawals. There is property tax that taxes homeowners. And that brings up the philosophical question of who should pay for the health care of today’s seniors? By funding Medicare Part A with payroll taxes, it is current wage-earning workers. But should it instead be paid by investors? pensioners? land owners? consumers? Someone ultimately has to pay for Medicare Part A through taxes, the questions is just exactly who should have to pay those taxes?

This is the ultimate solution the problem of depletion of the Medicare trust fund. The reasons why Americans pay so much more for their health care than people in any other country are complex. There is not a single, simple solution to fixing this problem. Americans pay way more than anyone else for medications. The Inflation Reduction Act of 2022 will help lower Medicare costs by lowering the costs of many expensive drugs. But to really control health care costs would require a major overhaul of the U.S. health care delivery system and in the current political climate, the chances of that happening the near future are nil.

So, if I was a government policy maker, how would I fix the Medicare HI trust fund? The fundamental problem is that Medicare Part A is spending more than it brings in from payroll taxes. Here are the measures that I would take:

  1. Move all home health into Medicare Part B in 2025 and hospice care into Medicare Part B in 2030. This would reduce the amount of money that Part A would have to spend and prevent the HI trust fund from becoming depleted (at least temporarily). However, this will just mean that those costs will have to be covered by income taxes or government borrowing. it is like “rearranging the deck chairs on the Titanic” but it does at least buy a few years for other policy changes to go into effect.
  2. Raise the Medicare full benefit age to 67. This would align with the Social Security full retirement age of 67. It would also decrease the number of Medicare beneficiaries while increasing the number of wage-earning workers since they would likely postpone retirement. The net effect would be to improve the ratio of current workers to current Medicare beneficiaries. Since Americans are living 5 years longer from age 65 than they were when Medicare was enacted in 1965, it can be justified that Americans work 2 years longer than they did in 1965 – 2 years of extra work is the price for 5 years of extra life. This would cause an uproar among those over age 50 since their retirement would be unexpectedly pushed back 2 years, but a compromise would be to offer those between ages 65 and 67 the option to buy Medicare by paying monthly premiums for both Parts A and B. This would be similar to the option to take Social Security early at age 62 with a reduced monthly benefit. So, if a person wants to retire at 65 they can but they have to pay for their own Medicare Part A coverage until they are 67.
  3. Increase immigration. This will be solve the problem of the United States’ declining fertility rate and increase the number of wage-earning workers. Ideally, those immigrants would be young enough to have at least 25-30 future working years and skilled enough to have high incomes (and thus more payroll tax contributions). Therefore, the “best” immigrants from a Medicare trust fund standpoint would be those who are under age 40 with a college degree. Immigrant children would also be beneficial to the Medicare HI trust fund since they will become wage-earning workers in the future.

The Medicare Part A funding strategy when Medicare was enacted worked fine in the 1960s but a combination of an increased U.S. life expectancy, health care inflation, more Americans going to college and entering the workforce later in life, and a declining U.S. fertility rate have now made the original funding strategy insufficient. The question presently faced by the United States is who will pay for Medicare Part A now that payroll taxes alone will not suffice? Every option will make someone unhappy.

July 25, 2024

Categories
Medical Economics

Why The Medicare Trust Fund Is Running Out Of Money

Currently the Medicare Hospital Insurance (HI) trust fund is projected to be depleted in 2036. At that time, Medicare will only be able to pay for 89% of the cost of inpatient hospital and nursing home care. The previous post outlined the sources of funding for Medicare Part A, Part B, and Part D. Because each of these Medicare components are funded differently, only Medicare Part A is in danger of insolvency. But how did we get here? The simple answer is that health care costs are increasing faster than Medicare payroll taxes. But an in-depth look indicates that the causes of Medicare’s impending insolvency are much more complex. In order to develop solutions to the depletion of the Medicare trust fund, we must first understand the complex reasons causing the trust fund to run out of money. We can group these reasons into two broad categories: (1) health care cost inflation and (2) a falling ratio of currently working Americans to Medicare beneficiaries.

Inflation is the increase in the cost of goods and services. It is commonly measured by changes in the consumer price index, as determined by the U.S. Department of Labor Statistics. The country’s overall average inflation rate is the sum of the individual inflation rates of all goods and services but each of these individual inflation rates vary considerably. The inflation rate for health care has consistently been higher than the overall average inflation rate. Since 2000, the increase in the consumer price index for all goods and services is up by 85% but the increase in the cost of health care is up by 119% as shown in the graph below.

Inflation is not necessarily bad because the cost of goods and services generally rises in tandem with worker wages. Only if inflation rises faster than worker wages is there a problem for the average American. Since 2000, wages have increased by an average of 82%, fairly close to the overall inflation rate but far less than the inflation rate for health care.

Because of health care inflation, Medicare expenditures are projected to increase at a faster pace than either worker’s earnings or the economy overall and as a result, money coming into Medicare Part A cannot keep up with money going out of Medicare Part A. Currently, Medicare expenditures are 3.8% of the nation’s overall GDP (gross domestic product) but this will increase to 5.8% by 2048.

Americans already pay more for health care than citizens in any other country. The OECD reports that in 2022, the cost of health care in the U.S. averaged $12,500 per person.

Because Medicare beneficiaries are by definition older or disabled, they generate higher health care costs than the average American. In 2023, the cost of health care for the average Medicare beneficiary was $16,710 per year. The net result of health care inflation is that each year, Medicare must spend increasingly more to pay for medical services for any one Medicare beneficiary.

Many Americans have the misconception that their Medicare benefits are funded by the money from the payroll taxes that they paid themselves when they were working. This is completely inaccurate – Medicare does not save the money that we individually pay in the way of payroll taxes in some kind of personal account. Medicare beneficiaries are supported by those people who are paying payroll taxes today. In order to maintain Medicare solvency, there must be a constant ratio of current workers to current Medicare beneficiaries. Historically, that ratio was 4:1, that is 4 Americans currently working and paying payroll taxes for every 1 Medicare beneficiary. That ratio started to fall in 2000 and is now down to 2.8:1. It is projected to fall even further over the next several decades as shown in the graph below from the most recent Annual Report by the Board of Trustees of the Medicare Trust Funds.

Medicare Part A is funded through the Medicare Hospital Insurance trust fund (HI). As the ratio of currently working Americans to Medicare beneficiaries falls, payroll taxes become insufficient to fully fund Medicare Part A expenses, eventually resulting in depletion of the Medicare HI trust fund.

There are several reasons for the reduced ratio of current workers to Medicare beneficiaries including (1) improved life expectancy, (2) reduced American birth rate, (3) the baby boomer population surge enrolling in Medicare, and (4) Americans working for fewer years than in the past. Let’s now look at each of these.

Over the past 120 years, medical science has allowed Americans to live longer. In 1900, the life expectancy from birth was 47 years and today it is 77.5 years, a 30 year longer life expectancy.

Much of the increase in life expectancy from birth has been due to improvements in infant and maternal mortality rates. For Medicare financing purposes, a better measure is life expectancy from age 65. In 1965, when Medicare was enacted, U.S. life expectancy from age 65 was 12.9 years for men and 16.3 years for women. In 2022, those numbers grew to 17.5 years for men and 20.1 years for women. In other words, American men are on Medicare 4.6 years longer (26%) than in 1965 and American women are on Medicare for 3.8 years longer (19%) than they were in 1965.

This striking improvement in life expectancy could not have been anticipated back when Medicare was first created. It is due in part to improvements in medical science and in part due to the reduction in cigarette smoking. In 1965, 52% of men and 34% of women smoked; today, only 13.1% of men and 10.1% of women smoke. The cost of our better health and improved life expectancy is being paid by Medicare that has to now pay medical expenses for more years per person. COVID gave us a temporary reprieve by preferentially killing Medicare beneficiaries and reducing average U.S. life expectancy by 2.3 years. But this reprieve will be short-lived as life expectancy returns to 2019 values over the next few years.

Americans are having fewer children and increasingly, more American women are having no children at all. The birth rate is the number of live births per 100,000 population. The fertility rate is the number of live births per women of childbearing age and is a better measurement of the number of children women are having. In 1965, the U.S. fertility rate was 3 live births for every 1 woman. Today, the U.S. fertility rate is only 1.62 live births for every 1 woman. In other words, the U.S. birth rate is about half of what it was in 1965 when Medicare was enacted.

As Americans have fewer children and those children grow up to become working adults, there are fewer working adults to pay payroll taxes and thus fewer working adults to support today’s Medicare beneficiaries.

There have been two recent surges in the U.S. total population – the baby boomer surge and the peak millennial surge. The peak millennials are the children of the baby boomers. In the graph below, these two surges can be seen in the males and females at age 60-64 (baby boomers) and at age 30-34 (peak millennials).

When a population surge hits age 65, there is a sudden increase in the number of people retiring from the workforce going on Medicare and this will reduce the ratio of current workers to current Medicare beneficiaries. The baby boomer surge has contributed to the inability of current payroll taxes to fund Medicare Part A. The United States will experience a similar surge in 30 years when the peak millennials enter Medicare.

The net effect of Americans living longer, the decreased U.S. fertility rate, and the baby boomer population surge has resulted in a disproportionately large increase in the number of Americans who are over age 65. In 1965, 9.6% of Americans were over age 65 and today, 17.6% of Americans are over age 65.

Medicare was designed to care for about 10% of the U.S. population but today, it has to cover nearly 18% of Americans. The Medicare funding equations that worked in 1965 simply do not work in 2024.

When Americans retire, they are no longer paying payroll taxes. When Americans retire at an earlier age, there are fewer Americans paying payroll taxes and thus less total money going into Medicare Part A every year. In 1965, at Medicare’s inception, the average American man retired at age 66. Today, the average American man retires at age 65. On the surface, this does not seem like much – only one year. However, that one year is usually at the point in a person’s career when they are earning the most money and therefore paying the most payroll taxes.

In contrast to men, American women are retiring later in life than in the past. In 1965, the average American woman retired at age 56 and today women retire on average at age 62. This increase represents a trend over the past 50 years for more women to work outside of the home while raising children and to continue working after those children leave home. The bad news is that American men’s income continues to be higher than American women’s income (the gender wage gap). The average American woman earns only 83.6% of the average American man. Thus, men retiring 1 year earlier has a greater reduction in payroll taxes than the increase in payroll taxes when women work 1 year longer.

But retirement age only tells part of the story when it comes to the number of years a man or woman works and contributes payroll taxes. The other part of the equation is when a man or woman enters the workforce and that generally does not happen until the completion of education. In 1965, 12.0% of men and 7.1% of women had a college education. In 2021, 36.2% of men and 39.0% of women had a college educations. Furthermore, more Americans are attending graduate school after college – 13% of Americans have a master’s degree, 3.5% have a professional degree, and 2% have a doctorate. By going to college, people enter the workforce about 4 years later in life than if they went to work directly after high school. Graduate school adds another 2-6 years. Although college educated people earn more than non-college educated people, they pay payroll taxes for fewer total years before retiring.

Although Americans are working fewer years between completion of education and retirement, the Medicare payroll tax rate of 2.9% has not changed in the past 38 years. However, there was a 0.9% tax premium on top of the base Medicare payroll tax for people earning more than $200,000 per year ($250,000 if married) that was enacted in 2013.

Since Medicare’s inception in 1965, the age of Medicare eligibility has not changed – it was age 65 in 1965 and it is still age 65 in 2024. On the other hand, the Social Security full retirement age has increased from age 66 in 1954 to age 67 today. Thus, the Social Security full retirement age is two years later than the age that Americans start Medicare. And herein lies a philosophical question – what should the Medicare age be tied to? Should it remain the (somewhat arbitrary) age of 65? Should it be tied to the Social Security full retirement age of 67? Should it be tied to life expectancy? Should it be tied to the number of working years?

If nothing is done, then the Medicare Part A trust fund will be depleted in 2036 and Medicare will no longer be able to fully cover inpatient hospital care, nursing home care, and hospice care. In the next post, we will examine options for preventing this from happening.

July 24, 2024

Categories
Medical Economics Uncategorized

How Is Medicare Funded? (hint: it’s complicated)

This is the second in a series of posts about Medicare funding and how to prevent depletion of the Medicare trust fund. In the previous post, we saw how the COVID pandemic extended the date of Medicare insolvency from 2031 to 2036 by preferentially killing Medicare beneficiaries and thus reducing future Medicare expenditures for all of those Americans who died. But the Medicare trust fund is still going to run out in 2036. To understand why, it is necessary to first understand how Medicare is funded.

Medicare consists of four components: Parts A, B, C, & D. Each of these is funded differently. Medicare Part A is funded by the Hospital Insurance trust fund (HI). Medicare Parts B & D are funded through the Supplementary Medical Insurance trust fund (SMI). Medicare Part C (Medicare Advantage Plans) is funded through both the HI and SMI trust funds.

Every year, the Board of Trustees of the Medicare trust funds publishes a report on the status of the trust funds. The most recent report was released in May 2024. In 2023, Medicare covered 66.7 million Americans (59.1 million over age 65 and 7.6 million who were disabled). Medicare total expenditures were $1,037.0 billion and Medicare income was $1,024.6 billion. This gave Medicare a $12.4 billion surplus in 2023 that is carried forward to 2024 in the Medicare trust funds.

The average benefit paid per Medicare enrollee in 2023 was $16,710. Of that, Part A accounted for $5,992 (36%), Part B accounted for $8,177 (49%), and Part D accounted for $2,541 (15%).

When the HI and SMI trust funds are lumped together, Medicare as a whole derives its funds from six sources: (1) payroll taxes, (2) federal government contributions, (3) premiums, (4) taxes on Social Security, (5) payments from states, and (6) interest.

  1. Government contributions (43%). From the graph above, it is clear that the largest funding source for Medicare is from the federal government. Specifically, this is from the general funds that are primarily derived from personal and corporate income taxes. The general fund transfers into Medicare are reset each year by Congressional budgetary legislation. A common misconception of Americans is that Medicare is mostly funded by Medicare payroll taxes whereas in reality, income taxes are ultimately the largest source of Medicare funding.
  2. Payroll taxes (36%). These are taxes paid by working Americans and their employers on earned income. The total payroll tax rate for most workers is a flat 12.4% of income with half (6.2%) paid by the employee and half (6.2%) paid by the employer. Payroll tax covers Social Security and Medicare. The portion allocated to Medicare is 2.90% with 1.45% paid by the employee and 1.45% paid by the employer. In addition, single workers earning more than $200,000 per year (or married workers jointly earning more than $250,000 per year) pay an additional 0.9% Medicare payroll tax for a total payroll tax of 3. 8% allocated to Medicare. Unlike the Social Security portion of the payroll tax that is limited to the first $168,000 of earnings, there is no limit on the amount of earnings subject to the Medicare portion of the payroll tax.
  3. Premiums (15%). Medicare part A is free to most Americans but Medicare Part B and Part D require monthly premiums charged to each Medicare beneficiary. The amount of the premium depends on a person’s modified adjusted gross income in any given year. The lowest premium (paid by most Medicare beneficiaries) is $174.70 per month. The highest premium is $594.00 per month, paid by beneficiaries with a modified adjusted gross annual income of more than $500,000 per year ($750,000 per year if married filing jointly). For determination of an individual’s monthly premium rate, there is a hold-harmless provision in the law that limits the dollar increase in the premium to the dollar increase in an individual’s Social Security benefit. Thus, by law, Part B premiums cannot rise faster than Social Security benefits.
  4. Taxation of benefits (3%). When a person receives Social Security and their total income is high enough, their Social Security benefit is subject to federal income tax. A portion of that income tax is directly allocated to Medicare part A.
  5. Payment from states (2%). For those people who are dually eligible for both Medicare and Medicaid, a portion of the money to cover Part D medication costs is covered by the states.
  6. Interest (1%). Money held in the Medicare trust funds that is not immediately needed to pay for healthcare costs is invested in U.S. Treasury securities and the interest from those investments is included as income to the trust funds. Currently, the Medicare trust funds have $396.7 billion held in U.S. Treasury securities giving $10 billion in annual interest.

The HI trust fund covers Medicare Part A. The HI is funded differently than the SMI trust fund that covers Medicare Parts B and D. Medicare Part A covers inpatient hospitalization, skilled nursing facilities, some home health care, and hospice care.

The overwhelming majority of funding for Medicare Part A comes from payroll taxes (88%) with a smaller amount from taxation of Social Security benefits (8%) and less than 2% each from interest income and premiums for those with insufficient work history to qualify for free Part A benefits.

The SMI trust fund covers Medicare Parts B and D. In turn, Medicare Part B is funded differently than Medicare Part D. Medicare Part B covers outpatient hospital care, physician professional fees, some home health care, durable medical equipment, physician-administered outpatient drugs, outpatient labs, outpatient radiology, and other outpatient services.

The overwhelming majority of Medicare Part B is covered by federal government general fund contributions (71%). These government contributions are derived primarily from personal and corporate income taxes. Medicare Part B premiums account for most of the rest of Part B funding (27%). Less than 1% is derived from interest income. Importantly, payroll taxes do not contribute at all to Medicare Part B funding.

Medicare Part D covers outpatient medications and falls under the SMI trust fund.

Part D is mainly funded by government general fund contributions from personal and corporate income taxes (73%). Part D premiums paid by Medicare beneficiaries account for 14%. Payment from states (to cover medications for people dually eligible for both Medicare and Medicaid) accounts for 12%. Interest income accounts for < 1%.

As shown above, the SMI trust fund that covers Medicare Parts B and D is funded primarily from federal government general funds (personal and corporate income tax) and premiums paid by Medicare beneficiaries. The amount of general fund contributions and premiums are reset each year by congress to insure that the SMI trust fund never runs out. For this reason, the SMI trust fund is in no danger of becoming depleted. As noted above, Medicare Part B premiums cannot be increased any more than the cost of living increase in Social Security benefits so if Medicare costs rise faster than the overall inflation rate, Part B premiums will be insufficient to keep up with Part B expenditures. Therefore, as Medicare Part B and Part D costs increase in the future, the federal government will be required to use a greater percentage of its income tax revenue to cover the higher costs.

On the other hand, the HI trust fund that covers Medicare Part A is permanently tied to payroll taxes. Under current law, the HI trust fund is not able to get additional money from the federal government general fund and thus cannot make up any shortfalls from income taxes. If Medicare Part A costs increase faster than money coming into Medicare from payroll taxes, then the HI trust fund will be depleted. There is currently $209 billion in the HI trust fund. Under current projections, HI trust fund expenditures will begin to exceed HI income from payroll taxes in 2030, requiring Medicare Part A to begin to deplete the HI trust fund reserves. The HI trust fund is projected to be fully depleted in 2036. At that time, Medicare Part A can only pay out as much as it receives in payroll taxes each year – this is projected to reduce beneficiary payments for hospital and nursing home care by 11%.

In the next post, we will see how several different factors have contributed to the HI trust fund’s impending depletion.

July 23, 2024