Categories
Medical Economics Outpatient Practice

Telemedicine Ends For Most Americans In January 2026 (…maybe)

Until 5 years ago, telemedicine was only reimbursed for patients in rural locations where long-distance travel for patients to get to a doctor’s office was difficult. Medicare required these patients to go to a rural health facility and the telemedicine encounter with a remote physician would then be conduced with the patient physically at the rural health facility. At the beginning of the COVID pandemic, Congress expanded telemedicine in order to allow patients to continue to receive outpatient services without having to physically go to a doctor’s office. This protected patients from exposure to contagious diseases in the waiting room, protected medical staff from exposure to contagious patients, and helped conserve personal protective equipment (PPE). The expansion of telemedicine was supposed to be a temporary measure with the intention that it would go away as the pandemic receded. But it turns out that both patients and doctors like telemedicine and now the onus is on Congress to make telemedicine permanent.

The temporary telemedicine expansion was set to expire on October 1, 2025. It had been anticipated that Congress would pass legislation to extend telemedicine beyond that date but with the government shutdown, Congress did not meet to pass any new legislation. Thus, as October 1st came and went, physicians largely stopped providing telemedicine because Medicare no longer paid for it. When the government shutdown ended, Congress passed a stopgap legislation to temporarily continue telemedicine coverage by Medicare until January 30, 2026. Without new legislation, telemedicine coverage will revert to the pre-pandemic restrictions of rural-only coverage.

At the beginning of the COVID pandemic, telemedicine was hugely popular with both patients and physicians. Office staff revised their workflows with many staff able to work from home. Physicians added cameras to their computer workstations to permit video conferencing with patients. Clinic parking lots became empty. The percent of Medicare patients using telemedicine shot up with 47% of them having a telemedicine visit in the second quarter of 2020 alone. As the pandemic waned, use of telemedicine fell but even this year, about 12% of Medicare patients have a telemedicine visit in any given quarter as shown from a graph below from a November 2025 CMS report.

Race and ethnicity. CMS reports that Hispanic and Asian Americans on Medicare are most likely to currently use telemedicine whereas White and Native Americans are least likely to use telemedicine. A household pulse survey by the U.S. Census Bureau about telemedicine utilization between July 2021 to August 2022 found similar differences in race/ethnicity utilization of telemedicine in all Americans and not just those on Medicare. However, the Census Bureau’s survey also found that White Americans were significantly more likely to use video telemedicine than Hispanic, Black, or Asian Americans; the latter were more likely to use audio-only telemedicine.

Medicare versus Medicaid. According to the CMS report, patients who are dually eligible for both Medicare and Medicaid are more likely to use telemedicine than those with Medicare alone. Dual eligible patients are more likely to be poor or disabled.

Age. The CMS report found that patients’ age also influenced telemedicine utilization with Medicare patients under age 65 twice as likely to use telemedicine as those over age 65. However, most Americans under age 65 are covered by commercial health insurance rather than Medicare unless they qualify for Medicare because of disability or end-stage renal disease. Commercially-insured patients were not included in the CMS report. So the data from the graph below may reflect use of telemedicine by disabled Americans on Medicare who have mobility and transportation barriers to coming to physician offices, and not reflect age effects per se. The Census Bureau survey that included Americans with commercial insurance found that older patients were more likely to use telemedicine than younger patients, although older persons are more likely to have any kind of physician visit than younger persons so the Census Bureau data may simply reflect the higher utilization of outpatient medical care in older persons.

Gender. Throughout the pandemic and extending to the present, women on Medicare are slightly more likely to utilize telemedicine than men.

Rural versus urban. Before the pandemic, only rural Medicare patents were eligible for telemedicine visits. However, since the onset of the pandemic, telemedicine is more likely to be used by urban Medicare recipients than rural Medicare recipients. This suggests that the distance a patient must travel to get to a doctor’s office is less of a predictor of telemedicine utilization than other factors.

Reason for Medicare qualification. There are three main ways a person can qualify for Medicare benefits: age over 65, disability, or end-stage renal disease (ESRD). Those qualifying for Medicare because of disability are most likely to use telemedicine, followed by those with ESRD. This likely reflects mobility and transportation barriers faced by disabled persons and those with ESRD.

Other factors. The Census Bureau report included other demographic variables not reported in the CMS report. Specifically, the Census Bureau report found that income correlated with telemedicine utilization with lower income persons more likely to use telemedicine than higher income persons. The Census Bureau report also found that telemedicine utilization varied by a person’s type of insurance with 26.8% of persons on Medicaid, 25.5% of those on Medicare, 19.2% of those with commercial insurance, and 9.0% of uninsured having a telemedicine visit within the previous 4 weeks. It is unclear whether income and insurance type independently affect utilization or whether patients with lower income and those on Medicaid are more likely to have disability or mobility barriers to traveling to physician offices for in-person visits.

Physicians practicing specialties where a large part of the encounter is devoted to counseling use telemedicine more than those in specialties that require an in-person physical examination. A report by the American Medical association found that psychiatrists were the most likely to utilize telemedicine with 68% of psychiatrists using telemedicine for more than 20% of patient encounters. At the other extreme, only 4% of dermatologists and 2% of ophthalmologists utilize telemedicine for >20% of patient encounters, reflecting the necessity of direct physical examination of the skin and eyes to complete these encounters. Notably, 32% of neurologists use telemedicine for >20% of encounters – many neurology patients have mobility barriers that make coming to the neurologist’s office for an in-person visit difficult.
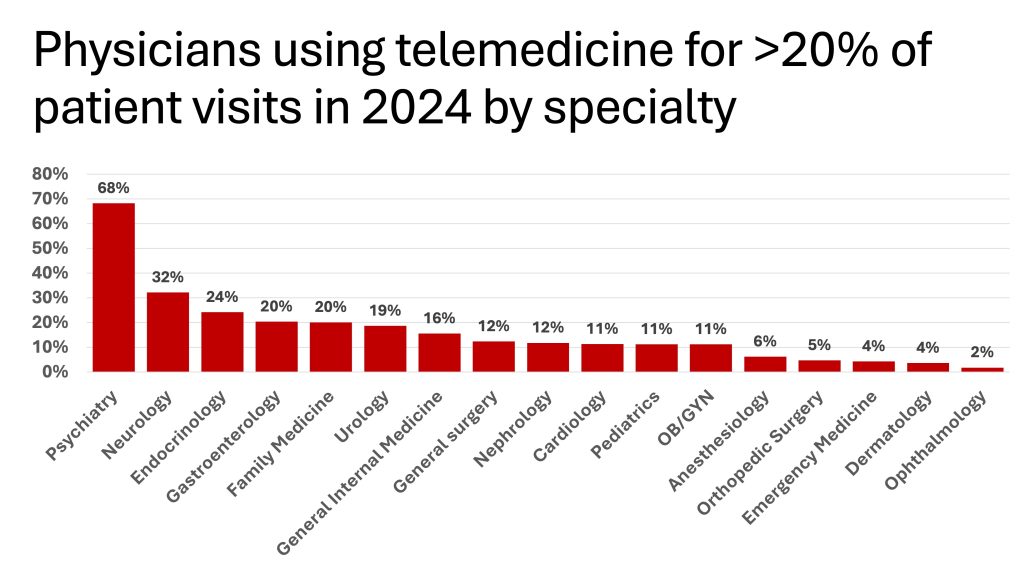
On the surface, it may seem surprising that telemedicine is utilized as much as it is in gastroenterology (20% using telemedicine for more than 20% of encounters), urology (19% using telemedicine for more than 20% of encounters), and general surgery (12% using telemedicine for more than 20% of encounters). However, these procedure-based specialties often schedule post-procedure follow-up encounters to discuss pathology results with patients and these encounters primarily consist of counseling which lends itself very well to telemedicine. In addition, many post-surgical follow-up visits are bundled into the procedure code for the initial surgery and are thus not reimbursed separately. These post-op visits are often used primarily for symptom reporting which can be done by audio telemedicine or simple examination of an incision which can be done by video telemedicine.

Early in the pandemic, both primary care physicians and specialty physicians mostly billed low-complexity encounters for telemedicine. A study from a New York City health system found that primary care physicians billed low complexity E/M codes for most of their new and return telemedicine encounters. On the other hand, as the pandemic progressed, specialty physicians billed moderate complexity E/M codes for most of their new and return telemedicine encounters. Primary care physicians rarely billed high complexity telemedicine E/M codes but specialists billed a significant number of telemedicine encounters as high complexity (albeit fewer than moderate or low complexity).

Unless Congress passes new legislation in the next month, telemedicine will no longer be covered by traditional Medicare for most Americans who are not living in rural parts of the country with access to a local rural health facility that participates in telemedicine with physicians located elsewhere. Behavioral health telemedicine will continue to be covered as this was made permanent by Congressional legislation in 2021 (of note, behavioral health patients must have an initial new patient in-person visit and an annual return in-person visit). Given the popularity of telemedicine, particularly among those with disability, mobility, and transportation limitations, it is hopeful that Congress will pass new legislation to extend traditional Medicare coverage for telemedicine or make telemedicine coverage permanent. Even if Congress fails to pass an extension, many Medicare Advantage Plans (Medicare Part C) may continue to cover telemedicine since these plans are administered by commercial insurance companies that have the freedom to cover or not cover telemedicine at their own discretion. Similarly, state-specific Medicaid plans and regular commercial health insurance plans may elect to continue telemedicine coverage for their enrollees.

This could result in a patchwork of telemedicine coverage with some patients within a medical practice being eligible for telemedicine coverage and others not eligible. Physician practices will then need to decide if they will offer telemedicine to those patients who do have insurance telemedicine benefits. This would require schedulers to determine whether or not each individual patient is eligible for telemedicine based on their specific health insurance coverage. Some practices may find that it is simpler to just not offer telemedicine to any patients rather than risk denials of bills for telemedicine encounters if a particular patient’s insurance plan no longer covers telemedicine after January 30, 2026.

Even if Congress lets Medicare telemedicine coverage expire in January 2026, patients in certain rural areas will still be eligible for telemedicine coverage based on the pre-pandemic telemedicine rules. However, these rural patients would now be required to go to a local rural health facility for their telemedicine encounter instead of having the telemedicine encounter in their own home. In addition, telemedicine could still be used for post-procedure and post-surgical follow-up encounters when those encounters are bundled into the procedure CPT code and not billed separately.

For now, physicians should not schedule telemedicine encounters for patients with traditional Medicare beyond January 30, 2026. Patients with Medicare Advantage Plans, with state-specific Medicaid plans, and with commercial health insurance policies should be scheduled on an individual basis, depending on whether or not their specific insurance carrier has agreed to continue telemedicine coverage after the telemedicine provisions for traditional Medicare expire. Uninsured patients can continue to be scheduled for telemedicine encounters since these patients pay out of pocket (or do not pay at all) and are thus not subject to Medicare telemedicine coverage rules. Post-procedure telemedicine encounters can continue to be scheduled for all patients if those encounters are bundled into the procedure CPT code, unless the specific code dictates that an in-person post-procedure visit is mandated. Neurologists and endocrinologists will be particularly impacted since these specialties have the greatest penetrance of telemedicine in their practices.

All physicians who use telemedicine should advocate for Congress to make Medicare telemedicine coverage permanent since telemedicine has become particularly beneficial for patients who are disabled and who otherwise have mobility and transportation barriers to in-person office visits.

December 27, 2025

Categories
Electronic Medical Records Outpatient Practice

One Simple Way To Reduce Your Electronic Medical Record In Basket Load

How a physician writes for prescription refills can save that physician a lot of time. I have written tens of thousands of prescriptions over my career, a lot of those were handwritten on prescription pads. I am a member of an increasingly small minority of physicians – those that practiced medicine before the era of the electronic medical record (EMR). When our hospital first contracted with the electronic medical record company Epic, there were many tasks that became much easier and more efficient but there were other tasks that became more difficult and time consuming. The ability to send medication prescriptions electronically to pharmacies was the single greatest benefit.

Before the EMR, I would go through dozens of pads of paper prescriptions every year. I would generally write slowly with big block letters that could be easily read by the pharmacists. But many physicians had notoriously sloppy handwriting with the results that pharmacists would frequently call the physician’s office to clarify a prescription or make their best guess about what the written prescription actually meant (and sometimes got the medication or dose completely wrong). The EMR with its electronic prescription capability changed all of that and allowed physicians to do with a couple of mouse clicks what previously took 30 seconds of handwriting. For my outpatients who came in once a year for an annual visit, I would give them 30-day prescriptions with 11 refills. If they were on a 90-day prescription plan, then I would give them 3 refills.

Intuitively, that should have been enough to get them through the full year until they came in for their next annual visit. But a year after we implemented our electronic medical record, I started noticing that my in basket was regularly filling up with prescription refill requests from patients or their pharmacists.

Doing prescription drug refills outside of a regular office visit is inefficient. You have to do at least a minimum of medication reconciliation for each drug that involves verifying that you are actually the physician prescribing that medication, that the patient still actually needs the medication, making sure that no one else has prescribed another medication that either duplicates or interacts with that medication, and making sure that a new drug allergy has not been entered into the EMR since the patient’s last visit. This all takes time and that time is not reimbursable.

A second thing I began to notice after our EMR had been up and running for about a year was that when patients came in to see me for routine office visits for their pulmonary disease, they would sometime ask me to refill their non-pulmonary medications because they were going to run out of refills a few weeks before their next annual visit with their primary care physician. I found myself prescribing a month’s worth of everything from anti-hypertensives to heart failure medications to Viagra to get the patients through until their next office visit with their other physician. So, what was going on?

Prescribing either a 30-day prescription with 11 refills or a 90-day prescription with 3 refills is a total of 360 days of medication. That is 5 days short of a full year. Moreover, most patients do not come in for their annual visits at exactly 365 days from their previous visit. Most scheduling staff will look for open appointments after 365 days and that generally results in patients being scheduled several days or weeks after the exact 365 day number for their next annual visit. Furthermore, most people do not know their exact weekly schedule 365 days in advance – vacations, work conflicts, weddings, and the kid’s soccer tournament often necessitate re-scheduling the annual office visit. This causes that annual visit to be pushed back even further beyond 365 days. The bottom line is that patients were running out of their year’s worth of refills before their yearly office visit.

In most states, pharmacists are permitted to refill prescriptions for non-controlled medications for up to 12 months. Therefore, by writing a 30-day prescription with 12 refills, that last refill would theoretically be 5 days before the 12 month limit was reached. That would give you and the patient a 25-day window after 365 day mark for that annual visit. It is far more efficient to refill medications at the time that the patient is physically in the office for their regular visit. Moreover, the writing of a prescription (or refilling a previous prescription) can add to the complexity of that office visit, allowing the physician to bill a higher (and justifiable) level of service.

For 90-day prescriptions, if you write for 4 refills, that last refill will be at 360 days (five days before the 12-month refill limit). That gives you and your patient an 85-day window for that annual office visit after the 365-day, 1-year mark. In my own practice, I was almost always booking out more than a month for available return office visits and having that 85-day grace period for medication refills allowed my patients to re-schedule their annual appointments without running out of medications.

The result was that my in basket got a lot less congested with medication refill requests once I put that extra refill on long-term prescriptions. I was happier because my in basket was de-bulked, my patients were happier because they didn’t have to worry about running out of their inhalers, the pharmacists were happier because they didn’t have to take their valuable time calling my office for a refill request, and my office staff were happier because they didn’t have to deal with patients and pharmacists calling our office for refills.

But there is a downside. Anyone who has ever taken a prescription medication has had the experience of getting to the end of the month and finding that there are 3 or 4 pills left in the bottle. It is really, really easy to forget to take a dose, or two, or five each month. So, if left to the patient to go to the pharmacy every 30 days, the patient will invariably go at 32 or 33 days and by the end of the year, they will show up for their last refill a few days after their 12-month (365 day) refill limit. Therefore, whenever possible, get the patient on a 90-day prescription plan, preferably from a pharmacy that mails the the patient their medication refills automatically every 90 days.

Always write long-term prescriptions as 30-days plus 12 refills. Or better yet, write 90-day prescriptions with 4 refills.

July 29, 2025

Categories
Inpatient Practice Outpatient Practice

20 Warning Signs When Interviewing Doctors For A Job

Over 33 years of practice, I’ve interviewed hundreds, if not thousands of doctors – from residency applicants, to fellowship applicants, to hospitalists, to specialists, to medical directors, and to CEOs. And I’ve missed some things, sometimes really, really important things, that have come back to haunt me later on. Here are some of the warning signs that the doctor that you are interviewing is going to end up being a problem after he or she is hired.

  1. They’ve been arrested for something. Most hospitals will have some question on the application like “Have you ever been convicted of a crime other than minor traffic violations?“. We hired a doctor who truthfully answered “no” to that question but he had actually been accused by multiple women of lewd behavior and sexual assault. In fact, there were plenty of articles about him in his local newspaper that I only found out about after we hired him (we suspended and then fired him as soon as we knew about it). I learned my lesson and started Googling every candidate’s name with associated key words like malpractice, crime, and lawsuit. On several occasions, I found out that physician applicants were involved in multiple civil suits or had been indicted but not convicted of serious crimes. The lesson is, always Google the applicant.
  2. Stuff they post on social media. I personally do not have a Facebook, Instagram, or X (Twitter) account and really don’t have any use for them. But you can learn plenty about me by my blog posts. If the applicant has social media accounts with public access, always see what they have to say and what pictures they post. You don’t want to hire a doctor that regularly re-tweets racist tweets or a doctor who proudly posts pictures of himself passed out drunk at a party.
  3. Swastika tattoos. Job applicants usually keep their tattoos covered up during interviews and then you don’t know what is tattooed on their forearms until they are wearing scrubs in your ICU 6 months later. Most people take no more note of the details of tattoos than they would the print details on a necktie or blouse. But a person’s tattoos tell you a lot about them. If an applicant’s tattoos are visible, take a careful look at them to be sure that they won’t be offensive if viewed by hospital staff or patients. Don’t hire a doctor with a naked woman tattoo visible on his arm or any kind of tattoo that could be seen as racist, political, or otherwise socially unacceptable.
  4. Time period gaps. Most job applications require the applicant to list the dates of the training programs and previous jobs that they have held. From that you should be able to construct a timeline of everything that applicant has done since graduating from high school. Gaps in time are a red flag and you need to specifically ask the applicant what they were doing during those time periods. Usually, these gaps are innocuous: studying for a board exam, maternity/paternity time, etc. But the chances are that the applicant is not going to list on the CV the 4 months that they were in a mental hospital because of catatonic schizophrenia.
  5. Drug and alcohol convictions. Most physician job applications have a check box with a question something like “Have you ever been addicted to alcohol or drugs?“. Many applicants will check the “no” box for that question because they don’t consider themselves to have an alcohol or drug problem. But the applicant who has had 3 DUIs has an alcohol problem no matter what the applicant thinks and you shouldn’t hire that physician unless he/she has completed an alcohol rehabilitation program. I had one physician applicant who had been arrested twice for DUI violations but in both cases, his attorney was able to get the charges dropped on technicalities so they did not show up on his job application. It is best to have a question like: “Have you ever been charged with a DUI offense or illegal drug offense?”.
  6. Always call the professional references. As a species, doctors usually write positive or at least neutral letters of recommendation for their colleagues. Sometimes, it is because we are trying to get rid of a problem doctor by helping them get a job elsewhere. Professional references will usually give you a more honest opinion if you call them on the phone and speak with them confidentially. One of our particularly problematic division directors looked great on paper and her reference letters were all fine. It was only after we hired her and someone ran into a couple of those references at a medical meeting that we found out that she was abusive, didn’t get along with anyone, and entire medical staff was delighted to see her leave their hospital. If a doctor’s professional references won’t return your calls, that should also be a red flag – it may mean that they are trying to distance themselves from that particular physician. Also, beware of the applicant who only lists references from many years ago – it may mean that the applicant has developed personality problems that any recent reference would have mentioned.
  7. They make jokes that aren’t funny. A fellowship applicant once told me during the interview that he wanted to become a critical care physician “Because critical care is like internal medicine on crack!“. OK, so exactly how do you know what being on crack is like? We didn’t hire him.
  8. They failed their board exam the first time they took it. I get that not everyone passes the board exam on the first go. People sometime have bad days – maybe they were up all night the night before the exam because one of their kids was sick. Or maybe they had a recent death in the family. But doctors have to re-take board exams every 8-10 years and if they can’t pass those recertification exams, they won’t be board-certified. And if they aren’t board-certified, they can’t stay on the hospital medical staff. At the least, doctors who fail the board exam once will likely need your attention in the future to ensure that they go to board preparation courses, etc. so that they don’t fail their future recertification exams. I’ve had to personally tutor hospitalists who failed their internal medicine board re-certification exams in order to help them pass them the second time around and to keep them on our medical staff.
  9. They move around a lot. There are several reasons why a doctor might change jobs frequently. Sometimes it is because they have a spouse who has to relocate frequently because of job transfers. But sometimes it is because they are ambitious and trying to rapidly climb the medical leadership ladder. And sometimes it is because they can’t get along with doctors and nurses at all of their previous jobs. Regardless, the doctor who frequently changes jobs warrants scrutiny. If it is because of ambition, then that doctor may do a great job for you but will likely leave for the next promotion opportunity in a year or two. If it is because they don’t get along with others, then you’re going to spend an inordinate amount of time doing conflict resolution if you hire them.
  10. They cleaned out the hotel minibar. We interviewed a moderately famous physician for a division director job. She looked great on paper and interviewed well over the 2-day visit. When we got the bill for her hotel stay, there was a huge charge for the hotel minibar. It turns out that she packed up everything in the minibar and took it with her when she left. We didn’t ask her back for a second interview.
  11. They are too successful in research. In academic medicine, we frequently judge physician candidates for leadership jobs by their research productivity. After all, it is easy to quantify research success based on a candidate’s number of grants and publications. But all too often, successful physician researchers make terrible leaders. Research success is all about your own personal accomplishments. But success in leadership is all about fostering accomplishments of everyone around you. I interviewed a candidate for the chairman of a different department who had an enormous CV full of millions of dollars of research grants and publications numbering in the hundreds. Although he interviewed well, I was very skeptical and gave him a thumbs down. But the dean of the college wanted him in order to bolster the department’s research productivity. Within 6 months of arrival, he was fired because he completely mismanaged the clinical activities of the department and belittled the clinical faculty as second class citizens compared to the research faculty. With the department losing money from declining clinical revenue and unhappy physicians leaving the department, the dean had no choice but to remove him and start the job search all over again. Division directors, department chairmen, and deans get their jobs based on their research success but lose their jobs based on their financial failures.
  12. They say dumb stuff at the recruitment dinner. I have a personal rule for recruitment dinners – get a non-alcoholic beer when no one is watching. That way, everyone thinks I’m drinking but I’m actually trying to keep my mind sharp so that I can observe the candidate’s behavior. If I can’t get a non-alcoholic beer without others knowing it, I order a beer that I don’t particularly like and nurse it all evening. Candidates usually let their guard down at dinner and it gives you a better idea of how they are likely going to behave in the hospital. If they are rude to the restaurant staff, they’ll be rude to the hospital staff. I was at a recruitment dinner once when the doctor called the waiter over to tell him that table’s bottle of wine was “corked” (i.e., suffered from cork taint) – she might has well stood on a chair and shouted: “I’m a prima donna!“. We didn’t hire her.
  13. They ask inappropriate questions. I interviewed a division director candidate once who looked very promising on paper and had a long list of publications. We had hired a search firm to help identify candidates and the firm’s consultant told me that this particular physician was the best candidate he had seen in years. During his interview, the candidate asked me whether as the division director, he would be allowed to put his name on all of the articles published by the division’s faculty members. That questions showed that he saw the job as a means for his personal benefit and not as a means of benefiting anyone else around him. We hired someone else.
  14. They don’t make eye contact during the interview. I think I’m pretty good at recognizing overt psychopathology during an interview but I have more difficulty recognizing more subtle personality disorders. One of the things that I can reliably judge during the interview is communication skills. If candidates babble on and on during the interview, they will babble on and on during teaching rounds and faculty meetings. If they don’t make eye contact with you as an interviewer, they likely won’t communicate well with patients, either.
  15. They talk down about their previous or current employer. I acknowledge that physicians usually change jobs because the new job offered something more than the last job. The emotionally mature candidate will put their desire for a job change as a positive, such as “I’ve had a good job at my current hospital but I see more opportunities to grow professionally at your hospital.” The candidate that says derogatory things about their current or past employer will have no qualms about saying derogatory things about you.
  16. They don’t dress the part. I don’t expect a physician candidate to come wearing a tuxedo or an evening dress but I do expect at least a minimum of formality in attire. I had a hospitalist candidate show up for his interview wearing jeans, an untucked golf shirt, and sneakers. I figured if he showed up that way for his interview with me, he would likely show up that way to take care of patients. We didn’t hire him.
  17. They show up late. Okay, I accept that there can be traffic jams, canceled flights, and car flat tires. But a candidate that is late for the interview better have a really, really good excuse. Otherwise, that candidate is also going to be likely to show up late for work, for meetings, and for rounds.
  18. They focus too much on time off and salary. I understand that these are questions on every candidate’s mind but the initial job interview is not the time to be excessively asking about the number of vacation days and salary structure. It comes across as pointing toward the candidate as a potential problem child, and not a team player.
  19. They run another business. Personally, I like it when physician candidates have outside hobbies and activities. I think they keep the physician grounded and help promote sanity. But a second job can become a time conflict. I interviewed a division director candidate who had started a company manufacturing a medical device that he had designed. He was world famous and had a lot of invited lectures on his CV. I was skeptical but we hired him anyway. He continued to travel regularly for invited lectures and company board meetings to the point that he was gone from the hospital more than he was there. One night when he was on call, I was covering our ICU and I paged him – he was in another state. I like physician candidates who are mildly famous, but not too famous. A second job can be a conflict of time.
  20. Expertise out of proportion to typical training experiences. I had a family medicine residency graduate who was interviewing for a hospitalist position claim that he had performed dozens of central venous catheter placements, arterial lines, and endotracheal intubations. He even produced procedure logs as confirmation. Family medicine residents rarely have this much experience performing ICU procedures. But things seemed in order so we hired him and credentialed him for those procedures. Within weeks, he had left a guide wire in a patient during a central line placement and caused a pneumothorax during another line. He repeatedly needed to call for back-up after inability to successfully place endotracheal tubes in emergencies. I suspect that he doctored his procedure logs from residency. We let him go before the end of his probationary period.

March 11, 2025

Categories
Outpatient Practice

What Physicians Need To Know About Compounding Pharmacies

A regular retail pharmacy sells drugs that are made by a pharmaceutical company. A compounding pharmacy is one that makes its own drugs from a group of chemical ingredients. Compounding pharmacies play an important role in American medicine but can be riskier to use than a regular retail pharmacy. Compounding pharmacies account for about 3% of prescription drugs sold in the United States. Some of the reasons physicians may utilize a compound pharmacy are:

  • An FDA-approved drug is not available in the best form for a patient. This is a common problem, for example, a patient cannot swallow pills and a certain medication is only available from pharmaceutical companies in pill form. In this case, the compounding pharmacy may create the medication in liquid form for that specific patient. Another common reason for compounding is to make put a drug in an ointment or cream for a dermatologic indication.
  • A drug needs flavoring for a child. Often, children won’t swallow medication if it tastes bad. A compounding pharmacy can often make the same medication with a fruit flavoring or sweetener added to it.
  • An FDA-approved drug has an inert ingredient that a patient is allergic to. I had this problem with a patient who was allergic to a dye used in the tablets of a certain drug. A compound pharmacy was able to make the same medication with no dye added.
  • A patient needs a dosage that is not in commercially available pills or capsules. In this case, the compounding pharmacy can create a customized dose of a drug in a capsule for a patient.
  • Consolidating multiple medications into one dose. For example, if a patient needs to take 3 different medications every day, the compounding pharmacy may be able to create one capsule containing all three drugs to simplify administration and improve patient compliance.
  • An FDA-approved drug is no longer being manufactured commercially. This can happen if the demand for a specific drug falls so that it is no longer financially profitable for a pharmaceutical company to continue manufacturing it.
  • Your pet needs a drug. Many medications used in humans are also used in dogs and cats. But that pet may require a different dose than is available for humans or may need the drug in a different form to administer to the animal.
  • A commercially available drug is on the FDA’s drug shortages list. When pharmaceutical companies are unable to manufacture enough of an FDA-approved drug to meet market demand, compounding pharmacies are allowed to make equivalent medications. This can happen because the pharmaceutical company has not ramped up production sufficiently or because there is a problem with the manufacturing facility (such as a fire or hurricane damage to the facility).

Many regular retail pharmacies will offer compounding services for simple compounding, such as converting a medication in capsule form into a liquid form. I have frequently had local pharmacies do this for patients with G-tubes who cannot take medications by mouth and can only take them in a liquid form through the feeding tube. But recently, there have been on-line compounding pharmacies that make copies of brand name drugs and often have their own employed physician who will prescribe the compounded drug over the internet to the patient.

The biggest risk to using a compounding pharmacy is that the compounded drug that they sell is not FDA-approved and the FDA does not have oversight to the mixing process or the labeling. Therefore, there can be issues with the drug’s purity, safety, or effectiveness. For example, in 2012, the New England Compounding Center produced a form of methylprednisolone for epidural injection that was contaminated with a fungus. 798 people developed fungal meningitis from Exserohilum rostratum and Aspergillus fumigatus. 64 of these infected patients died. Last year, tirzepatide produced by a compounding pharmacy was found to be contaminated by bacteria (tirzepatide is the chemical name for the commercially available drugs Monjaro and Zepbound).

Compounded drugs are not always as potent as the FDA-approved brand name drug. For example, in 2023, it was found that some compounding pharmacies making semaglutide (the chemical in the brand named drug, Wegovy) were using semaglutide sodium and semaglutide acetate which are salts of semaglutide that have not been proven safe or effective. Sometimes compounded drugs may come in different concentrations than the brand name drug, creating the possibility that patients can miscalculate and accidentally take too much or too little of a dose.

Currently, there are a lot of television ads for Hims.com, an on-line compounding pharmacy that advertised during the Super Bowl. Companies such as this allow people to enter some basic medical information on-line and then a prescriber working for the company can order compounded versions of drugs for conditions such as weight loss, erectile dysfunction, anxiety, and hair loss. These compounded drugs are often much cheaper than the commercially-available brand name medications that a person would buy at a retail pharmacy. Also, some people want to avoid the embarrassment associated with discussing their weight or sexual problems with their regular doctor and feel more comfortable with the anonymity of on-line prescribing.

From a treating physician’s standpoint, the biggest problem I have with patients using compounding pharmacies is that I don’t know what drugs the patients are getting. We normally go to great lengths to do “medication reconciliation” to ensure that we have an accurate list of a patient’s medications. Our electronic medical records are where this reconciliation occurs and if we don’t have a medication listed in the electronic medical record, there is no way for us to know if that medication causes dangerous drug interactions with the medications we prescribe or if that medication is responsible for new symptoms that are side effects of that medication. Similarly, the provider working for the on-line compounding pharmacy cannot access our electronic medical record and consequently cannot be sure of what medications I have already prescribed for the patient or what medical conditions I have diagnosed the patient with. The result is that patients can be harmed when information falls through these cracks.

The compounding pharmacies do not fall under the FDA’s jurisdiction. That means that the FDA has not done independent testing to ensure a compounded drug is safe or that the dose is correct. Instead, compounding pharmacies are licensed and overseen by the department of health of the state that the compounding pharmacy is located in. Every state’s department of health is different – there are different state-specific laws, different degrees of health department staffing, different frequencies of facility inspection, and different degrees of oversight between states. For this reason, there is no way of knowing if an out of state compounding pharmacy is being held to the same standards that it would be if it was in your own state. Like many businesses, compounding pharmacies often gravitate to states with the fewest regulations.

Compounding pharmacies cannot sell a drug under its brand name and instead can only use the drug’s chemical name. Thus, the compound pharmacy will use the chemical name semaglutide but not the brand names Ozempic or Wegovy. The price difference can be dramatic – Wegovy costs just over $5,000 for a 3-month supply without insurance whereas compound pharmacies sell compounded semaglutide for $750 for a 3-months supply on-line.

Importantly, compounded drugs are not generic drugs. The FDA regulates and approves generic drugs that are manufactured by a pharmaceutical company and sold at a lower price than brand name drugs. This typically happens when a drug’s patent expires. Generic drugs are sold in regular retail pharmacies. Since generic drugs are overseen by the FDA, you can be reasonably confident that the drug is pure, it is safe, and the dosage is accurate.

To create a drug like Wegovy requires years of research that can cost hundreds of millions of dollars. The United States recognizes this and will grant pharmaceutical companies patents on new drugs for 20 years. This gives the pharmaceutical company 20 years to recoup their research and development cost as well as make a profit. Once that patent expires, other pharmaceutical companies can make and sell generic forms of that medication.

Compounding pharmacies can bypass the patent protection by making copies of a drug when the FDA determines that there is a national shortage of that drug. This can erode the pharmaceutical company’s marketshare of a patented drug and lower profits. Needless to say, pharmaceutical companies want their patented drugs to get off of the FDA’s Drug Shortages List as quickly as possible so that compounding pharmacies cannot produce copies of their drugs. This leads to arguments between the pharmaceutical companies and the compounding pharmacies about whether the pharmaceutical company actually has enough supply of a drug to meet demand. The compounding pharmacies will accuse the pharmaceutical company of underestimating demand and the pharmaceutical companies will accuse the compounding pharmacies of overestimating demand. The FDA then gets caught in the middle trying to make a decision.

Eli Lilly’s drugs Zepbound and Mounjaro were taken off of the FDA’s Drug Shortages List last October and compounding pharmacies then had to stop manufacturing compounded tirzepatide. Last month, the FDA determined that Novo Nordisk’s drugs Ozempic and Wegovy will be taken off of the Drug Shortages List so compounding pharmacies have been given 6 months to stop producing compounded semaglutide. Last week, the Outsourcing Facilities Association, a compounding industry group, filed a lawsuit against the FDA in order to put Ozempic and Wegovy back on the Drug Shortages List so that they can continue to create compounded versions of the drugs.

Whenever possible, tell patients to get their medications at a regular retail pharmacy in either brand name or generic form. When compounding cannot be avoided (for example, getting a drug in liquid form that is only commercially available in tablet form), then use a pharmacy that you trust – either a retail pharmacist or a local compounding pharmacy that you are familiar with. Avoid using on-line compounding pharmacies for drugs that patients can otherwise get at their regular retail pharmacy.

This usually is not a problem when a drug is covered by a patient’s health insurance plan – all the patient will be responsible for is a (usually) low co-pay. It can be a problem when a drug is not covered on a patient’s health insurance formulary, if the insurance company will not approve the drug for the patient’s specific condition, or if the patient does not have health insurance. In these cases, the physician needs to weigh the risks and benefits of a compounded drug for the individual patient. On the one hand, there is no guarantee of the compounded drug’s purity or effectiveness. On the other hand, the patient may not be able to afford the drug produced by a pharmaceutical company and sold in a regular retail pharmacy.

The GLP-1 receptor agonist drugs are the quintessential example – most insurance companies will only cover them for diabetes and not for general weight loss indications. For a patient without diabetes who wants to take a GLP-1 drug to lose weight, the annual cost of the drug made by a compounding pharmacy is about $3,000 whereas the annual cost to buy the drug made by a pharmaceutical company is about $20,000. Many patients will accept the risk of the compounded drug since it will cost them $17,000 a year less. From a physician’s perspective, the health risk of untreated obesity may be greater than the risk of the compounded drug.

Most importantly, be sure to get drugs patients acquire from compound pharmacies onto your electronic medical record. This means asking your patients specifically if they are getting medications from on-line pharmacies. The electronic medical record will identify common drug interactions and can prevent serious harm from patients, but only if the drugs patients are actually taking are entered into the EMR. No physician wants to be caught by prescribing nitroglycerin to a patient who has been getting tadalafil (Cialis) from an on-line pharmacy and then having the patient have a cardiac arrest from sudden hypotension cause by the interaction of the two medications.

March 1, 2025

Categories
Outpatient Practice

Screening Cholesterol Levels Is Not Enough – Measure Lipoprotein (a) In Everyone

We’ve all seen this patient – the one with a normal cholesterol level and no apparent cardiovascular risk factors who gets admitted with a myocardial infarction at age 50. For years, we had no explanation for why someone so healthy would get such bad coronary artery disease. But now, we do – that explanation is lipoprotein (a). And now, we have treatments that can lower lipoprotein (a) levels and reduce the chances of a heart attack or stroke later in life.

Lipoprotein (a) is composed of an LDL particle with a large glycoprotein called apo(a) wrapped around it. The concentration of lipoprotein (a) in the blood is controlled by the LPA gene on chromosome 6. Heritable variations in this gene result in higher or lower lipoprotein (a) levels. As a result, if a person inherits a certain variation of the LPA gene, that person will have high blood concentrations of lipoprotein (a). About 20 – 30% of humans have elevated lipoprotein (a) levels and these persons are at increased risk of atherosclerosis. People of African descent typically have 2-3 times higher blood levels of lipoprotein (a) than people of European or Asian descent.

Lipoprotein (a) is produced by the liver and then released into the blood. It is excreted or metabolized by the kidney with the result that kidney disease causes the lipoprotein (a) blood levels to increase and liver disease causes levels to decrease. A diet low in saturated fats can also decrease lipoprotein (a) blood levels, but only modestly.

Historically, blood test screening for cardiovascular risk assessment consisted of measuring total and LDL cholesterol levels. People with high LDL levels are usually recommended to start statin medications to reduce their blood cholesterol and thus reduce their risk of atherosclerosis. But it appears that lipoprotein (a) levels may be just as important as LDL levels when it comes to cardiovascular risk. However, most primary care physicians have not been routinely screening patients for elevated lipoprotein (a) levels. This needs to change and I believe that every American should have their lipoprotein (a) level tested once in their life, preferably in their 20’s or earlier, before the onset of atherosclerosis.

Statins are great at reducing LDL cholesterol levels but they have a minimal effect on lipoprotein (a) levels. In the past, that was a major reason why physicians did not regularly do screening lipoprotein (a) levels – the thought was: “If I can’t do anything about it, why test for it?” But there are compelling reasons to test patients because there is something we can do about it and those treatment options will be increasing in the near future. Here are some of the things you can do for your patients with high lipoprotein (a) levels:

  • Have a lower threshold for starting statins. Currently, statins are recommended for any adult with an LDL cholesterol level above 190 mg/dL. For those with other cardiovascular risk factors putting them at high risk, the LDL cholesterol threshold for statins is 70 mg/dL. The lipoprotein (a) level should be included as one of these other cardiovascular risk factors and patients should be started on a statin if their LDL cholesterol is above 70 mg/dL and also have a lipoprotein (a) level above 50 mg/dL. The statin may not lower lipoprotein (a) levels but by reducing LDL cholesterol levels, the statin can reduce one’s cardiovascular risk.
  • Have a lower threshold for starting anti-hypertensive medications. Currently, an out-of-office daytime blood pressure ≥135 mmHg systolic or ≥85 mmHg diastolic is considered indications for starting medication for hypertension. Lower blood pressure thresholds are used if patients have additional cardiovascular risk factors such as diabetes, kidney disease, or age over 65. Consider starting anti-hypertensive medications in patients with an out-of-office daytime blood pressure ≥130 mmHg systolic or ≥80 mmHg diastolic if their lipoprotein (a) level is greater than 50 mg/dL.
  • Stronger lifestyle modification recommendations. Some people can get away with being obese, smoking, or a high saturated fat diet. Those with a high lipoprotein (a) level are not these people and need to be told that stopping smoking, keeping their BMI below 30, and eating a diet low in saturated fats is essential to avoiding cardiovascular disease.
  • Screen the family. Because lipoprotein (a) levels are determined by inherited genes, if one family member has high levels, it is likely that other family members do also. Advise patients that they have a genetic condition that increases the risk of cardiovascular disease and that they should tell their first degree relatives to get their own lipoprotein (a) level tested.
  • PCSK9 inhibitors. Recently, drugs that can reduce lipoprotein (a) levels by 25% have been approved. These include the monoclonal antibodies, evolucumab (Repathа) and alirocumab (Praluent). These drugs have their FDA indications for secondary prevention of atherosclerosis and for familial hypercholesterolemia so treatment of elevated lipoprotein (a) levels is currently considered an off-label indication. This can make insurance coverage difficult by some health insurance companies.
  • Lipoprotein apheresis. This is the only FDA-approved treatment for elevated lipoprotein (a) levels and can reduce those levels by 75%. However, aphaeresis must be performed weekly, making it both inconvenient and very expensive for the patient. My suspicion is that most health insurance companies if given a choice between paying $2,500 per week for apheresis or paying $340 every two weeks for Repatha will approve off-label use of Repatha in order to avoid paying for apheresis.
  • Pelacarsen. This is an investigational anti-sense medication that targets messenger RNA for lipoprotein (a) and can reduce levels by 50%. Phase 3 studies are underway and FDA approval could come later this year.

Because a person’s lipoprotein (a) level remains constant throughout life after age 5-years-old, there is no reason to wait until patients are elderly or already have heart disease. Instead, consider testing patients in their 20’s or even earlier in order to encourage a life-time of heart healthy lifestyle changes. The only caveat is that is best to screen patients when they are healthy and not during periods of inflammation, kidney disease, or liver disease since these conditions can affect lipoprotein (a) levels. Most commercial labs will perform lipoprotein (a) tests for $30 – $50 without an order from a person’s doctor. Physician-ordered tests that are run through a patient’s insurance may be even less expensive.

Many physicians rely on the United States Preventive Services Task Force (USPSTF) recommendations when deciding what patients should be screened for what diseases. Currently, the USPSTF has no recommendations about screening patients for elevated lipoprotein (a) levels. But other organizations do have recommendations. For example, the National Lipid Association recommends measuring lipoprotein (a) at least once in every adult. The European Atherosclerosis Society also recommends testing all adults at least once. The American College of Cardiology recommends testing all individuals with risk factors for cardiovascular disease once in a lifetime. The USPSTF generally bases its guidelines on recommendations from specialty societies, it is likely that the USPSTF will include recommendations for lipoprotein (a) screening in the future. But as I see it, there is no reason to wait for the USPSTF, go ahead and start screening all patients now.

February 13, 2025

Categories
Outpatient Practice

Physicians Should Promote Over-The-Counter Influenza Testing

When the COVID history books are written, one of the good things to come out of the pandemic is the public’s successful use of home antigen testing for viruses. Forty years ago, if you wanted any kind of diagnostic medical test, you had to go to a doctor. The U.S. Food and Drug Administration (FDA) took the position that the general public was just not sophisticated enough to perform any kind of home testing. Then, in 1976, the FDA made a ground-breaking approval of e.p.t. – the Early Pregnancy Test which became the first over-the-counter pregnancy test that anyone could do. By 1988, 33% women of child-bearing potential had used a home pregnancy test. Today, global annual sales of home pregnancy tests are $705 million and they are well-accepted for their ability to accurately identify pregnancy as early as a week after conception.

Home glucose testing followed a similar timeline. The first glucose test strip, Dextrostix, was developed in 1965 and for the next fifteen years, the use of test strips was limited to physician offices. In 1980, the Dextrometer was launched and home glucose testing rapidly became the standard of care.

But it wasn’t until the COVID pandemic that home testing for an infection became available. Indeed, the home tests for COVID became one of public health’s most valuable tools to identify infections early in order to isolate contagious persons and slow the infection rate in communities. I can remember the earliest COVID home tests that required a person to use a camera on a phone or computer to link with a person trained in proctoring the steps in testing and in interpretation of the results. Those test kits gave way to tests that anyone could do on their own, without telemedicine proctoring. It turned out that the general public was more sophisticated than the health community had thought and were able to correctly perform and interpret these tests without proctoring.

Labcorp’s Pixel test can diagnose RSV and influenza infection in addition to COVID. Anyone can buy an over-the-counter Pixel test and do the nasal swab themself at home; however, it must be mailed to Labcorp for analysis and the results can take 2 days to come back. This delay of 2 days to make a diagnosis renders Pixel of limited use since rapid influenza tests can be performed in a doctor’s office in a matter of minutes. Thus, if a person is worried that they have influenza, it is far more expedient to go to their doctor, an urgent care center, or an emergency department for a rapid flu test.

Last year, in February 2023, the FDA approved Lucira, a home test for both COVID and influenza. This test, produced by Pfizer, correctly identified 90% of positive influenza A samples and 99.3% of negative influenza A samples. Lucira also detects influenza B but there were few cases of influenza B circulating at the time that Lucira was tested for accuracy. Unlike Pixel, Lucira tests are done by having the person do their own nasal swab and then perform testing and test interpretation themselves. The test requires a battery-powered device to analyze the specimens (the device and batteries are included in the Lucira kit). The total amount of time to perform the nasal swab and run the test through the device is about 35 minutes. Lucira is available through Amazon and costs $50 for one test kit. You can read the full kit instructions here, at the FDA’s website.

Why aren’t more people using Lucira tests?

Lucira has been a major breakthrough – a home influenza test that anyone can do and get immediate results. Diagnosing influenza early is crucial for infection control and treatment efficacy. You get influenza by being exposed to an infected person’s respiratory droplets. Thus, early diagnosis permits isolation of an infected person so as to reduce the chance of spreading influenza to family members, co-workers, or classmates. We have a very effective treatment for influenza – oseltamivir (Tamiflu), made by Genentech. However, for oseltamivir to be effective, it should be started within 2 days of the onset of influenza symptoms. This limits the usefulness of the Pixel tests since by the time the results get back, it is often too late to start Tamiflu. For these reasons, you would think that Lucira would be flying off the shelves but the reality is that few Americans (including doctors) have even heard of it. So why is it being so woefully underutilized?

  • It is only available through Amazon. In larger communities, Amazon can deliver a Lucira test kit the same day it is ordered. But in some areas of the country, it can take longer. Most people would prefer to stop by their local pharmacy to buy a test kit on-demand when they first develop flu symptoms but you can’t buy Lucira at a CVS or Walgreens. By limiting sales through Amazon, there is an access and time barrier to obtaining a test kit.
  • It is expensive. Personally, I would be more than willing to pay $50 to find out as early as possible if my fever and cough are due to influenza or not. But $50 can be a cost barrier to many people, especially since a COVID-only test kit costs less than $20 (for 2 tests in a kit) at your local pharmacy.
  • It is not being marketed. The American public is inundated with TV commercials for drugs. That’s because there is money to be made when pharmaceutical companies sell more of those drugs. Pfizer has relatively little to gain by selling its Lucira test kits. If Genentech produced an influenza home test kit, it would have an enormous financial incentive in the form of greater sales of Tamiflu from all of those early influenza diagnoses. Pfizer lacks an incentive to put money into advertising Lucira or to reduce the price of Lucira.
  • The public has COVID fatigue. Let’s face it, we’re all tired of COVID and just want it to go away. And the truth is that COVID hospitalizations were lower last week than any week since June 2023. We are also at the end of influenza season and flu cases are dwindling. If you get flu-like symptoms today, it is statistically more likely to be some other respiratory virus that there is no treatment for, anyway. COVID and influenza are out-of-sight, out-of-mind in the American public’s consciousness.

So, what can we do?

I’ve seen many people die from influenza during my career. As a pulmonologist, I know that the best way to reduce the chance that my patients will die from influenza is to diagnose it as early as possible. But I also know that it can be difficult for patients to get in to see a doctor within 48 hours of onset of flu-like symptoms. Patients will often call their doctor or message their doctor through their electronic medical record patient portal when they have flu-like symptoms but most doctors will not prescribe Tamiflu unless they have confidence that the patient actually has influenza as opposed to some other respiratory virus. So, what can we do to improve the use of home influenza testing?

  1. Make it more widely available. Don’t get me wrong, I buy a lot of stuff through Amazon. I’m surprised that Jeff Bezos doesn’t send me a fruit basket every Christmas in gratitude. But by limiting distribution to Amazon, the test kits are just not readily available to many (or most) Americans. Physicians should ask Pfizer to sell Lucira at brick and mortar pharmacies.
  2. Increase competition. Adam Smith, the father of supply and demand economics, identified that the best way to improve the quality and availability of a good or service as well as reduce the price of that good or service is through competition. Right now, Pfizer has a monopoly on the home influenza test kit market and is not incentivized to reduce the cost of test kits or to improve those kits. The FDA needs to authorize home influenza test kits from other manufacturers. It’s industrial competition that makes America great.
  3. Physicians need to educate themselves. We are influenced the greatest when a trusted peer advocates a new test or treatment. This can be through formal educational programs, such as grand rounds, or through informal settings such as department meetings or medical staff meetings. We need to spread the word about the availability of home influenza testing – not only among ourselves but also among our patients.
  4. A perfect opportunity for telemedicine. My inbasket in our electronic medical record was always the bane of my existence. I would tediously clear out all of the test results and patient messages every evening but by the next day, that inbasket would be full again. Physicians don’t like providing health advice or treatment via a patient portal or phone call because it takes up a lot of time and they don’t get paid (or if they do, they get paid very little). But with the expansion of telemedicine reimbursement during the COVID pandemic, a doctor can get paid for their time and expertise while improving the health of their patient expediently. Home influenza testing creates an ideal opportunity to utilize telemedicine – the doctor can observe the patient’s general condition and look at the test result via the video link. If the test is positive, a prescription for Tamiflu can be sent to the pharmacy without the patient having to come to the doctor’s office (and potentially infect patients in the waiting room, the office staff, or the doctor him/herself). Ideally, medical practices should make same-day telemedicine encounters available for any patient with a positive home influenza test. Every hour faster that we can prescribe Tamiflu is better for our patients.

At age 65-years-old, I recognize that I am at higher risk of death or serious illness from either COVID or influenza. Even if the infection doesn’t make me sick enough to be admitted to the hospital, those infections will still make me feel pretty crappy for several days and I don’t particularly like to feel crappy. I’m financially secure enough (and value my health enough) that next fall, when influenza season starts, I’ll spend the $50 and buy a Lucira kit through Amazon and leave it in my medicine cabinet for a year in case I develop symptoms. But I think that we can do better – and by we, I mean doctors, the FDA, and kit manufacturers. I’m hoping that like e.p.t. paved the way for other home pregnancy tests, Lucira will pave the way for other home influenza test kits that are easier to use, more accurate, more available, and less expensive.

April 25, 2024

Categories
Outpatient Practice

Your Hospital Needs Palliative Care Telemedicine

One of the good things to come out of the COVID pandemic was the expanded use of telemedicine. It allowed us to provide on-going care to our patients during lock-down periods early in the pandemic and later allowed us to care for patients who were uncomfortable coming into a place where they could potentially become infected. It became clear from the beginning that some specialties were more amenable to telemedicine than others. Telemedicine was less useful for those visits that require a more detailed physical exam or required in-office procedures. Telemedicine was more useful for those visits that were mainly for counseling. A recent study in JAMA demonstrated the value of telemedicine in palliative care for non-cancer diseases.

The study involved 306 patients two Veteran’s Administration health systems between October 2016 and April 2020. Patients all had either COPD, interstitial lung disease, or heart failure. Patients were randomly assigned to either usual care or a telehealth group that received 6 phone calls from a nurse and 6 phone calls from a social worker. Patients were evaluated with a multi-domain quality of life survey (the FACT-G score) and disease-specific quality of life scores. After 6-months, the telehealth group reported significantly better quality of life than the usual care group. There are several important conclusions we can make about palliative medicine telehealth based on this study:

  1. It does not require expensive specialists. The RN and social worker who performed the telephone calls had 10 hours of training. Physicians who have completed palliative medicine fellowships are in short supply and there are not enough of them to provide telehealth services for all hospitals. Registered nurses and social workers are much more widely available (and less expensive) than board-certified palliative medicine physicians. This study shows that at least some of palliative care telehealth can be provided by RNs and social workers with a minimum of training. This would free up palliative medicine physicians (and nurse practitioners) to provide programatic oversight and to provide selective telehealth encounters when the RN or social worker identified need for advanced care and decision-making.
  2. It works for patients with non-cancer diagnoses. In many hospitals, palliative medicine is largely relegated to the care of patients with cancer. Furthermore, palliative medicine is often funded by the hospital’s cancer program. This study shows that the quality of life of patients with COPD, interstitial lung disease, and heart failure improve with palliative medicine telehealth.
  3. It overcomes transportation and mobility barriers. Patients with advanced COPD, interstitial lung disease, or heart failure generally have limiting dyspnea with exertion and are often on supplemental oxygen. This creates a barrier to traveling to an outpatient clinic site with the result that many patients who could benefit by palliative medicine do not receive it. This is especially true of patients who live a great distance from the palliative medicine clinic location.
  4. It did not affect hospitalization rates. The total number of patients in the study was small with only 154 patients randomized to palliative care telehealth and 152 patients randomized to usual care. The primary outcome for which the study was powered was for quality of life scores and a secondary outcome was hospitalization. At the end of 1 year, 109 of the palliative care group and 119 of the usual care group had been hospitalized, a difference that was not statistically significant. There was also no statistical difference in mortality at 1 year: 6 patients in the palliative care group and 5 patients in the usual care group died. Healthcare utilization, in terms of annual total healthcare costs, was not reported so it is unknown if palliative care telehealth reduced healthcare expenditures.
  5. The population studied was limited to Veterans Administration patients. Care at VA medical centers is very different than care at other healthcare facilities. There is easy access to inpatient and outpatient care. Co-pays and deductibles for medical care are relatively low or waived. Additionally, medications are free or available with a relatively low co-pay. In this study, most patients were male and Hispanic. It is unknown if the results can be extrapolated to a more diverse group of patients or patients at non-VA hospitals.

Advantages of palliative medicine telehealth

Any physician who has ever performed a home visit will tell you that you get important information by seeing the patient in their own home environment that you cannot get when seeing the patient in a clinic exam room. During a video-telehealth visit, you can often get a good idea of the patient’s environment that can clue you into home health needs. Assessment of entry ways, stairs, and bathrooms can indicate measures that can be taken to reduce falls. Assessment of home oxygen equipment can ensure adequate (and safe) oxygenation. The need for durable medical equipment can be identified.

The advantages of using telehealth to reach patients who have mobility, transportation, or geographic distance barriers cannot be overstated. Some physicians will argue that in-person visits for palliative care are superior to telemedicine visits; however, a telemedicine visit is vastly superior to no visit if the patient is unable to come to the physician’s office. This is particularly true for patients with conditions such as end-stage renal disease who are bound to their locality three days a week for dialysis, those who are wheelchair-dependent, and those who have limiting dyspnea on exertion.

During COVID, it quickly became clear that telemedicine was more effective for some specialties than others. Diseases that require the patient to undergo regular testing (blood tests, EKGs, pulmonary function tests, etc.) are not as amenable to telemedicine since the patient must come to the clinic for the tests, anyway. Similarly, diseases that require an in-person physical examination for regular assessment are not as amenable to telemedicine compared to those diseases that only require counseling. Palliative medicine is primarily counseling and generally does not require regular testing or procedures. Thus, palliative medicine is in many ways the ideal specialty to utilize telemedicine.

Telehealth has the potential to reduce palliative medicine outpatient no-show rates. When a patient cancels an outpatient appointment on short notice, there is no bill generated and no income to cover the overhead expense of the clinic or the physician’s salary for that period of time. Even if a patient is feeling too unwell to travel on the day of their office appointment or if their transportation is unexpectedly unavailable, that patient can still have a billable telehealth visit which can reduce or eliminate the financial loss of a late cancellation or no-show.

Paying for it

The recent study does not address cost of care. A disadvantage of using a registered nurse to perform palliative care telehealth is that those encounters are generally not billable. Thus, the funding must come from other sources. Alternatively, telehealth can be performed by a physician, nurse practitioner, or physician assistant who can generate revenue by making it a billable telemedicine encounter. Future studies are needed to determine if per-person annual healthcare costs are lowered by palliative medicine telehealth in non-cancer diseases. If so, then managed care programs and insurance companies could be approached for funding. Similarly, health systems participating in value-based-purchasing models and bundled-care payment models could internally fund palliative care telehealth if it is shown to be reduce hospitalizations or annual cost of care.

Palliative medicine is rarely financially self-sufficient. In most hospitals, palliative care is heavily subsidized by the hospital since it is not possible to cover the salary of palliative medicine physicians or advance practice providers on professional revenue billing alone. This study has shown that palliative medicine telehealth improves patient quality of life. However, the current U.S. healthcare system does not pay hospitals to improve quality of life. Hospitals get paid by outpatient testing, surgeries, and inpatient admissions. They use the profits from these services to cover the cost of services that they lose money on. Palliative care has to compete with a myriad other hospital services for funding. In deciding which of these services to monetarily support, hospital leaders rely on clinical research studies and publications to guide them. This recent study will help to provide needed justification for expansion of palliative care telemedicine services. Indeed, palliative medicine and telemedicine are perfect for each other.

March 8, 2024

Categories
Epidemiology Outpatient Practice

Is It Dangerous To Vaccinate Pregnant Women And Children Against COVID?

Last fall, I was hiking and birdwatching in a nature preserve in coastal North Carolina. A woman walked by talking on her cell phone loudly enough for me to overhear her conversation 50 feet away. She spoke about her outrage that children were being vaccinated against COVID and that her internet research from the Children’s Health Defense organization indicated to her that COVID was a hoax propagated by Bill Gates and that COVID vaccines cause autism. I rolled my eyes, kept my mouth shut, and went back to watching egrets.

It reminded me of another conversation that I had with one of our family medicine physicians about 15 years ago. It was October and she was pregnant. I had arranged an influenza vaccination station in the hospital physician lounge and told her about it so that she could get vaccinated. She said that she wasn’t going to get a flu shot because she believed that flu shots in pregnant women cause autism in their children. I tried to convince her otherwise but she was firm in her beliefs. That winter, when she delivered her baby, she had active influenza. Her newborn ended up in the neonatal ICU at Nationwide Children’s Hospital with an intracranial hemorrhage.

The lesson is that misinformation abounds, even among intelligent and educated people. The main defense against misinformation is scientific research. In the short-run, misinformation can persist but in the long-run, science eventually prevails. Beliefs such as the sun revolves around the earth, the earth is flat, and smoking cigarettes is beneficial to your health were all held as incontrovertible truths in the past but eventually were dispelled by science to all except the most gullible. This week, two new scientific studies were published that will help to dispel misinformation about COVID vaccines and children.

The first was a study in JAMA that looked at all newborns in Sweden and Norway between June 2021 and January 2023; in total, 196,470 infants. 48% of the infants were born of mothers who were vaccinated against COVID during pregnancy and 52% were born of unvaccinated mothers. The results are striking. The babies born from unvaccinated mothers were twice as likely to have intracranial hemorrhage compared to babies born from mothers who were vaccinated during pregnancy. In addition, compared to babies whose mothers got vaccinated, the babies of unvaccinated mothers were twice as likely to die and 50% more likely to have hypoxic encephalopathy. The benefits of maternal vaccination did not stop there. Newborns of unvaccinated mothers were also more likely to have anemia, bleeding, thombosis, lower birth weight, septicemia, seizures, heart failure, feeding problems, and necrotizing enterocolitis. This was a study that involved a huge number of subjects and made all the stronger because all children born in the two countries for a year and a half were included in the analysis.

The second study was also published in JAMA and looked at 2,959 children between ages 5-17 at 6 U.S. study sites in Texas, Arizona, Oregon, Michigan, Utah, and Washington. 25% of the children received a bivalent COVID vaccine and 75% were not vaccinated with a bivalent COVID vaccine. The results were not surprising – the unvaccinated children were more likely to get both asymptomatic COVID infections and symptomatic COVID infections compared to the vaccinated children.

These two studies will not convince all anti-vaxxers but they will hopefully loosen the hold of misinformation on some of them. For some people, beliefs are just too hard to break – there are still those among us who believe that there are bands of bigfoot roaming rural Ohio, stealing chickens and throwing rocks at passing cars. Similarly, like the woman at the North Carolina nature preserve, there are those who are ardent believers of Robert F. Kennedy, Jr. (the founder of the Children’s Health Defense organization) who publicly stated about COVID vaccines: “It is criminal medical malpractice to give a child one of these vaccines”. In 1887, Abraham Lincoln famously said “You can fool all of the people some of time; you can fool some of the people all of the time, but you can’t fool all the people all the time.” Kennedy has made millions of dollars for himself by fooling some of the people all of the time.

But physicians can now tell their pregnant patients with confidence that getting a COVID vaccination will improve their chances of having a healthy baby and improve the chances that their baby will live through its first month after birth. COVID vaccines do not provide 100% protection against the infection. But then neither do kevlar vests provide 100% protection in a mass shooting. However, wearing a kevlar vest will improve your chances of surviving and improve your chances of avoiding major injury. COVID vaccines are like wearing a kevlar vest against the virus for pregnant women and for children.

February 7, 2024

Categories
Epidemiology Outpatient Practice

Why Your Practice Needs An Outpatient Antibiotic Stewardship Program

When physicians hear the words “antibiotic stewardship”, they think of inpatient programs to control antibiotic use. However, more than 80% of antibiotics are prescribed in the outpatient setting. The Joint Commission mandates that hospitals have an inpatient antibiotic stewardship program but there is no national requirement in the outpatient setting and consequently, better stewardship of outpatient antibiotic use is essential to control multi-drug resistant bacteria.

Emergence of drug-resistant bacteria

Charles Darwin

The story of drug-resistant bacteria is the story of evolutionary biology and that story dates back more than 2 centuries ago.

It was the fall of 1827 and Charles Darwin was bored. He was in his second year of medical school at the University of Edinburgh but was neglecting his medical studies as he was more interested in studying the biology of oysters than of humans. So, his father sent him to Cambridge to study to become a county parson instead. There, he was more interested in studying entomology than religion. However, he did manage to graduate in 1831. But with no employment opportunities that interested him, he decided to sign on as a naturalist on a 5-year expedition to chart the coast of South America on the HMS Beagle. His observations of during the voyage served as the foundation for his theory of natural selection that later became the central tenet of evolutionary biology.

Alexander Fleming

Perhaps nowhere has natural selection been more easily observed than in the emergence of antibiotic resistant bacteria over the past 80 years. In 1928, Alexander Fleming discovered penicillin, purely by accident. In 1941, police constable Albert Alexander became the first person treated with penicillin when he scratched his face with a rose thorn and developed a flesh-consuming infection caused by Staph aureus. After 5 days of treatment with the new drug, his infection was under control but he then relapsed when his doctors exhausted their supply of penicillin. When penicillin was initially rolled out, it killed essentially all Staph aureus bacteria. But by 1942, penicillin-resistant Staph were identified and by 1946, 12.5% of all Staph aureus isolates were resistant to penicillin. One year later, the incidence of penicillin resistant staph had tripled even further.

Methicillin-resistant Staph aureus

To fight the rapidly emerging resistance of Staph aureus to penicillin, a new semi-synthetic penicillin derivative was created in 1959 called methicillin. It was first marketed in September 1960 but only one month later, a public health lab in London identified isolates of Staph that were resistant to the new antibiotic and these were called methicillin resistant Staph aureus, or MRSA. Thirty years ago, 2% of all Staph infections were due to MRSA. Today, in the United States, most staph infections are caused by MRSA and one-third of all healthy Americans are colonized with MRSA in their noses. To treat MRSA infections, the medical community turned to vancomycin. But in 2002, the first case of vancomycin-resistant Staph aureus was identified in a diabetic patient in Michigan. Today, vancomycin-resistant Staph aureus has replaced MRSA as the bacterial bogyman in our nation’s hospitals.

Currently in the United States, there are 2.8 million infections caused by drug-resistant infections and 35,000 deaths due to antibiotic resistance every year. There are additionally 12,800 deaths each year due to Clostridium difficile that arises as a complication of antibiotic use. Antibiotic overuse and misuse is fertilizer for antimicrobial resistance. To slow the emergence of drug-resistant pathogens, it is necessary to more judiciously prescribe antibiotics, especially in the outpatient setting.

The problem of outpatient antibiotic use

In the U.S., three are 211 million outpatient antibiotic prescriptions written every year. The CDC estimates that 72% of these are necessary but 28% are unnecessary. Even when antibiotic prescriptions are necessary, we have opportunities to improve drug selection, improve drug dosing, and shorten the duration of administration. Taking all of this into consideration, about half of all outpatient antibiotics are either unnecessary or prescribed incorrectly.

All of us who practice outpatient medicine have been guilty of antibiotic misuse at one time or another. A patient comes to the office with a viral upper respiratory infection and the doctor prescribes an antibiotic that was never needed in the first place. Maybe the doctor was not aware of clinical practice guidelines for managing upper respiratory infections. Maybe the doctor wanted to make the patient happy by prescribing an antibiotic. Maybe the doctor was afraid of complications of the URI. Maybe the doctor figured he or she could bill a higher level of service for the office visit by prescribing an antibiotic. Maybe the doctor thought that it would be faster to prescribe an antibiotic than to explain why an antibiotic was not necessary. Regardless of the reason, the next time that the patient has a cold, that patient will believe that an antibiotic is necessary and expect the physician to prescribe one. This results in a vicious cycle of antibiotic misuse.

The 4 components of outpatient antibiotic stewardship

The Centers for Disease Control has an excellent on-line resource for outpatient antibiotic stewardship. This resource identifies four key components that can be incorporated into any outpatient practice: commitment, action, tracking, and education.

Commitment

Not only must the physician be committed to appropriate antibiotic use but the entire office staff must be committed. This implies that a consistent message will be given to patients, from the nurses, from the schedulers, from the medical assistants, and from the physicians. For example, when a patient calls in with a sore throat, the nurses can set the stage for antibiotic stewardship by saying “The doctor needs to evaluate you in person to determine if an antibiotic is necessary” rather than simply calling in an antibiotic prescription. The schedulers can help by telling the patient that the office has the ability to do on-site rapid strep screens during the patient’s office visit. The medical assistants can reinforce the message by telling the patient that a negative rapid strep test means that the sore throat is not caused by a bacteria.

Ideally, each medical practice should have a leader for the practice’s antibiotic stewardship program. This could be a pharmacist, nurse or medical assistant. This individual would be responsible for ensuring that all of the office staff know their roles in antibiotic stewardship and that the office’s commitment to antibiotic stewardship is communicated to patients. A simple way of doing this is with posters in the waiting room or in the examination rooms stating the practice’s commitment. The CDC has a down-loadable poster that can be used by any medical office. A 2014 study found that inappropriate antibiotic prescriptions were reduced by 19.7% simply by hanging commitment posters in exam rooms.

Action

Incorporation of evidence-based guidelines for management of common outpatient infections can help ensure that the right antibiotic is prescribed for the right duration of time for any given bacterial infection. Guidelines can also help ensure that antibacterial antibiotics are not prescribed for viral infections. One of the challenges with use of evidence-based guidelines is that many national organizations publish their own guidelines for any given infection and these guidelines can differ depending on the decisions of different guideline writing committees and how long in the past the guidelines were written. Large medical centers can develop their own practice guidelines based on distillation of available literature. In smaller outpatient practices, it is best for all of the providers to agree on the use of one guideline or another – it can be confusing to staff and patients if different providers in the practice utilize different clinical guidelines. When possible, the power of the electronic medical record should be harnessed to prompt clinicians regarding test ordering or antibiotic prescriptions for any given infection based on the ICD-10 diagnoses.

A useful action plan is the use of the “over-the-counter prescription pad” to use for common viral infections – essentially a printed checklist of non-antibiotic recommendations by the provider for such items as acetaminophen, NSAIDs, decongestant nose sprays, guaifenesin, dextromethorphan, etc. Often, a printed paper to given to the patient that is customized to include the patient’s name, date, and diagnosis can be a powerful way to reinforce that antibiotics are not necessary and that the physician is invested in treating the patient (just not with an antibiotic).

Tracking

For hospital-employed physicians, most compensation plans incorporate some kind of quality metric into each physician’s annual bonus. In our medical center, over the years these have included metrics such as percent of patients getting mammograms or colonoscopies, percent of patients getting influenza vaccinations, and patient satisfaction scores. Antibiotic stewardship is in many ways an ideal quality metric for outpatient and ER practices. This is because appropriate antibiotic prescription is a physician behavior whereas when a patient refuses a flu shot, is a no-show for their scheduled colonoscopy, or writes a bad patient satisfaction survey, it is a patient behavior. As a result, using these latter types of metrics for physician bonuses tends to financially reward physicians who have a “desirable” patient panel as opposed to those physicians who care for a lot of uninsured, lower income, or lower education level patients. By using a physician behavior in the bonus equation, the practice can avoid penalizing physicians for patient behaviors that are beyond the physicians’ control.

The electronic medical record can be utilized to track and report antibiotic stewardship quality metrics such as use of order sets derived from the organization’s clinical practice guidelines, use of rapid strep testing in patients given antibiotics for pharyngitis, and appropriate duration of antibiotics for uncomplicated urinary tract infections.

Education

This requires both education of physicians and education of patients. Physician education can take the form of grand rounds and other CME events about antibiotic stewardship. But on a smaller scale, can include distribution of the organization’s clinical practice guidelines for common infections. Successful distribution can be a challenge, however – many hospitals that maintain a “clinical practice guideline” website on the hospital’s intranet find that physicians rarely access the website. Successful adoption of guidelines usually is most effectively done on a local basis, such as at medical staff meetings, at department meetings, or by incorporation of the guideline into the electronic medical record.

Patients need to be educated about the difference between viral and bacterial infections and why viral infections do not require an antibacterial antibiotic. They also need to be educated about the risks of antibiotics, including costs, side effects, development of drug-resistant bacteria, and C. difficile. Patient education materials can again include posters for the examination rooms but can also include text pasted into the patient’s after visit summary. Whenever possible, after visit summaries should be printed and handed to the patient at the end of their office visit rather than simply loaded onto the patient portal in the electronic medical record – few patient actually open up their patient portal after they leave the office but a piece of paper will tend to stick around until the patient actually reads it.

The Centers for Disease control has several excellent patient education handouts that can be printed as posters for the office’s exam rooms or as paper handouts to be given to patients. These are available in both English and Spanish language versions. These can be downloaded from the CDC’s website or you can click on the images below for the English language handouts.


Penicillin allergy deserves a special mention. Fully 10% of patients report having an allergy to penicillin but only 1% of the population actually has penicillin allergy when tested for IgE-mediated reactions. In other words, 9 out of 10 patients who think they have a penicillin allergy do not actually have an allergy.  One of the reasons for this is that 80% of patients who truly have a penicillin allergy lose their IgE responsiveness after 10 years. But presumption of penicillin allergy drives the use of more broad-spectrum antibiotics and the development of drug-resistant bacteria. Patients reporting penicillin allergy should be asked about the specific symptoms they had when taking penicillin in the past. When uncertainty exists, patients should undergo penicillin skin testing. In the past, this required consulting an allergist but now there are easy-to-perform penicillin allergy skin tests that can be done in the primary care office. Importantly, if the test is negative, then not only does the patient need to be informed that they are not allergic, but penicillin allergy should be removed from their electronic medical record.

The special case of dentistry

Dentists account for 10% of all outpatient antibiotic prescriptions. But dental practices generally fall outside of the purview of our nation’s hospitals. As a consequence, dental practices are largely on their own when it comes to antibiotic stewardship support. Physicians can help by participating in dental continuing education programs and by sharing effective programs and practices with local dentistry colleagues. One of the important changes over the past 20 years has been a move away from indiscriminate use of prophylactic antibiotics prior to dental procedures in patients with heart murmurs and limiting prophylactic antibiotics to only those cardiac patients that truly benefit from them. There are also CDC guidelines for when to prescribe antibiotics for common oral infections such as pulpitis, periodontitis, and pulp necrosis.

An ounce of prevention

The most effective way to reduce antibiotic misuse and development of drug-resistant pathogens is to never get infected in the first place. Keeping patients up to date with vaccinations is essential. Chief among these for bacterial infections is pneumococcal pneumonia – the new PCV20 vaccine should be given to all adults over age 65. Similarly, viral infection can mimic bacterial infections or lead to secondary bacterial infections that can result in antibiotic prescriptions. Preventing these common viral infections can thus reduce antibiotic use. All Americans should receive an annual influenza vaccine and COVID update vaccine. All people over age 60 and all pregnant women should be vaccinated against RSV.

We are fortunate to be living in an era when we have more effective vaccines for deadly diseases than ever before. Vaccine recommendations change frequently as new vaccines are developed. The CDC lists the current vaccination recommendations on their website. You can also click on the images below for the 2024 child and adult vaccine schedules.


We don’t have to lose the war…

I have watched patients die of bacterial infections that were untreatable with any known antibiotic. I have taken care of patients with such extensive drug allergies that there was only one or two antibiotics that I could use for any infection they came down with. I have taken care of patients who were admitted to our ICU with overwhelming Clostridium difficile due to taking an unnecessary antibiotic or due to taking a necessary antibiotic for longer than indicated. In all of these cases, antibiotic misuse and drug-resistant bacteria were the root causes.

The good news is that initiatives to reduce antibiotic misuse are effective. Since 2013, the CDC reports that there has been  a decrease in hospital-acquired infections caused by vancomycin-resistant enterococcal, multi-drug-resistant Pseudomonas, methicillin-resistant Staph aureus, carbapenem-resistant acinetobacter, and drug-resistant Candida. However, other outpatient-acquired drug-resistant pathogens are now on the rise including erythromycin-resistant group A Strep, drug-resistant Neisseria gonorrhoeae, and ESBL-producing Enterobacteriaceae. Outpatient stewardship efforts in our physician offices, urgent care centers, and emergency departments can and will make a difference. To view an OSU MedNet-21 webcast for more information on outpatient antibiotic stewardship, click on this link.

November 22, 2023

Categories
Outpatient Practice

The History Of Idiopathic Pulmonary Fibrosis Treatments

Next year will be the 80th anniversary of the first description of idiopathic pulmonary fibrosis (IPF). It will also mark 40 years since I graduated from medical school. I spent most of those 40 years specializing in the management of patients with IPF and there have been enormous strides forward in those 40 years. This post will look back on where we have been, where we are now, and where we are going with respect to treating IPF.

First, some definitions.

Interstitial lung diseases are characterized by the accumulation of inflammation or scar or both in the lungs. There are at least 140 different interstitial lung diseases. Pulmonary fibrosis means accumulation of scar in the lungs and many of the interstitial lung diseases can result in pulmonary fibrosis. For most of these, the cause is known, such as rheumatoid arthritis-associated pulmonary fibrosis, radiation-induced pulmonary fibrosis, and asbestosis. Idiopathic pulmonary fibrosis (IPF) is when pulmonary fibrosis occurs without any known underlying cause (“idiopathic” means no obvious cause).

Usual interstitial pneumonitis (UIP) is a pattern of findings on either a chest CT scan or a lung biopsy that is typically seen in idiopathic pulmonary fibrosis. However, the UIP pattern can also be seen in other interstitial lung diseases. For this reason, the radiologist and the pathologist generally do not diagnose idiopathic pulmonary fibrosis – it is up to the pulmonologist who is seeing the patient to diagnose idiopathic pulmonary fibrosis by taking the radiologist’s or pathologist’s finding of UIP in the context of the patient’s history, physical exam, and laboratory test results.

The historical timeline of IPF

There is no one person who discovered idiopathic pulmonary fibrosis. Instead, there has been an evolution of thought about IPF over the past century. Some of the more important points in the timeline of IPF are:

  • 1944. The first clinical description of idiopathic pulmonary fibrosis is credited to Drs. Hamman and Rich from Johns Hopkins in 1944 in their description of 4 patients with interstitial lung disease of uncertain cause. Although the term “Hamman-Rich syndrome” became used as a catch-all term for many interstitial lung diseases (including idiopathic pulmonary fibrosis), their 4 patients likely had acute interstitial pneumonitis, which is a different disease.
  • 1962. Dr. Gross suggested that there were two forms of Hamman-Rich syndrome: an acute form and a chronic form. This article laid the foundation for IPF as a distinct disease (the chronic form).
  • 1964. Dr. Scadding from the United Kingdom proposed using the term cryptogenic fibrosing alveolitis for the chronic form of Hamman-Rich syndrome. For many years, cryptogenic fibrosing alveolitis was synonymous with idiopathic pulmonary fibrosis.
  • 1969. Drs. Leibow and Carrington described 5 histologic subgroups of “chronic idiopathic interstitial pneumonia”, one of which was usual interstitial pneumonitis (UIP).
  • 1976. Researchers at the National Institutes of Health, led by Dr. Crystal, proposed that idiopathic pulmonary fibrosis initiates as inflammation in the alveoli of the lungs that later progresses to fibrosis. The basis of this proposed mechanism was the findings of increased inflammatory cells in bronchoalveolar lavage fluid obtained from bronchoscopies performed on patients with IPF.
  • 1998. Drs. Katzenstein and Myers proposed that usual interstitial pneumonitis is the lung biopsy finding that occurs in idiopathic pulmonary fibrosis. They determined that the disease is due to excessive fibrosis (scar) and that there is little inflammation.
  • 2001. Dr. Hunninghake and colleagues determined that IPF can be often be diagnosed by the finding of usual interstitial pneumonitis on the chest CT scan, allowing some patients to avoid undergoing a lung biopsy.

What causes idiopathic pulmonary fibrosis?

In 2023, idiopathic pulmonary fibrosis is less idiopathic than it was in the past. IPF can be currently thought of as an auto-fibrotic lung disease due to a combination of inherited genes and environmental factors. An “auto-immune” disease occurs when the body’s immune system turns against itself, such as in systemic lupus erythematosis. An “auto-inflammatory” disease occurs when the body’s inflammatory system turns against itself, such as in the VEXAS syndrome. An “auto-fibrotic” disease is when the body’s scarring system turns against itself. Scar results when wounds heal and as such, auto-fibrotic diseases can be thought of as disorders of uncontrolled wound healing.

There is not one single gene that is responsible for idiopathic pulmonary fibrosis but rather there are many genes that can predispose a person to develop IPF. These genes vary in terms of how strongly they predispose IPF. For example, people with abnormal telomerase genes have a very high risk for developing IPF whereas those with an abnormal MUC5B gene have an increased risk of developing IPF that is not as great as with abnormal telomerase genes. For all of these genes, environmental injury to the lungs significantly increases the chance that a person will ultimately develop IPF. The most common cause of environmental injury is tobacco smoking but respiratory viruses, work-related dust inhalation, air pollution, and chronic gastroesophageal reflux can also increase the chance that a person with an abnormal gene will develop IPF.

How do we know if a drug for IPF works?

The only way to know if a drug against any disease works is by scientific research. But some types of scientific research are more convincing than others. Here are the common categories of research that physicians look at when determining a drug’s effectiveness.

  • Case reports. These are usually publications of one or two patients who appeared to respond to some type of treatment. Case reports are the weakest evidence of a drug’s effectiveness but they can be the justification for doing additional future research about a drug.
  • Case series. These are publications of numerous patients treated with a drug. Although they can provide stronger evidence than a case reports, they are still overall fairly weak. These are often called “retrospective reviews” meaning that a physician is looking back (retrospective) over a group of patients that the physician has managed in the past.
  • Open-label clinical trial. This is when a researcher deliberately gives a group of patients a drug and tracks how they respond to it. There will generally be a specific test that the researcher performs to see if the drug has an impact, for example, by performing pulmonary function tests. When a clinical trial is “open-label”, it means that the researcher and the patients know whether or not they are getting the drug. However, this knowledge can lead to bias by either the patients or the researcher who may want to think that the drug is working, even if it is not.
  • Randomized, double-blind, placebo-controlled clinical trial. These provide the strongest evidence that a drug is effective. Patients are randomly assigned to either receive the drug or a placebo and neither the patients nor the researchers know if a particular patient got the drug or got the placebo. In order for these studies to be statistically significant, the studies have to have a large number of patients, typically in the hundreds or thousands.

There are three “phases” of clinical trials of new drugs. The FDA will grant approval if the final phase of a clinical trial shows a statistically significant benefit of the drug without severe side effects.

  • Phase 1 trials. These involve a small number of patients and are usually open-label and of short duration. The researchers are primarily interested in drug safety and side effects. Several doses of the drug will be tested in order to find the safest doses and how frequently the drug should be given.
  • Phase 2 trials. These involve a larger number of patients who are randomized to receive either the drug or a placebo. During phase 2, the researchers will determine if the drug holds the possibility of being effective and will determine the best dose of the drug to use in the next phase.
  • Phase 3 trials. These involve very large numbers of patients – IPF trials typically require more than a thousand subjects. There are usually many hospitals (study sites) involved from multiple states and often from multiple countries. Patients are randomized to receive placebo or the drug and are tested regularly to determine if the drug is effective compared to placebo. Most IPF phase 3 trials require each subject to participate for 1 – 2 years.

IPF treatment over the years

Prior to 2014, there were no drugs that were approved by the FDA to treat idiopathic pulmonary fibrosis. Therefore, physicians used drugs that were approved for other diseases that were already available on the market. This is called “off-label” use of these drugs. Over time, researchers performed clinical trials to determine if these off-label drugs were actually effective and pharmaceutical companies developed new drugs to test in clinical trials. Clinical trials are expensive to perform and most of the clinical trials involving off-label drugs were funded by federal grants from the National Institutes of Health. Clinical trials of newly created drugs are generally funded by pharmaceutical companies. There has been a steady evolution in the treatment of IPF:

  • 1970’s – The prevailing belief about the cause of IPF was abnormal inflammation resulting in alveolitis. Thus, the drugs most commonly used to treat IPF were anti-inflammatory drugs, such as the corticosteroid, prednisone. There were no clinical trials to determine the best dose or whether corticosteroids even worked at all.
  • 1980’s – After years of watching patients fail to improve with corticosteroids, physicians turned to a more powerful anti-inflammatory drug, cyclophosphamide (Cytoxan) based on case reports and retrospective case series. Cytoxan was largely used as a chemotherapy drug to treat cancer but was also being used to treat auto-immune diseases such as systemic lupus erythematosus (aka, SLE)  and granulomatosis with angiitis (aka, Wegener’s granulomatosis). A problem with Cytoxan is that it was very toxic and patients frequently developed low white blood cell counts, bladder hemorrhaging, and bladder cancer.
  • 1990’s – After years of dealing with Cytoxan’s side effects, physicians looked to a different drug that was slightly less powerful as an anti-inflammatory drug but had much fewer complications. That drug was azathioprine, or Imuran. This was often given along with the corticosteroid, prednisone. A third drug as also frequently added: N-acetylcysteine (NAC). Because NAC has very few side effects and is available over-the-counter, it was seen as being fairly innocuous and possibly beneficial due to it’s anti-oxidant properties.
  • 2000’s – A phase 3 study of azathioprine, prednisone, and NAC found that these drugs were not helpful in IPF and if anything, patients who took them did worse than patients who got the placebo. A small study suggested that gamma interferon might be beneficial and so physicians turned to the off-label use of gamma interferon that was already approved by the FDA for use in a rare condition called chronic granulomatous disease.
  • 2010’s – A phase 3 study of gamma interferon showed that it was ineffective in IPF and thus physicians stopped using it. In 2014, large phase 3 trials found that the anti-fibrotic drugs pirfenidone and nintedanib were both effective in IPF, resulting in the FDA approving their use. Presently, these are the only drugs approved for IPF in the U.S. and are considered the current standard of care.

The past 3 decades are littered with drugs that initially held promise but were shown in clinical trials to be ineffective in IPF. A list of the most prominent of these drugs is below:

Current IPF treatment

Pirfenidone and nintedanib have both been shown to slow the progression of IPF compared to placebo, however they do not stop or cure the disease. Think of them as slowing the progression of IPF from 60 miles per hour down to 30 miles per hour. The patients will still ultimately get worse but just more slowly. There has not been a head-to-head comparison of the two drugs but the available evidence suggests that both are equally effective. The choice of which drug to prescribe is generally based on the personal preference of the physician and the patient. These preferences are most commonly based on the differing side effect profiles of the two drugs: pirfenidone cause cause skin rash and sun-sensitivity, nintedanib can cause diarrhea. The drugs also differ in drug-drug interactions – for example, nintedanib interacts with anticoagulants whereas pirfenidone interacts with ciprofloxacin.

Lung transplant is the only curative treatment for IPF. In the U.S., IPF is now the most common indication for lung transplant, accounting for 37%. Not all patients with IPF are eligible for transplant, however. The decision of eligibility is made by each hospital’s transplant team and limiting factors can include active tobacco use, obesity, older age, deconditioning, and presence of other concurrent diseases. Moreover, transplant comes with it’s own risks – 15% of patients with IPF die in the first 12 months after transplant and of those who survive the first 12 months, only 67% are still alive 5 years after transplant. However, post-transplant care is improving and survival rates are expected to improve in the future.

In addition to anti-fibrotic medications and lung transplant, there are other interventions that have been shown to be useful in patients with idiopathic pulmonary fibrosis. Oxygen is effective in improving the quality of life of patients with IPF. It can reduce shortness of breath, improve ability to exercise, and facilitate travel. Pulmonary rehabilitation is also effective in improving quality of life and should be considered for all IPF patients with shortness of breath or exercise limitation. Patients with IPF are at increased risk of obstructive sleep apnea and physicians should have a low threshold for performing sleep studies and prescribing CPAP when indicated. Although treating asymptomatic patients with proton pump inhibitors is ineffective in IPF, whose with symptoms of gastroesphageal reflux should be treated in order to reduce on-going lung injury. Patients with large hiatal hernias may benefit by surgical repair if they are able to tolerate surgery. Smoking cessation is essential to stop on-going lung injury, improve quality of life, and make patients eligible for lung transplant. All patients with IPF should be vaccinated to prevent pneumococcal pneumonia, influenza, respiratory syncytial virus (RSV) and COVID. Patients with IPF are at higher risk of death from respiratory infections and even if they survive the infection, it can result in additional lung injury that can accelerate the progression of IPF. During the first 12 months of the pandemic, 5% of my outpatients with interstitial lung disease died from a COVID infection due to their greater susceptibility.

Although cure of IPF is not yet possible (other than with transplant), it appears that our current treatment approach is making a difference. A recent study from Italy compared patients with IPF over a 15-year period from 2002 to 2016. Over this time, there was an increase in life expectancy, decrease in the rate of hospitalization, and decrease in the rate of acute exacerbations. Correlated with these improved outcomes was an increase in the use of anti-fibrotic drugs (pirfenidone and nintedanib), decrease in the use of anti-inflammatory drugs (corticosteroids, cyclophosphamide, and azathioprine), and increase in the use of bronchoscopic cryobiopsies as opposed to the more invasive surgical lung biopsies.

The future of IPF treatment

Prior to the FDA approval of pirfenidone and nintedanib, most IPF clinical trials compared a promising drug to placebo. Now that pirfenidone and nintedanib are the accepted standard of care, future trials have to either compare new drugs to pirfenidone and nintedanib or have to compare new drugs to placebo in patients who are already taking pirfenidone or nintedanib. Performing clinical trials in IPF is complicated for a number of reasons:

  • The heterogeneity of IPF makes trial design difficult. Given that there are multiple predisposing genes involved in IPF and given that there are multiple environmental risks for IPF, no two patients with IPF are exactly alike and treatments that work for one patient may not work for another.
  • Mortality cannot be used as an endpoint. The current average survival of a patient with IPF is 5.5 years based on the Italian study. If researchers were to use death as the endpoint in a clinical trial, that trial would have to last for a decade or more in order to recruit a sufficient number of patients and follow them until death. This is too long of a length of time to realistically perform a clinical trial.
  • Pulmonary function tests are currently the best outcome measure for IPF clinical trials. We use change in the forced vital capacity and diffusing capacity as markers of the progression of IPF. Although this is appealing from a logical standpoint, PFT changes may not necessarily correlate with life expectancy. But for now, PFTs are the best that we have.
  • To be statistically significant, trials must include hundreds of patients. The CAPACITY and ASCEND studies that led to approval of pirfenidone enrolled 1,247 subjects. The IMPULSIS studies that led to the approval of nintedanib enrolled 1,066 subjects. To recruit this many subjects, many study sites are required – the IMPULSIS studies required 205 hospital locations in 24 countries, the CAPACITY studies required 110 hospital locations in 13 countries, and the ASCEND study required 127 hospital locations in 9 countries.  Because future trials will need to incorporate multiple treatment arms including those taking pirfenidone, those taking nintedanib, and those taking neither, the number of subjects in future trials will need to be even larger than in previous IPF trials.
  • Clinical trials are costly. The average cost to bring a new drug to market, from initial drug discovery to FDA approval is $2.3 billion. Consequently, for pharmaceutical companies to recoup their drug development costs, any new drug is expensive and IPF drugs are no exception. The retail price of pirfenidone is $16,000 per month ($2,200 per month if using coupons such as GoodRx) and the retail price of nintedanib is similar.

There are a number of new drugs currently in phase 1 and phase 2 trials and several of these hold early promise to add to our treatment options for IPF patients. Some of the questions likely to be answered in future IPF treatment research include:

  • Is combination therapy more effective than mono therapy? Currently, patients receive either pirfenidone or nintedanib but not both. We do not know if the combination of the two be better than either one alone. The same holds for any new drug that is developed – whether it should be given alone or in combination with one of the two currently approved drugs.
  • Is inhaled therapy better than oral therapy? Giving drugs to treat lung disease by inhalation is attractive – it offers the possibility of giving relatively high concentrations of the drug directly to the airways with lower concentrations in the blood. This has the potential to reduce systemic side effects while boosting the effect in the lungs.
  • What are the chemical pathways involved in fibrosis? At present, it appears that transforming growth factor-β (TGF-β) is a key player in fibrosis development. Drugs that specifically target TGF-β may be effective in slowing fibrosis. Because TGF-β is secreted as inactive form that is converted to an active form by αvβ6 integrin, this molecule is another attractive target for future treatments. We need to identify the other proteins in the body that are involved in fibrosis.
  • Are there biomarkers of IPF that would be better to use in clinical trials than changes in pulmonary function tests? In atherosclerosis, we have a great biomarker in the cholesterol level that allows us to determine if a drug is working without having to wait to see whether or not a patient develops a heart attack or stroke. Measurement of biomarkers that are involved in the chemical pathways of fibrosis would allow us to more quickly tell if a drug is working for a particular patient without having to wait months or years to see if there are changes in pulmonary function tests.
  • Can genetics direct treatment? The different genes involved in idiopathic pulmonary fibrosis affect different proteins in the body and each of these proteins has a different role in the development of fibrosis. In lung cancer, we use the genetics of a person’s cancer to choose which chemotherapy will be most effective. As we learn more about the genetics of IPF, it is likely that a person’s specific genetic make-up will help us pick the best treatment for that particular individual.
  • What is the role of gene therapy? Gene editing is in its infancy in medicine but is already showing great promise in muscular dystrophy and sickle cell anemia. As we learn more about the genes involved in IPF, we may be able to edit those genes, not only in patients with IPF but also potentially in their relatives with the hope of preventing the onset of IPF in the first place. Because IPF only affects the lungs, it is possible that only the genes of lung tissues would need to be edited, for example, by inhalational techniques.

When I first started specializing in treating IPF 35 years ago, it was my hope to see effective treatments arise during my career. Not only do we now have effective treatments but we also know which medications can actually make patients worse. For these reasons, our management of IPF is much better today than ever before. The treatment will be even better yet in the future with translational research that results in taking the word “idiopathic” out of idiopathic pulmonary fibrosis and clinical research to bring us more effective therapies for patients with IPF.

November 14, 2023