Categories
Medical Economics

American Healthcare Financing: where the money came from and where it went

This month, the Center for Medicare and Medicaid Services (CMS) released the most recent report on U.S. healthcare financing. This covers calendar year 2024 and shows us how we pay for healthcare in the United States. Additionally, CMS has projected how we will be spending our healthcare dollars over the next 8 years.

Americans spend more on healthcare than citizens of any other country. In 2024, we spent $15,474 per person on healthcare. That works out to 18.1% of the country’s entire gross domestic product! Not only is healthcare more expensive in the U.S., but it has also been increasing at a faster pace than any other country. The graph below based on data from the OECD shows expenditures on healthcare as a percentage of GDP from 1980 to 2021. United States in the green line shows that our healthcare expenditures are increasing much faster than any other developed country.

The CMS data shows that healthcare expenditures increase dramatically with age. In 2020, healthcare for those under age 18 only costed an average of $4,217 per person but for those over age 85, the average healthcare expenditures were $35,995 per person. Importantly, the most recent CMS data on age-related expenditures is from 6 years ago, in 2020. In that year, the average U.S. per capita healthcare expenditure was $12,637 and increased 22% by 2024. Based on the recent 7.2% annual healthcare cost inflation rate, we can estimate that in 2025, the cost of healthcare for Americans over age 85 was approximately $46,500 per year. This is roughly twice the amount of the average retired American’s annual Social Security benefit.

So, why is it that Americans spend so much for healthcare compared to the rest of the world? Inevitably, any discussion about U.S. healthcare finances leads to finger pointing at individual healthcare costs: drug costs, hospital charges, physician charge, nursing home costs, etc. But the reality is that we pay a lot for all of the various healthcare costs. The figure below from the recent CMS report shows how Americans spent money on healthcare in 2024.

The largest expense was for hospital care at 31% of total healthcare expenditures or $1.64 trillion. The next largest was for physician and other clinical services at 21% or $1.11 trillion. Prescription drugs accounted for 9% of healthcare expenditures and nursing home expenditures only accounted for 4% of the total. In contrast, 7% of healthcare expenditures went toward the administrative costs of insurance companies and Medicare – that was a total of $370 billion in 2024.

The types of healthcare expenditures that Americans pay for has not changed appreciably over the past 24 years. The table below shows the percent of types of healthcare expenditures on a per capita basis. There has only been a 1 – 2 percentage point change in each of these categories between 2000 and 2024. In other words, all types of healthcare services and products have increased similarly since 2000.

Private health insurance companies were the largest source of healthcare funding at 31%, followed by Medicare at 21% and Medicaid at 17%. Out of pocket expenditures accounted for 11% which works out to an average out of pocket cost per American of $1,700.

The CMS report also includes projections of healthcare expenditures through 2033. The report anticipates a per capita 4.7% to 5.2% annual increase in healthcare expenditures. As a result, in 2033, the average American’s healthcare expenditure will be $24,200. That equates to an increase to 20.3% of the nation’s gross domestic product in 2033.

CMS projects that all types of healthcare expenditures will increase with hospital care continuing to be the largest healthcare expenditure in 2033.

Not all types of healthcare expenditures are projected to increase at the same rate, however. The greatest increase between 2025 and 2033 is projected to be in home health (71% increase) and private insurance company administrative costs (69%). At the other end of the spectrum, public health is only projected to increase by 21% from 2025 to 2033. In contrast, the Congressional Budget Office projects that the consumer price index will increase by 19.8% from 2025 to 2033, indicating that all types of healthcare costs will substantially outpace the general inflation rate over the next 8 years.

One implication of these projections is that home healthcare will be a growth opportunity over the next 8 years and hospitals would be well advised to invest in home health delivery.

The other implication is that commercial health insurance company administrative cost increases will outpace increases in other healthcare expenditures and increase nearly twice as much as governmental insurance administrative costs, such as Medicare. There are several reasons why this will likely occur. With the steady growth in Medicare Advantage Plans (Medicare Part C), commercial insurance companies will increasingly assume administrative costs previously incurred by Medicare when in the past, a majority of Medicare beneficiaries were covered under traditional Medicare, rather than Medicare Part C. In addition, insurance company CEO pay has increased more than other healthcare costs with an increase of 27% between 2023 and 2024 alone. Collectively, the CEOs of the six major national health plans earned $159.4 million in total compensation in 2024.

However, this also indicates a financial vulnerability of American healthcare – dozens of individual commercial health insurance companies all have redundant administrative costs, such as employment of company-specific actuaries, CEOs, underwriters, contract analysts, and sales staff. From a macro national healthcare economic standpoint, these redundant costs add considerably to what Americans pay for healthcare and represent opportunities for policy changes that could lower future costs.

From all of the above data, it is clear that there is no simple way to reign in U.S. healthcare costs. We cannot reduce per capita healthcare expenditures by simply reducing prescription drug costs. Nor by simply reducing physician reimbursement. Nor by reducing payments to nursing homes. The problem with the cost of American healthcare is that all types of healthcare expenditures are increasing and they are all increasing faster than the general inflation rate.

But there is reason to hope. Other countries have been able to provide as good or better healthcare to their citizens for a fraction of the cost in the United States. And although healthcare expenditures as a percent of GDP are increasing in all countries, all other developed countries have been able to control the rate of increase in expenditures more effectively than the U.S. If other countries have been able to do it, we should be able to as well.

January 25, 2026

Categories
Medical Education

Are You Paying Too Much For CME Credits?

Continuing medical education (CME) is required for all physicians in order to maintain medical licensure. For example, here in Ohio, we must have 50 hours of CME credit every two years to keep our medical licenses. There are a lot of ways to get CME but the costs can vary substantially.

  • Hospital grand rounds. Many hospitals provide free grand rounds lectures for physicians on their medical staff with one grand rounds equalling one CME credit hour. But it is difficult for most physicians to block out an hour each week to attend an in-person lecture – maybe they work night shifts, maybe the grand rounds conflicts with their operating room block, or maybe they have an outpatient clinic a distance from the hospital. For any number of reasons, most physicians are unable to attend the hospital’s 8-9 AM Thursday grand rounds. It still costs the hospital money to produce the grand rounds with administrative time to maintain CME accreditation and honoraria expenses for speakers. But the hospital generally provides CME for free as a perk to physicians. Nevertheless, every dollar that the hospital spends to put on a grand rounds is a dollar that they cannot pay the physicians in salary.
  • Medical conferences. Every national medical society has an annual meeting. As a pulmonary/critical care physician, I often attended the annual CHEST (American College of Chest Physicians) and ATS (American Thoracic Society) meetings. These are usually held in convention centers at large cities once a year and last an average of about 4 days. You can get a lot of CME credit by attending lectures and symposia with the potential of getting 25 CME credit hours by attending one medical conference. But it comes with the cost of airfare, hotel stay, conference registration, food, and taxi/Uber fare. Using the 2026 CHEST conference in Phoenix as an example, airfare is about $550, hotel stay is about $1,000, conference registration is about $1,300, taxi/Uber is about $50, and food is about $300. The total cost for the conference is approximately $3,200.
  • Professional societies. Many physician professional organizations will provide free online CME to members. But you have to pay an annual membership fee to access that CME. As an example, the American Medical Association has 64 online CME credit hours for members but the annual membership fee is $420/year.
  • Professional society-sponsored. Other professional societies will sponsor online CME that can be purchased, with society members often getting a discount on the purchase price. As an example, the American College of Physicians offers up to 165 hours of online lecture recordings from its annual meeting for $1,500. East hour of recorded lecture provides one CME credit hour. This is a less-expensive alternative to attending the annual meeting in person.
  • Medical journals. Many medical journals will provide free online CME to subscribers. As an example, the New England Journal of Medicine has 300 online CME credit hours available to subscribers. An annual subscription is $190.
  • UpToDate. Since its inception in 1992, UpToDate has emerged as the main online reference for many physicians. It offers CME credit for reading “chapters” about thousands of medical conditions and medications. The subscription cost is $500 per year.
  • Webcasts. Many academic medical centers provide online webcasts or podcasts for a fee. As an example, the OSU MedNet-21 webcast provides 40 hours of CME webcasts and podcasts each year at a cost of $25 per credit hour. As a disclaimer, I was the host/moderator of OSU MedNet-21 for 23 years.

Taking these as examples, it is clear that there is a huge difference in the cost of the various ways to get CME credits. Taking Ohio’s medical licensure requirements as typical for state medical boards, a physician must get at least 25 CME credit hours per year to maintain licensure. To get those 25 CME credits, the graph below shows the cost per credit hour between the various options.

At $128 per credit hour, attending a national medical conference is the most expensive way to get CME and if the sole reason for attending is for CME purposes, it is a poor investment. However, there are many other reasons to attend national medical meetings – networking with peers, access to the latest research study results, ability to present one’s own research, and time away from clinical practice to focus purely on learning. Moreover, these meetings are usually in desirable travel destinations, allowing physicians to make mini vacations out of attending a conference. Many employers will reimburse the cost of attending one conference every year as an employment perk so the conference may not cost the physician anything directly out of pocket. However, if the employer is paying for the cost to attend a conference, that is money that is not being paid directly to the physician in salary.

Getting online CME from a professional society that the physician is a dues-paying member of is relatively inexpensive. Being a member of the American Medical Association gets you access to CME at $17 per credit hour for 25 CME credits. Most physicians belong to at least one professional society so this can be a very cost-effective way to keep up CME credits.

However, online CME courses that are sponsored by professional societies but not offered for free can be quite expensive. To get 25 credit hours of online CME through the American College of Physicians every year would cost $60 per credit hour.

Subscribing to medical journals is one of the least expensive ways to get CME. At $8 per credit hour, a subscription to the New England Journal of Medicine is a bargain.

An annual subscription to the online reference UpToDate will get you CME at $20 per credit hour. This is a particularly efficient way to get CME since most physicians who use UpToDate use it primarily to look up the current recommended approach to diagnosing and treating various conditions that their patients have. So, many physicians subscribe to UpToDate for its use as a reference and then get the CME credit as a bonus for reading that material.

Webcasts, such as OSU MedNet-21, cost about $25 per CME credit hour in order to get the 25 credit hours per year required for medical licensure. This can be a great option for physicians who like to get their continuing medical education in a lecture format, like a grand rounds, but with the advantage of watching on-demand at a time that is most convenient for the physician.

The least expensive way for most physicians to meet their state’s CME requirements is to find a hospital that provides free CME to grand round attendees. But because attending a grand rounds each week at a set time on a set day is not possible for most physicians due to conflicts with patient care, the most practical way to get inexpensive CME is by subscribing to a medical journal that offers free CME to subscribers or by becoming a member of a professional society that provides free CME to members. UpToDate is slightly more expensive but allows physicians to get CME for topics that they were going to look up and read about anyway. Webcasts are a cost-effective way to get grand rounds-type CME on-demand. Professional society sponsored online CME courses and attendance at a professional society annual meeting are the most expensive ways to get CME, although there can be other reasons why a physician might want to attend a conference other than purely for CME purposes.

January 20, 2026

Categories
Medical Education

Medical Student Scholarships Are Needed Now More Than Ever Before

Currently, 70% of graduating medical students owe money on educational loans. The average amount of these loans is $228,000 ($215,000 from medical school and $13,000 from undergraduate college). A new Federal law limits the amount of Federal loans to $50,000 per year of professional school and $200,000 total for all of undergraduate and professional school combined. The result is that most medical students are no longer able to afford medical school on just Federal student loans in combination with their personal savings. Their only options are to either take out private commercial loans or obtain scholarships.

Medical school is expensive. The average cost of tuition, fees, and insurance for an in-state resident at a public medical school is $48,000 per year. Private medical colleges are more expensive and cost an average of $68,000 per year. However, there is considerable variation between medical schools and between different years of medical school. For example, at the Ohio State University, the cost of tuition and fees for years 1 & 2 is $32,000 per year and for years 3 & 4 is $48,000 per year for Ohio residents. For non-residents, the cost at OSU for years 1 & 2 is $57,000 per year and for years 3 & 4 is $58,000 per year. Add to that the cost of books, supplies, transportation, living and personal expenses at an average of an additional $30,000 per year. This means that the average total cost to attend a 4-year public medical school as an in-state resident is $312,000. For a private medical college or an out-of-state resident at a public medical college, the average total cost is $392,000!

The result is that no medical student can pay for medical education with Federal student loans alone. Options for students are to ask their parents for financial support, to work for a few years between college and medical school, to get scholarships, or to take out private commercial loans. Nationwide, 65% of medical students have non-loan financial support, usually scholarships or grants. Increasingly, medical students take a “gap year” between college and medical school. As discussed in a previous post, 73% of medical students reported taking at least 1 year between college graduation and medical school; 48% reported taking between 1 and 2 years; 16.5% reported taking 3 to 4 years, and 8.7% took 5 or more years off. Although there are numerous reasons why medical students take gap years, 40% reported that the main reason was to earn money to pay for medical school.

Commercial student loans are often the only other option for medical students. After all, banks consider medical students good loan risks given that when they become attending physicians, they will not have difficulty getting a job and they will have a relatively high salary. However, commercial student loans come with a very high cost with annual interest rates as high as 18% (Federal graduate student loans are currently at an annual interest rate of 7.94%). These commercial loans often come with variable interest rates that start off very low but then rapidly balloon upward into double digits. The bottom line is that commercial loans in the long run come with a higher interest rate than Federal student loans. Furthermore, unlike Federal student loans, commercial loans generally do not have income-based repayment plans that can lower payments during the years of residency and fellowship. Also unlike Federal student loans, commercial loans are not eligible for PSLF (public service loan forgiveness). Because of these factors, commercial loans are the last resort for most medical students trying to finance their medical education.

With the new Federal loan limit of $200,000 per medical student, financial need-based scholarships are more important than ever before in order to cover the gap between the cost of medical education and the Federal student loan limit. To have the greatest impact, these scholarships should be need-based rather than merit-based. Let’s face it, you’ve already got to be really, really smart to get into medical school. As a result, merit-based scholarships award money to only the smartest of a bunch of very smart students. On the other hand, need-based scholarships ensure that those students who are smart enough to get into medical school have the financial ability to attend. Otherwise, these students may find the cost of medical school to be an insurmountable barrier and choose to go into a different career.

Most scholarships come from endowments into scholarship funds. These funds are designed to generate money to award scholarships indefinitely. They are therefore invested into institution investment portfolios in order to generate predictable annual returns. Thus, most scholarship funds will award 4% – 5% of the fund value each year in order to continue awards in perpetuity. Given that the new Federal student loan limit for medical students is $200,000 and that the average student loan debt for graduating students is $228,000, there is currently an average $28,000 gap ($7,000 per year for 4 years) that each student needs come up with to attend medical school. A scholarship fund that awards $7,000 per year would need to maintain a balance of between $140,000 and $175,000.

Many students take gap years to earn enough to cover the difference in the cost of medical school compared to what they can borrow in Federal loans. When a student takes a gap year between college and medical school, that student enters the physician workforce a year later than if the student had gone straight into medical school after college graduation. Most medical students now take at least one gap year and 1 out of every 12 students take five or more gap years. Medical school admission committees like students who take gap years because of the perception that these students are more mature and are more certain of their career choice.

But gap years are terrible for society. Doctors who took gap years do not retire at an older age than those who did not take a gap year. Therefore, taking a gap year results in a shorter career as a practicing physician. Shorter careers result in a smaller physician workforce and a greater shortage of physicians. For taxpayers who subsidize public medical schools, it means that those taxpayers are getting a smaller return on their investment into every medical student who takes a gap year. Gap years are also terrible for physician financial health. If taking a 3-year gap between college and medical school results in a physician working 3 fewer years over the course of their career, then that means the physician has 3 fewer years to save for retirement while paying off student loans. Taking a 3-year gap results in a 10% shorter career as a practicing physician. A medical education can be a great financial investment but only if you then work enough years in clinical practice to derive the benefit of a physician income.

I would argue that the target for an annual scholarship award should be higher than $7,000 so that students do not need to take gap years in order to pay for the cost of medical education that is not covered by Federal loans. From a societal standpoint and from a physician financial health standpoint, we should be doing everything possible to eliminate gap years, rather than encouraging them. Having an average annual scholarship award of $10,000 – $12,000 would pay for the average cost of medical education not covered by Federal student loans and also eliminate the need for most students to take gap years.

The reality is that average financial needs are just that… average. Some graduating medical students have education debt that far exceeds the $200,000 Federal student loan limit. Maybe a student had to borrow the entire amount for both undergraduate college and medical school. Maybe a student could only get into an out-of-state public medical college with high non-resident tuition. Or maybe the student could only get into a costly private medical college. Maybe the student really wants to go into family medicine, a relatively low-paying specialty, but feels pressure to go into a surgical specialty that pays several times more than family medicine in order to be able to pay off student loans. For any of these reasons, some students may need larger annual scholarship awards than others. A $10,000 annual scholarship award might completely fill the needs of one student but another might need a $100,000 annual scholarship award to have the same impact.

But for simplicity, let’s say that a scholarship fund’s annual award target is $10,000. To generate that annual award, the fund balance would need to be between $200,000 – $250,000. Most of us do not have a quarter of a million dollars to donate as a charitable contribution to create a scholarship. But there are other options.

  • Contribute to existing scholarship funds. Every medical school will have multiple scholarship funds that anyone can contribute to. Many medical schools have class funds where physicians who graduated in a given year can donate to their class scholarship fund. When selecting a scholarship fund to donate to, look at the requirements for different scholarships – some will be merit-based, some will be financial need-based, and others might be for students coming from a particular hometown or high school.
  • Utilize a donor-directed fund. In a donor-directed fund, you donate to the fund and take a charitable deduction from your Federal income tax return that year. The fund then grows tax-free until you direct the fund administrator to disperse some or all of the funds. The disbursements can be made as scholarship awards and you can dictate the application requirements, such as financial need or desire to practice in a underserved area.
  • Put it in your will. Every college of medicine has development officers who can advise you on putting a contribution to a scholarship fund in your will. If you have a trust, you may need to have your own attorney modify the trust documents to include a scholarship contribution. The advantage of this approach is that if you live a long time and need all of your money, you can spend it. But if you die earlier than you expected, the money left in your estate can be put to good use as a contribution to a scholarship fund.
  • Charitable gift annuity. With a charitable gift annuity, you make a cash or stock contribution to a charity, such as a college of medicine scholarship. The charity then pays you a guaranteed fixed percentage of that contribution every year for the rest of your life. At death, the remaining amount in the annuity goes to the charity., A typical annual percentage would be about 5% – 6% for a donor in their late 60’s increasing to about 9% for a donor over age 85. This allows the donor to have a predictable income stream if the donor lives longer than they expect while still ensuring that there is a substantial contribution to the charity.

Last year, Congress passed a law that makes it more favorable for Americans to donate to charities. By increasing the SALT (State And Local Tax) deduction limits, it has now become more advantageous for many taxpayers to itemize deductions. And when you itemize deductions, you can deduct charitable contributions such as donating to a scholarship fund. Before 2025, the most you could deduct on your Federal income tax returns for the amount you paid in property tax, state income tax, and local income tax was $10,000 if you are married filing jointly. With a standard deduction of $29,200 (married filing jointly), taxpayers would have to have $19,200 in charitable deductions combined with the $10,000 SALT deductions to even reach the amount of the standard deduction. So, most taxpayers just took the standard deduction and did not get any additional tax benefit from their $5,000, $10,000, or $15,000 donations to charity.

For 2025, the SALT limit increased to $40,000 and the standard eduction is $31,500 (married filing jointly). The result is that for many Americans, particularly those with higher incomes, it is now more advantageous to itemize deductions instead of taking the standard deduction. This means that your $5,000, $10,000, or $15,000 charitable contribution to a scholarship fund is now tax deductible whereas in 2024 it likely was not. If you are in the 32% tax bracket, then donating $1,000 to a scholarship fund in 2025 is like donating $1,320 in 2024 – you’re now giving more of your donation to charity and less to the IRS.

The vast majority of physicians went into medicine in order to make positive contributions to society by improving health. We can continue that by ensuring that qualified students are able to go into medicine without having to borrow at excessively high interest rates or take gap years. I regularly donate to my medical school alma mater’s class scholarship fund. I don’t get any special recognition, no one is going to name a building after me, and the students who get scholarship awards from our class fund will never know my name. I do it simply because it is important and for decades to come will help students who otherwise could not afford medical school.

January 14, 2026

Categories
Physician Finances

Doctors Should Not Pay Off Student Loans Early

A few years ago, I was talking to one of the young gastroenterologists at our hospital who told me about how he had listened to a financial pundit who emphasized the importance of being debt-free and therefore dedicated his finances to paying off his student loans early. He had two young children at home and his wife did not work. He was proud of his recent debt-free accomplishment – I didn’t have the heart to tell him that he had just made a big financial mistake.

Student loan debt is an enormous problem for physicians. Currently, 70% of graduating medical students have student loan debt, averaging $228,000 per physician. After medical school, physicians must complete 3 – 7 years of residency and fellowship, depending on the specific specialty. Resident income is relatively low, with first year residents averaging about $67,000 per year. Most physicians do not complete their training and enter the attending physician workforce until they are in their early 30’s. The temptation to pay off student loans early once earning an attending physician income can be very strong. But I will argue that physicians should not make extra payments on those loans in an effort to be debt-free.Instead, physicians should be debt-smart.

Let’s take my gastroenterologist colleague as an example and go through the reasons why paying off his student loans early was a mistake.

  • He is an employee of a not-for-profit hospital. I asked him about PSLF, the public service loan forgiveness program, and he said he had heard about it but didn’t know if he was eligible. PSLF was signed into law by President Bush in 2007. To be eligible, people with Federal Direct student loans have to work full-time for 10 years for a government or non-profit organization, make 120 on-time monthly payments on the loans, be on an income-driven payment plan, and submit a PSLF certification form every year. At the end of the 10-year period, the Federal government will forgive the remaining balance of the loan. Because he wasn’t aware that he qualified for PSLF, the gastroenterologist had not submitted annual PSLF certification forms to the government. The result was that his 6 years of residency and fellowship at a non-profit hospital could not be counted toward PSLF. Had he submitted those certification forms during residency and fellowship training, the government would have forgiven the remaining balance on his loans after 4 years of being an attending gastroenterologist at our university medical center (qualifying as both a state government university and a non-profit hospital). No one should never pay off student loans early if they qualify for PSLF since it reduces the amount of the loan that the Federal government will ultimately forgive.
  • His wife does not work outside of the home. Federal Direct student loans are repaid on an income-based repayment plan, meaning that the higher your annual income, the higher your monthly payments. If you are married filing jointly for Federal income taxes, then the income-driven repayment plan is based on you and your spouse’s combined incomes. If your spouse does not have an income, then your monthly student loan payments will be lower, leaving more loan principal that can be forgiven under PSLF. Since my gastroenterologist colleague’s wife did not have an income, he could have had a sizable amount of his student loans forgiven under PSLF.
  • He has two children. College education is expensive and tends to increase in cost at a rate higher than inflation. Vanguard estimates that in 18 years, a 4-year education at a state-supported public university like the Ohio State University will cost $290,000 and a private university like the University of Notre Dame will cost $860,000. The only way most parents can come up with that kind of money is to start saving early and make regular contributions to their child’s college education fund. This allows the magic of compound interest to work for them and amplify the amount of money in that education fund. In order to have $290,000 to pay for four years of a college education at a public university in 18 years, a parent would need to make an initial investment contribution of $16,000 for a child born today and then contribute $465 every month for the next 18 years with an average annual return of 8%. That works out to a total of $60,640 in contributions but compound interest will turn that into $290,000 in 18 years. The longer you delay contributing to a child’s college education fund, the less benefit you get from compound interest and consequently, the more money you have to contribute to cover the cost of college. Because the gastroenterologist prioritized paying off his student loans early, he had not yet started to contribute to his kids’ college education funds.
  • He might have been able to deduct the interest on the student loan… maybe. You can deduct up to $2,500 of annual student loan interest on your Federal income tax returns if you meet income thresholds. For a married couple filing jointly, the modified gross annual income limit is $170,000 for the full deduction and $200,000 for a partial deduction. Most gastroenterologists earn more than $200,000 a year but many primary care physicians earn considerably less than $200,000 and can qualify for the student loan interest deduction.
  • He is not adequately funding his retirement. A recent post on the website The White Coat Investor noted that 25% of physicians retire with less than $1 million in net worth. A million dollars may sound like a lot but net worth includes all of your investments plus everything you own, like your house and your cars. Even if you retire today with $1 million in investments, using a 4% per year withdrawal strategy, that only yields an annual retirement income of $40,000 per year from your investments. Add in an average Social Security benefit of $24,000 per year and you end up with a total annual retirement income of $64,000. Far too many physicians have to either accept a less expensive lifestyle in retirement or work beyond their desired retirement age because they have not saved enough during their working years. Once again, compound interest works its magic best the sooner you start to invest in your retirement account. Assuming an average annual return of 8%, investing $10,000 per year will result in $1.8 million in 35 years. Investing $20,000 per year will result in $3.7 million in 35 years. Investing $30,000 per year will result in $5.6 million in 35 years. By putting money into paying off his student loans early, the gastroenterologist did not have enough money to maximize his contributions to his 403(b) retirement plan.
  • But wait, isn’t it better to pay off the loans early so you can avoid paying all of that loan interest? Not necessarily. If y0u have an extra $10,000 at the end of the year, you are almost always better off in the long run putting that money into a 401(k) or 402(b) rather than making extra payments on a student loan. Even assuming a loan interest rate of 8% and an annual investment return also of 8%, you are better off putting the money in a 401(k) or 403(b). The reason is that those 401(k) or 403(b) contributions reduce your taxable income and thus reduce your marginal income tax rate, thus reducing the amount you have to pay the Federal government in income tax. In addition, the 401(k) or 403(b) contributions reduce your modified adjusted gross income, thus reducing your monthly student loan payments on an income-based repayment plan. Factoring in the loan interest, the investment return, today’s income tax effects, and the income tax eventually paid in retirement when taking 401(k) or 403(b) withdrawals, I calculate that the total financial benefit to putting $10,000 into a 401(k) or 403(b) instead of making early payments on a student loan to be $23,000 after 20 years in favor of the 401(k)/403(b) contributions. If you participate in PSLF, then that amount could be even greater by resulting in a larger loan balance to be forgiven at the end of 10 years.

In an ideal world, we’d all be debt-free. But education (especially medical education) costs a lot of money and that education can be a tremendous investment that can pay huge dividends in earning power. Education loans can be healthy debt if the education gets you a job with a high annual income. Education debt can also be unhealthy debt if it does not result in a job after college that more than pays for the cost of eduction loans. Doctors have a high enough income that student loan debt is almost always healthy debt. Be sure to make your full monthly repayments every month but do not pay them off too early, particularly if early repayment causes you to neglect other aspects of financial health such as:

  • Have an emergency fund with enough money to cover 3 – 6 months of living expenses.
  • Contribute to your 401(k), 403(b), 457, or SEP plan.
  • Contribute to your children’s college education plan.

On the other hand, avoid unhealthy debt, particularly early in your career. Ways to avoid unhealthy debt include:

  • Always pay your credit cards off every month to avoid high interest charges.
  • Don’t buy a more expensive car than you can really afford and then face high car loan interest rates.
  • Don’t buy a bigger house than you can afford.
  • Make an annual budget at the beginning of each year and then stick to it.
  • Be adequately insured including home, automobile, term life, health, and disability insurance (and probably an umbrella insurance policy for good measure).

Physicians spend years training for one of the hardest jobs in the world. But that training doesn’t include learning about financial health. All too often, we rely on someone’s talk show, podcast, or website to tell us how to manage our finances, including student loans. Understanding how those loans uniquely fit into one’s personal financial health is a responsibility for each of us.

January 6, 2026

Categories
Medical Economics Outpatient Practice

Telemedicine Ends For Most Americans In January 2026 (…maybe)

Until 5 years ago, telemedicine was only reimbursed for patients in rural locations where long-distance travel for patients to get to a doctor’s office was difficult. Medicare required these patients to go to a rural health facility and the telemedicine encounter with a remote physician would then be conduced with the patient physically at the rural health facility. At the beginning of the COVID pandemic, Congress expanded telemedicine in order to allow patients to continue to receive outpatient services without having to physically go to a doctor’s office. This protected patients from exposure to contagious diseases in the waiting room, protected medical staff from exposure to contagious patients, and helped conserve personal protective equipment (PPE). The expansion of telemedicine was supposed to be a temporary measure with the intention that it would go away as the pandemic receded. But it turns out that both patients and doctors like telemedicine and now the onus is on Congress to make telemedicine permanent.

The temporary telemedicine expansion was set to expire on October 1, 2025. It had been anticipated that Congress would pass legislation to extend telemedicine beyond that date but with the government shutdown, Congress did not meet to pass any new legislation. Thus, as October 1st came and went, physicians largely stopped providing telemedicine because Medicare no longer paid for it. When the government shutdown ended, Congress passed a stopgap legislation to temporarily continue telemedicine coverage by Medicare until January 30, 2026. Without new legislation, telemedicine coverage will revert to the pre-pandemic restrictions of rural-only coverage.

At the beginning of the COVID pandemic, telemedicine was hugely popular with both patients and physicians. Office staff revised their workflows with many staff able to work from home. Physicians added cameras to their computer workstations to permit video conferencing with patients. Clinic parking lots became empty. The percent of Medicare patients using telemedicine shot up with 47% of them having a telemedicine visit in the second quarter of 2020 alone. As the pandemic waned, use of telemedicine fell but even this year, about 12% of Medicare patients have a telemedicine visit in any given quarter as shown from a graph below from a November 2025 CMS report.

Race and ethnicity. CMS reports that Hispanic and Asian Americans on Medicare are most likely to currently use telemedicine whereas White and Native Americans are least likely to use telemedicine. A household pulse survey by the U.S. Census Bureau about telemedicine utilization between July 2021 to August 2022 found similar differences in race/ethnicity utilization of telemedicine in all Americans and not just those on Medicare. However, the Census Bureau’s survey also found that White Americans were significantly more likely to use video telemedicine than Hispanic, Black, or Asian Americans; the latter were more likely to use audio-only telemedicine.

Medicare versus Medicaid. According to the CMS report, patients who are dually eligible for both Medicare and Medicaid are more likely to use telemedicine than those with Medicare alone. Dual eligible patients are more likely to be poor or disabled.

Age. The CMS report found that patients’ age also influenced telemedicine utilization with Medicare patients under age 65 twice as likely to use telemedicine as those over age 65. However, most Americans under age 65 are covered by commercial health insurance rather than Medicare unless they qualify for Medicare because of disability or end-stage renal disease. Commercially-insured patients were not included in the CMS report. So the data from the graph below may reflect use of telemedicine by disabled Americans on Medicare who have mobility and transportation barriers to coming to physician offices, and not reflect age effects per se. The Census Bureau survey that included Americans with commercial insurance found that older patients were more likely to use telemedicine than younger patients, although older persons are more likely to have any kind of physician visit than younger persons so the Census Bureau data may simply reflect the higher utilization of outpatient medical care in older persons.

Gender. Throughout the pandemic and extending to the present, women on Medicare are slightly more likely to utilize telemedicine than men.

Rural versus urban. Before the pandemic, only rural Medicare patents were eligible for telemedicine visits. However, since the onset of the pandemic, telemedicine is more likely to be used by urban Medicare recipients than rural Medicare recipients. This suggests that the distance a patient must travel to get to a doctor’s office is less of a predictor of telemedicine utilization than other factors.

Reason for Medicare qualification. There are three main ways a person can qualify for Medicare benefits: age over 65, disability, or end-stage renal disease (ESRD). Those qualifying for Medicare because of disability are most likely to use telemedicine, followed by those with ESRD. This likely reflects mobility and transportation barriers faced by disabled persons and those with ESRD.

Other factors. The Census Bureau report included other demographic variables not reported in the CMS report. Specifically, the Census Bureau report found that income correlated with telemedicine utilization with lower income persons more likely to use telemedicine than higher income persons. The Census Bureau report also found that telemedicine utilization varied by a person’s type of insurance with 26.8% of persons on Medicaid, 25.5% of those on Medicare, 19.2% of those with commercial insurance, and 9.0% of uninsured having a telemedicine visit within the previous 4 weeks. It is unclear whether income and insurance type independently affect utilization or whether patients with lower income and those on Medicaid are more likely to have disability or mobility barriers to traveling to physician offices for in-person visits.

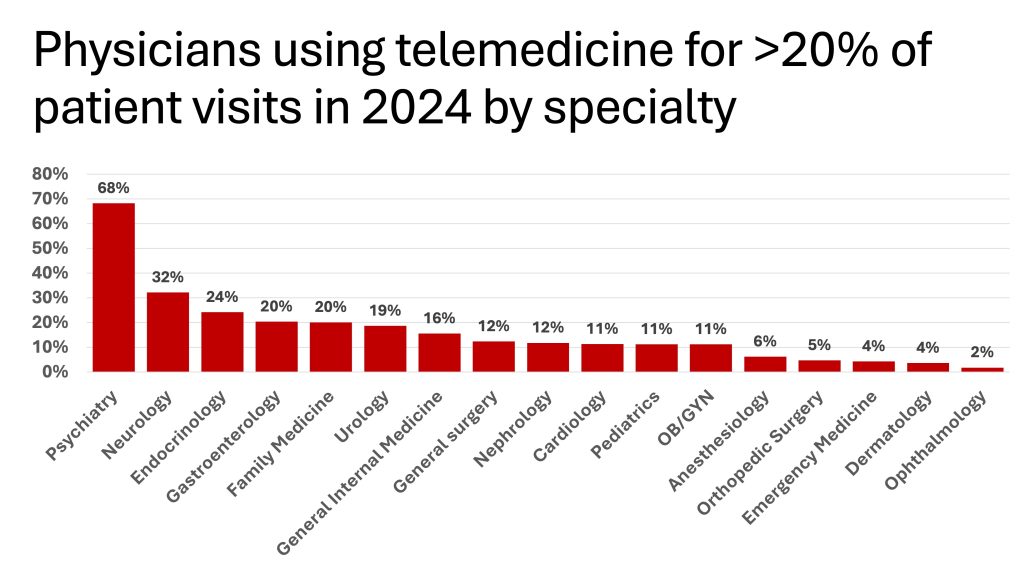
Physicians practicing specialties where a large part of the encounter is devoted to counseling use telemedicine more than those in specialties that require an in-person physical examination. A report by the American Medical association found that psychiatrists were the most likely to utilize telemedicine with 68% of psychiatrists using telemedicine for more than 20% of patient encounters. At the other extreme, only 4% of dermatologists and 2% of ophthalmologists utilize telemedicine for >20% of patient encounters, reflecting the necessity of direct physical examination of the skin and eyes to complete these encounters. Notably, 32% of neurologists use telemedicine for >20% of encounters – many neurology patients have mobility barriers that make coming to the neurologist’s office for an in-person visit difficult.

On the surface, it may seem surprising that telemedicine is utilized as much as it is in gastroenterology (20% using telemedicine for more than 20% of encounters), urology (19% using telemedicine for more than 20% of encounters), and general surgery (12% using telemedicine for more than 20% of encounters). However, these procedure-based specialties often schedule post-procedure follow-up encounters to discuss pathology results with patients and these encounters primarily consist of counseling which lends itself very well to telemedicine. In addition, many post-surgical follow-up visits are bundled into the procedure code for the initial surgery and are thus not reimbursed separately. These post-op visits are often used primarily for symptom reporting which can be done by audio telemedicine or simple examination of an incision which can be done by video telemedicine.

Early in the pandemic, both primary care physicians and specialty physicians mostly billed low-complexity encounters for telemedicine. A study from a New York City health system found that primary care physicians billed low complexity E/M codes for most of their new and return telemedicine encounters. On the other hand, as the pandemic progressed, specialty physicians billed moderate complexity E/M codes for most of their new and return telemedicine encounters. Primary care physicians rarely billed high complexity telemedicine E/M codes but specialists billed a significant number of telemedicine encounters as high complexity (albeit fewer than moderate or low complexity).

Unless Congress passes new legislation in the next month, telemedicine will no longer be covered by traditional Medicare for most Americans who are not living in rural parts of the country with access to a local rural health facility that participates in telemedicine with physicians located elsewhere. Behavioral health telemedicine will continue to be covered as this was made permanent by Congressional legislation in 2021 (of note, behavioral health patients must have an initial new patient in-person visit and an annual return in-person visit). Given the popularity of telemedicine, particularly among those with disability, mobility, and transportation limitations, it is hopeful that Congress will pass new legislation to extend traditional Medicare coverage for telemedicine or make telemedicine coverage permanent. Even if Congress fails to pass an extension, many Medicare Advantage Plans (Medicare Part C) may continue to cover telemedicine since these plans are administered by commercial insurance companies that have the freedom to cover or not cover telemedicine at their own discretion. Similarly, state-specific Medicaid plans and regular commercial health insurance plans may elect to continue telemedicine coverage for their enrollees.

This could result in a patchwork of telemedicine coverage with some patients within a medical practice being eligible for telemedicine coverage and others not eligible. Physician practices will then need to decide if they will offer telemedicine to those patients who do have insurance telemedicine benefits. This would require schedulers to determine whether or not each individual patient is eligible for telemedicine based on their specific health insurance coverage. Some practices may find that it is simpler to just not offer telemedicine to any patients rather than risk denials of bills for telemedicine encounters if a particular patient’s insurance plan no longer covers telemedicine after January 30, 2026.

Even if Congress lets Medicare telemedicine coverage expire in January 2026, patients in certain rural areas will still be eligible for telemedicine coverage based on the pre-pandemic telemedicine rules. However, these rural patients would now be required to go to a local rural health facility for their telemedicine encounter instead of having the telemedicine encounter in their own home. In addition, telemedicine could still be used for post-procedure and post-surgical follow-up encounters when those encounters are bundled into the procedure CPT code and not billed separately.

For now, physicians should not schedule telemedicine encounters for patients with traditional Medicare beyond January 30, 2026. Patients with Medicare Advantage Plans, with state-specific Medicaid plans, and with commercial health insurance policies should be scheduled on an individual basis, depending on whether or not their specific insurance carrier has agreed to continue telemedicine coverage after the telemedicine provisions for traditional Medicare expire. Uninsured patients can continue to be scheduled for telemedicine encounters since these patients pay out of pocket (or do not pay at all) and are thus not subject to Medicare telemedicine coverage rules. Post-procedure telemedicine encounters can continue to be scheduled for all patients if those encounters are bundled into the procedure CPT code, unless the specific code dictates that an in-person post-procedure visit is mandated. Neurologists and endocrinologists will be particularly impacted since these specialties have the greatest penetrance of telemedicine in their practices.

All physicians who use telemedicine should advocate for Congress to make Medicare telemedicine coverage permanent since telemedicine has become particularly beneficial for patients who are disabled and who otherwise have mobility and transportation barriers to in-person office visits.

December 27, 2025

Categories
Medical Education Physician Finances

The Covert Way That The Government Plans To Take Away Your Public Service Loan Forgiveness

In October, the U.S. Department of Education released its final rule on the Public Service Loan Forgiveness program (PSLF). The 36-page document is available online in the Federal Register. The central tenet of the rule is that it gives the Secretary of the Department of Education the ability to disqualify organizations as being eligible for PSLF if the Secretary determines that the organization has a “substantive illegal purpose”. Employees of those organizations would then no longer be able to count their years of employment toward public service loan forgiveness. This now allows the Executive Branch of the federal government to use PSLF as a weapon against hospitals and universities.

The Public Service Loan Forgiveness program was established by the U.S. federal government in 2007 under President George W. Bush as a way to help college graduates who enter a career or public service pay for college education by forgiving a portion of their student loans. The specific criteria are:

  • Be employed by a federal government, state government, local government, tribal government, or qualifying not-for-profit organization.
  • Work full-time
  • Have federal direct student loans
  • Make 120 qualifying monthly payments on the loans.

Once those criteria are met, any remaining principal and interest on the loan is forgiven. Thus far, 694,900 government workers and 305,500 workers at non-for-profit organizations have met all of the PSLF criteria and had the remainder of their student loans forgiven. The amount of loan forgiven for the average government worker was $73,100 and for the average worker at not-for-profit organizations was $82,200. Combined, 1,000,400 people have had loan balances forgiven at an average of $75,900 per person. 163,900 employees of healthcare organizations (mostly doctors and nurses) have had loans forgiven under PSLF.

Not all non-profits companies or organizations qualify as employers for PSLF purposes. Those that that are tax-exempt under Section 501(c)(3) of the Internal Revenue Code do qualify. Other non-profit organizations that devote a majority of their full-time equivalent employees to providing certain types of services also qualify. These services are: civilian service to the military, emergency management, National Guard, public safety, law enforcement, public interest law, early childhood education, public service for individuals with disabilities, public health (including physicians and nurses in a clinical setting), public education, public library, school library, school-based services, and public service for the elderly.

For physicians and nurses, this means that most public universities and most non-profit hospitals qualify as PSLF employers. Physicians can currently count their employment during residency and fellowship for PSLF purposes – there has been federal legislation proposed to no longer count residency toward the 120 loan repayment months but thus far, this legislation has not been voted on. Because most physicians do their residencies at non-profit hospitals, they can count 3-6 years of residency and fellowship toward the 10 years of required loan payments. 70% of medical students have education debt with an average of $220,000. The “One Big Beautiful Bill” now limits federal direct student loans for medical students to $200,000. Because federal direct student loan monthly payments are based on one’s income and because residents have a low income ($67,000 for a first year resident), it is very advantageous for physicians to begin paying off their direct student loans during residency since this results in a greater amount of principal that is forgiven at the end of 10 years.

The Department of Education’s new rule will permit the Secretary of the Department of Education to disqualify an organization if it engages in activities with a “substantive illegal purpose”. This is defined in the rule:

The activities indicative of a substantial illegal purpose include aiding and abetting violations of Federal immigration laws, supporting terrorism or engaging in violence for the purpose of obstructing or influencing Federal Government policy, engaging in the chemical and surgical castration or mutilation of children in violation of Federal or state law, engaging in the trafficking of children to another State for purposes of emancipation from their lawful parents in violation of Federal or State law, engaging in a pattern of aiding and abetting illegal discrimination, and engaging in a pattern of violating State laws.

The rule is proactive and goes into effect in July 2026. Organizations that are disqualified by the Secretary of the Department of Education have to wait 10 years to reapply as a PSLF qualifying organization unless the Secretary approves a corrective action plan for that organization.

The rule gives the Secretary of the Department of Education broad authority to determine what constitutes activities indicative of a substantial illegal purpose. Some of the criteria include:

“Chemical castration of children”. The rule defines chemical castration of children as:

  • The use of puberty blockers, including GnRH agonists and other interventions, to delay the onset or progression of normally timed puberty in an individual who does not identify as his or her sex.
  • The use of sex hormones, such as androgen blockers, estrogen, progesterone, or testosterone, to align an individual’s physical appearance with an identity that differs from his or her sex.
  • Child means an individual under 19 years of age.

This essentially means any hospital or other organization that provides gender-affirming care to patients under age 19. It also means that physicians employed by hospitals cannot themselves provide gender-affirming care to anyone younger than age 19. By defining a child as younger than age 19 (rather than younger than age 18), the rule means that physicians at university student health clinics are not able to prescribe or refill sex hormone medications as part of gender-affirming care, even if those medications were initiated by the student’s personal (non-university) physician.

Aiding and abetting illegal discrimination. The Trump administration has taken the position that all DEI (diversity, equity, and inclusion) activities are discriminatory and thus illegal. Many hospitals and universities have had a variety of DEI initiatives and any of these could be considered as illegal by the Secretary of Education. Because the Secretary is given sole authority for determine what constitutes substantive illegal activities, the Secretary could choose to categorize transgender athletes, race or ethnic-specific college clubs, or implicit bias training programs, or race/religion/ethnicity-based scholarships as discriminatory.

Aiding and abetting violations of Federal immigration laws. Once again, the Secretary of the Department of Education has the authority to determine if an organization has violated immigration laws. Will this include schools that enroll students who are undocumented? Will it include hospitals that provide non-emergency medical care to undocumented immigrants? Will this include universities where students protest ICE activities? Will it include homeless shelters and food pantries that do not require proof of citizenship to get in the door?

Engaging in a pattern of violating state laws. This is very broad and gives the Secretary authority to disqualify organizations for any violation of a state-specific law. The rule does state that: “Organizations will not be penalized if their actions are legal in the State in which they are operating.” However, many organizations operate in more than one state. So, if a hospital organization has a hospital in Texas where abortion is illegal and has a second hospital in New Mexico where abortion is legal, will the organization be disqualified if it performs abortions in New Mexico since it also operates a hospital in Texas? The Secretary’s interpretation of this will be final.

Engaging in violence for the purpose of obstructing or influencing Federal Government policy. The current administration has already demonstrated that it has little tolerance for behaviors opposing its policies. When Sean Charles Dunn threw a Subway sandwich at an ICE agent in August 2025, he was arrested and charged with felony assault of a Federal officer. A jury subsequently found him not guilty. But next summer, if a university student throws a sandwich at an ICE agent, there will be no jury trial – if the Secretary decides that it constitutes assault, then the university could be determined to have activities of a substantive illegal purpose. The Secretary will be the sole arbitrator of whether a student protest is violent or not.

The Department of Education states that the average amount of loan forgiveness is $75,900 per person. The new rule estimates that it will eliminate $1.616 billion in loans. This works out to 21,291 people who currently qualify for PSLF to be disqualified because they work for an organization that the Secretary of the Department of Education will disqualify. The implication is that the Department has already determined that it will be disqualifying a large number of organizations in July 2026. In looking over the definition that the new rule is using for “activities with a substantive illegal purpose”, it appears that the rule will mainly be implemented against public universities and non-profit hospitals.

The Trump administration has used similar justification for freezing Federal grants and withdrawing accreditation to effect policy and idealogical change at universities. It follows that the administration will use this new rule for disqualifying organizations for PSLF in a similar fashion. It is an extraordinarily powerful weapon, indeed. Because 70% of graduating medical students and 69% of nursing students have student loans, any hospital that becomes disqualified for PSLF will have a very, very hard time recruiting residents, attending physicians, or nurses. At particular risk are residents and nurses employed by university hospitals since any activities that happen on campus that the Secretary of the Department of Education deems to be “activities with a substantive illegal purpose” will result in those residents and nurses no longer being able to count their employment toward their 120 months of PSLF employment. Residents locked into a 3-5 year residency contract could face significant financial harm. Universities such as Harvard, Columbia, and Cornell that have already been extensively targeted by the Trump administration could be at highest risk.

When the new rule was open for public comments, many commenters questioned how the determinations would be made and what the process for appeals would be. The Department of Education responded: “The Secretary will weigh any evidence presented showing that an organization’s activities violated any laws and make a determination if those violations rise to the level of substantial illegal purpose.” In other words, whatever Secretary of the Department of Education Linda McMahon says is the final word. There is no option for an appeal. This places enormous power in the hands of a single individual who is a political appointee not elected by the general populace.

I personally agree that there are organizations that are dangerously terroristic should not qualify for PSLF, such as the Klu Klux Klan and Al-Qa’ida. But the vagueness of the new rule now allows Secretary McMahon to decide what rises to a level of substantial illegal purpose. Normally in the United States, an action is determined to be illegal by conviction in the court system. The sixth amendment of the U.S. Constitution guarantees the right of citizens to a trial by jury for non-petty crimes. But in the new Department of Education rule, there is no court, Linda McMahon alone becomes the prosecutor, judge, and jury. And there is no court of appeals.

The U.S. Department of Education’s official mission statement is “To promote student achievement and preparation for global competitiveness by fostering educational excellence and ensuring equal access.” The Department’s new rule on PSLF indicates that will use existing personnel to enforce the new rule and estimates an annual cost of $1.5 – $3 million per year. The rule represents a substantial departure from the Department’s stated mission and will now shift the Department’s mission to forcing ideologic and policy to eliminate “wokeness” and left-wing bias at our nation’s universities and hospitals. The Department of Education has now become a weapon to be used against any non-profit organization that the administration disagrees with.

Every physician, nurse, and resident who works at a university hospital or non-profit hospital should be afraid… very afraid.

December 24, 2026

Categories
Physician Retirement Planning

403b & 401k After-tax with an After-Tax Roth Conversion: A Tremendous Option For Retirement Savers

Most people are familiar with the annual contribution limits to tax-deferred retirement plans. But many employers now offer an additional way to contribute to 401(k) and 403(b) plans that allows employees to save even more of their income for retirement. And I think this is a great opportunity.

Tax-deferred retirement plans are offered by employers as a way for employees to elect to set aside a portion of their income for retirement. These contributions are tax-deferred meaning that you do not have to pay federal income tax on the contributions for the year that you contributed them to your 401(k), 403(b), or 457 plan. Instead, you pay federal income tax on the withdrawals in your retirement years.

A 401(k) plan is a tax-deferred retirement plan offered by for-profit companies. A 403(b) is a similar plan offered by non-profit companies or organizations. And a 457 is a similar plan offered by government institutions. They are all identical except that 401(k) and 403(b) plans are subject to an IRS penalty if you take withdrawals before age 59 1/2 whereas 457 plans do not have an early withdrawal penalty. A traditional IRA is similar but can consist of either tax-deferred contributions or post-tax contributions. When an IRA is created from only tax-deferred contributions (and no post-tax contributions), it is virtually identical in practice to a 401(k) or 403(b) plan.

In a Roth plan, you pay federal (and usually state) income tax on the contributions during the year that you made those contributions. In retirement, you pay no income tax on the withdrawals. Some employers will only offer tax-deferred 401(k), 403(b), or 457 plans but many will give the employee the option of either contributing to a tax-deferred 401(k), 403(b), or 457 plan or contributing to a Roth 401(k), 403(b), or 457 plan. Later in this post, I will discuss who should contribute to a tax-deferred plan and who should contribute to a Roth plan.

Each year, the federal government sets limits to the amount that an employee can contribute to a 401(k), 403(b), or 457 plan. That limit varies by the employee’s age. For 2026, contribution limits are:

  • $24,500 for employees younger than age 50
  • $32,500 for employees age 50 – 60 and older than age 63
  • $35,750 for employees age 60 – 63

In addition, the IRS allows employers to contribute to 401(k) and 403(b) plans. These employer contributions are considered separate to the employee contributions and are often offered as “matching” contributions. Combined, the employee contributions plus employer contributions cannot exceed a total of $72,000. Not all employers will offer matching contributions and those that do often limit the amount that they will match to just a few thousand dollars. As a result, very few 401(k) or 403(b) plans reach the $72,000 total contribution limit.

In 2025, many companies and organizations began to offer employees the option of contributing more money into a 401(k) or 403(b) plan by using an after-tax with an after-tax Roth conversion. Here is how it works. First, the employee must make their age-determined maximum annual contribution to their 401(k) or 403(b) plan. So, for an employee younger than age 50, that would mean $24,500 in 2026. Next, the employee contributes post-tax income into a 401(k) or 403(b) plan and immediately converts that money into a Roth 401(k) or 403(b) plan. Importantly, the conversion must be done immediately, before those after-tax contributions have a chance to earn any money on investments in the regular 401(k) or 403(b) plan; otherwise, those earnings would be subject to additional income tax when converted to the Roth 401(k) or 403(b) plan.

The maximum amount that the employee can contribute to an after-tax with an after-tax Roth conversion 2026 is $47,500. For example John Smith is 40-years-old and works for State University. He makes his maximum contribution to his regular 403(b) of $24,500. He can then make an additional $47,500 after-tax contribution with an after-tax Roth conversion. His total contribution is $24,500 + $47,500 = $72,000. On the other hand, Jane Brown is 61-years-old and also works at State University. She makes her age-adjusted maximum contribution to her regular 403(b) of $35,750. She can then make an additional $47,500 after-tax contribution with an after-tax Roth conversion. Her total contribution is $35,750 + $47,500 = $83,250.

If your employer gives you the option of either contributing to a regular tax-deferred 401(k)/403(b) plan or contributing to a Roth 401(k)/403(b) plan, you have to make a decision about whether it is better to pay income tax now or pay income tax in retirement. The guiding principle is to contribute to a Roth plan when your income tax rate is lower than it will be in retirement. Conversely, contribute to a tax-deferred plan when your income tax rate is higher than it will be in retirement.

A Roth 401(k) or 403(b) plan is better if:

  • You are younger. It is better to pay income tax on 401(k) or 403(b) contributions when your federal income tax rate is lowest. For most people, this is early in their careers when their annual income is relatively low compared to where it will be later in life. Your financial goal should be to have enough retirement savings so that your taxable income (and thus income tax rate) is higher in your retirement years than it is in your earliest working years (when your taxable income is relatively low).
  • You have a shortfall in income. Similarly, if your annual income is disrupted by being out of work for a few weeks or a few months, then your income that year will be relatively low and that will translate to having a relatively low federal income tax rate that year.
  • You anticipate a big increase in income in the future. Let’s say you are an architect and have been working as an associate for the past 10 years. The firm typically promotes architects to partner status after 15 years. Partners make double the income as associates so it would be better to pay income taxes on your 401(k) contributions now, while your income (and consequently income tax rate) is low. There are many reasons why your income could rise in the future – maybe you anticipate a big promotion in the upcoming years, maybe you own your company and plan on selling in a few years, or maybe you are working part-time and planning on increasing to full-time in a few years. Any of these situations could result in you having a lower taxable income today than you will in your retirement years.
  • You are planning a one-time big contribution to a charity this year. Maybe your congregation is planning on building a new church. Or maybe the Red Cross has an urgent appeal for donations due to a natural disaster. For whatever reason, if you anticipate making a very large contribution to charity in any given year, and if you itemize deductions on your federal income tax form, then that charitable contribution will lower your taxable income for that year. As a result, you are better off contributing to a Roth retirement account instead of a tax-deferred retirement account the year that your taxable income is low, making your income tax rate low.
  • You believe that the federal government will raise income tax rates in the future. We are currently living in an era of historically low federal income tax rates. However, income tax rates are like a pendulum that swings back and forth every few years. Americans will complain about high income taxes and vote in politicians who cut income tax rates and reduce government services. A few years later, Americans realize that the government is no longer providing the services that Americans want and then vote in politicians who raise income taxes in order to expand services. What the income tax rates will be when you are retired is anyone’s guess but if you personally think that they will be higher in your retirement, then it is better to contribute to a Roth 401(k) or 403(b) while income tax rates are still low.
  • You don’t think you will live very long. Maybe you smoke a pack of cigarettes a day, are obese, and are an anti-vaxxer. The bad news is that you probably will have a relatively short life expectancy in retirement. The good news is that you will be able to withdraw a lot of money from your retirement accounts each year in retirement because that retirement account does not need to last very long. That means that you could be in a higher income tax bracket in retirement than you were when you were working so contributing to a Roth retirement account would make sense.
  • You plan on working into your 70’s. Similar to the person who does not think they will live very long, a person who does not plan on retiring until they are in their 70’s or 80’s will have fewer years that they will have to depend on the money from their retirement accounts and this means that they will likely have a relatively high income once they start taking the money out of those accounts. It is better to contribute to a Roth account when working and have a lower taxable income and thus a lower federal income tax rate. Also keep in mind that at age 73, the IRS mandates that you take required minimum distributions from your tax-deferred IRA, 401(k), 403(b), or 457 plan and this means that your taxable income could increase dramatically at age 73 if you also have regular income from working at that age. Roth accounts are not subject to required minimum distributions at age 73.

A tax-deferred 401(k) or 403(b) plan is better if:

  • You are older. Most people have their highest earning years when they are older, generally in their 50’s. If this is the case, then you are better off making tax-deferred 401(k) or 403(b) contributions now and then taking money out of that tax-deferred 401(k) or 403(b) in retirement when you have a lower taxable income and thus a lower federal income tax rate. The additional benefit is that those tax-deferred contributions lower your taxable income in the year that you make those contributions and that means that you will have a lower effective income tax rate.
  • You anticipate a fall in your annual income in the future. Maybe you think that artificial intelligence is going to eliminate your job. Or maybe you think that the factory that you work at will be going out of business. Or maybe you just want to cut back to working part-time once you reach age 55. You’re likely going to have a higher taxable income now than you will in retirement so you are better off making tax-deferred contributions today, before the anticipated fall in your annual income.
  • You just inherited a tax-deferred IRA, 401(k), or 403(b). Usually, if you inherit a tax-deferred retirement account from a newly deceased relative, you are required to withdraw all of the money from those accounts within 5 years. Those withdrawals are considered taxable income on your federal income tax returns so they will make your total taxable income higher and thus put you in a higher federal income tax bracket with a higher effective income tax rate. You are better off contributing to your own tax-deferred 401(k) or 403(b) plan when you are taking the required distributions from the inherited tax-deferred retirement plan. This allows you to offset the increase in your taxable income from the inherited retirement account withdrawals with the decrease in your taxable income from the contributions to your own tax-deferred retirement account.
  • You just inherited an annuity (maybe). Inherited annuities (and IRAs) can be complicated. They sometimes consist of both a taxable component and a non-taxable component. They are also usually subject to the requirement that all of the money be withdrawn within 5 years of inheriting them. If an annuity (or IRA) consist of both taxable and non-taxable components, then the annuity company will likely make you withdraw the taxable component first and then withdraw the non-taxable component later. So, if half of the annuity is taxable and half is not-taxable and you withdraw the annuity over 4 years, you’ll pay income taxes on the withdrawals during years 1 & 2 and you will not pay income taxes the withdrawals during years 3 & 4. Therefore, you are better off contributing to your own tax-deferred 401(k) or 403(b) during years 1 & 2 in order to lower your total taxable income (and thus income tax rate) during those years. Importantly, anytime you inherit an annuity or IRA, make sure that you ask the insurance company or financial institution holding that annuity or IRA about whether or not all of the withdrawals are taxable and if not, which years’ withdrawals will be taxable and which years’ withdrawals will be tax-free.
  • You think you will live very long. The longer your life expectancy in retirement, the more years your retirement savings will have to last. That means that you will likely have a relatively lower taxable income every year in retirement. Lower annual income means a lower income tax rate. Therefore, you may be better off with a tax-deferred retirement account so that you pay income taxes when your income tax rate is lower than it was when you were working.
  • You believe in a zombie apocalypse. If you think that the world is going to end about the time you turn 65 or if you think that world is going to turn to bitcoin and U.S. dollars will be worthless in the future, then why pay income taxes on Roth contributions during your working years. For that matter, why contribute to a retirement account at all? The problem is that if the zombie apocalypse never happens, then you’ll be living in a homeless shelter and eating cat food once you retire if you haven’t saved.

Anyone who has enough income to contribute the maximum to their 401(k) or 403(b) plan ($24,500 in 2026 for those younger than age 50) should think about making additional after-tax contributions to a 401(k) or 403(b) with an after-tax Roth conversion. The reality is that contributing $24,500 to your retirement account every year is pretty darn good. Assuming an average annual return of 8%, working for 35 years, and then withdrawing 4% out of your retirement account every year, you would have an annual income in retirement of $196,000! But when you factor in inflation at 3% per year, that $196,000 is equal to only $69,000 in today’s dollars. If you add in the average Social Security benefit of $24,000 per person, this adds up an annual retirement income of $93,000 if you are single and $117,000 if you are married. If you are planning on doing a lot of traveling in retirement or maybe buying a second home or buying a boat in your retirement years, then $93,000 a year may not be enough.

Contributing to a 401(k) or 403(b) with an after-tax Roth conversion is always better than investing money in a regular brokerage account if you are investing for retirement. You will have to pay capital gains taxes on the earnings from those brokerage account investments whereas you won’t pay any taxes on the earnings in your Roth account. So, if you have the money to make additional retirement savings, contribute to a 401(k) or 403(b) with an after-tax Roth conversion.

Some organizations offer their employees both a 403(b) and a 457. An example would be a public university that is considered to be both a state government institution and a nonprofit institution. In this case, an employee can contribute the maximum to both the 403(b) and the 457 plans for a total of $49,000 in 2026. This would result in an annual retirement income of $138,000 in today’s dollars. Add in Social Security and that results in $162,000 if you are single and $186,000 in today’s dollars if you are married. This is a lot of money but if your taxable income is currently $350,000 a year when you are working, you will be looking at a drop in income in retirement.

For physicians, the picture gets more complicated. Most doctors are about 30-years-old when they finish a 3-year residency and about 33-years old if they do a fellowship after that. The AMA reports that 42% of physicians retire before age 65. So physicians often have fewer working years to contribute to retirement savings than other workers. Fewer years investing for retirement means fewer years for compound interest to work its magic on your investment. Factor in an average medical school loan debt of $220,000 and physicians often contribute relatively less of their income to retirement early in their careers and need to catch-up in their 40’s and 50’s. For these mid-career and late-career individuals, contributing to a 401(k) or 403(b) with an after-tax Roth conversion can make a lot of sense.

As a retired physician, I cannot overemphasize the importance of having a balanced retirement portfolio that consists of both tax-deferred retirement accounts and Roth accounts. This allows for strategic withdrawal from both types of accounts each year in order to avoid having to pay excessive income tax. That way, you can preferentially withdraw from your Roth accounts during years when you have a lot of expenses and need a lot of money (such as travel or purchasing a second home) in order to avoid having a high taxable income that year that would cause your effective income tax rate to be high. On the other hand, you can rely on just your tax-deferred accounts in years when you have fewer expenses and do not need to withdraw as much money.

If your employer offers a match to your 401(k) or 403(b). Figure out a way to at least contribute enough to maximize the match. This is free money and you should never turn down free money. So, if your employer will match up to $3,000 to your 401(k), contribute at least $3,000 yourself so that you can get the full additional $3,000 from your employer.

If your employer offers only a tax deferred 401(k), 403(b), or 457. You don’t have a choice – you can only make tax-deferred contributions up to the maximum that the IRS permits for your age. But, you can still contribute to a Roth IRA. If your income is less than $150,000 filing single or less than $236,00 married filing jointly, then you can contribute directly to a Roth IRA. If your income is higher than this, you can contribute after tax money into a traditional IRA and then immediately convert it to a Roth IRA (the so-called “backdoor” Roth IRA). In 2026, the IRA contribution limits are $7,500 for those under age 50 and $8,600 for those older than age 50.

If your employer offers you the choice of either a tax-deferred or a Roth 401(k), 403(b), or 457. In this situation, you have to decide whether you are better off with the tax-deferred option or the Roth option. Which option is best for you may change for any given year. For example, the Roth option may be better early in your career when your taxable income is lower and then the tax-deferred option may be better later in your career when your taxable income is relatively higher.

If your employer offers a 401(k) or 403(b) after-tax with an after-tax Roth conversion. First, assuming you are younger than age 50, decide whether your initial $24,500 contribution should go to a regular tax-deferred 401(k)/403(b) plan or a Roth 401(k)/403(b) plan. Then determine how much of your post-tax income you can afford to contribute to an after-tax 401(k) or 403(b) plan with an after-tax Roth conversion. Keep in mind that the maximum after tax contribution with after-tax Roth conversion is $47,500 per year.

If your employer offers both a 403(b) and a 457. This is common for public university employees. It opens up more options but also adds a layer of complexity. First, decide whether your initial contributions should be to a tax-deferred or Roth 457 (if your employer gives you a choice). Second, maximize your contributions to the 457 plan since unlike the 403(b), the 457 withdrawals are not subject to early withdrawal penalties if you retire before age 59 1/2 and need to tap into your retirement account. Third, after maximizing your 457 contributions, contribute to the 403(b) up to the age-determined maximum. Fourth, if your employer allows post tax contributions with an after tax Roth conversion, contribute up to $47,500 in post tax 403(b) contributions with an after tax Roth 403(b) conversion. This strategy allows employees younger than age 50 to put away a total of $96,500 in their retirement accounts each year. This would result in a whopping annual retirement income of $750,000, equal to $270,000 in today’s dollars.

If you have contributed the maximum to your 401(k), 403(b), or 457 plan(s). For money that you know you will be investing for retirement, first contribute to a post tax traditional IRA and then do an immediate conversion to a Roth IRA (the backdoor Roth IRA). Avoid making post tax contributions to a traditional IRA and leaving it in that traditional IRA because you will have to pay regular income tax on the earnings when you take the money out in retirement. After contributing the maximum to a backdoor Roth IRA, invest any additional money into a regular brokerage account. You will have to pay capital gains taxes on these investments but your capital gains tax rate will usually be less than your regular income tax rate.

If you have a side hustle. Many employees have self employment income in addition to their income from their employer. Maybe you are a weekend artist and sell your paintings. Maybe you are a university professor but do some outside consulting in your spare time. Or maybe you play in a band on Friday and Saturday nights. You can contribute up to 20% of your self-employed income to an SEP (simplified employee pension) with a maximum annual contribution of $72,000. SEP contributions are tax-deferred so they will decrease the adjusted gross income from your self employment income. If you have income that is on your IRS schedule C form, then you can contribute to an SEP.

A goal of financial planning is to ensure that you have enough to fund your desired lifestyle in retirement. For most of us, that means having at least as much disposable income each year in retirement as we have during our working years. Ideally, we should have a greater annual disposable income when we are retired so that we can do all the fun things we’ve dreamed of doing when we were working. We want to be able to travel, to take up new hobbies, to renovate our kitchens, to buy an RV – and all that takes money. It takes gold to make our golden years golden.

But an AARP survey found that 20% of Americans over age 50 have no retirement investment savings. These individuals will have to survive on Social Security alone in their retirement. A recent Gallup poll found that 55% of Americans do not believe that they will be financially comfortable in retirement. With the decline in the number of companies that offer traditional pensions, it is increasingly up to individuals to take responsibility for their own retirement savings. This means taking advantage of 401(k), 403(b), and 457 plans when available. The new option of after-tax contributions with after-tax Roth conversion that many employers are now offering for their 401(k) and 403(b) plans now makes it easier for Americans to save enough to fund their retirements.

December 15, 2025

Categories
Medical Education

A Mentor Should Be A Career Fiduciary

If you ask 100 business, government, military, or academic leaders what are the most important factors in successful career development, 99 of them will include identifying a good mentor. For medicine in general and for academic medicine especially, mentors are essential in order to achieve one’s maximum potential. The reality is that most of us will have many mentors that each guide us through different facets of our careers. But there is usually one person who we can look back on and say that that individual had the biggest impact on helping us realize our career success.

The best mentors are not those who you model your own behavior from, but are those who actively guide you and advocate for you. The mentor’s actions should be with the mentee’s best interest in mind and not the best interest of the mentor. In other words, the mentor should act in a fiduciary manner.

I’ve seen a lot of people who thought of themselves as mentors but were actually using those junior to them to advance their own careers rather than the junior colleagues’ careers. Here are some examples.

25 years ago, I was on a search committee for a new division director. We had narrowed the search to three finalists and invited each of them for a formal visit that included interviews with various hospital and college of medicine leaders. During my interview with him, he asked me if he was selected, whether he would be able to put his name on all manuscripts written by the members of the division. At the time, this included about 20 physicians and PhDs who collectively wrote dozens if not hundreds of papers a year. It was clear that he wanted to use the position of division director to advance his own career rather than to advance the careers of the members of the division. Needless to say, we didn’t offer him the job.

Our hospital had a quality director who always had a junior physician functioning as a quality intern. The junior physician spent months and countless hours reviewing patient charts in the analysis of a particular quality issue and then analyzing the data. The director had the junior physician prepare a PowerPoint presentation and then the director presented the findings to the medical staff leadership committee, to the Dean, and ultimately to the hospital’s Board of Trustees. In none of these presentations did the director mention the name of the physician who did all of the work and ultimately, the junior physician decided to leave academic medicine and go into a private clinical practice.

As a resident, there was an attending cardiologist whose main interest was his research laboratory. However, he was required to attend on the inpatient cardiology service 3 months a year in order to earn enough clinical income to cover his salary. He viewed the residents on the cardiology service as indentured servants whose main role was to do H&Ps, write progress notes, collect data, and put in orders. To him, residents were a tool for him to use to earn clinical income. He would show up for an hour a day to round on patients and then would go back to his research lab for the rest of the day. His belief was that residents were responsible for their own education and did little to no teaching.

As a third year medical student, I spent the month of December at a community hospital in Columbus on a general surgery rotation. At the time, students on surgery rotations were pretty low in the pecking order and were generally relegated to doing history and physical exams, collecting lab results, and performing general scut work. If a student was lucky, he or she might be granted the opportunity to stand in the corner of the operating room and watch the attending surgeon and residents perform an operation. But on the first day of December, my attending told me that he and the resident would do the H&Ps and that his nurse would collect labs and do scut. He said that I could learn the most about general surgery from being in the operating room. His goal for me was for me to scrub in on 100 surgeries during the month. He told all of the other surgeons at the hospital the plan and I held retractors during a Whipple procedure, made an incision to remove a lipoma, stood by the operating table during heart and brain surgeries, and helped suture abdominal surgery closures. I still rounded with the attending and resident every day but by the end of the month, I had been in on 100 procedures and learned more than any other month of my medical school clinical rotations.

During my first year of pulmonary/critical care fellowship, we had a weird case in our ICU of a college student who developed respiratory failure with diffuse pulmonary infiltrates and a large number of lung eosinophils found during bronchoscopy. We soon identified 3 other cases of a previously undescribed disease that we called “acute eosinophilic pneumonia”. One of my attending physicians suggested that I write it up and send it to the New England Journal of Medicine. It took me 35 drafts with the attending physician finding something to change in the first 34 but eventually we sent it in and it was accepted. The attending physician told me to put my name first on the article, rather than his name – and it launched my academic clinical career.

During the second and third years of my fellowship, I was assigned to do research with a different attending physician who specialized in the role of interleukins in lung disease. He had seen an article that suggested that some interleukins were bound to microtubules, the intracellular scaffolding that gives cells their shapes. He had me do a few experiments that supported the role of microtubules with interleukin production by a type of lung cells called alveolar macrophages. He then anointed me as the alveolar macrophage microtubule guy. That became the basis of grants I received from the National Institutes of Health and the American Lung Association – it launched my academic research career and for a few years, I was the world’s leading expert in the very obscure and esoteric field of the role of human alveolar macrophage microtubules during inflammation (mainly because no one else was doing research on it).

As a species, we physicians often have big egos that need to be constantly stroked. We have spent 15 to 20 years of training after high school competing to get into the best colleges, medical schools, residencies, and fellowships. Success in that competition usually means trying to make ourselves look better than everyone else – better test scores, better grades, more publications, more grant money, and more leadership appointments. So it is the rare physician who can step away from making themselves successful and famous to making a trainee or junior colleague successful and famous. Here are some of the specific actions that a fiduciary mentor can take for their mentees. Although these are derived from my experiences and observations as an academic physician, they can be generalized to most professions.

  • Trainees are there to be trained. Whether the trainee is a resident, a PhD post-doc, or a business intern, the reason they are there is to learn. At that level, learning is by a combination of the learning triad: (1) observation of experts performing their skills, (2) practice performing those skills themselves, and (3) didactic training. A fiduciary mentor ensures that the mentee has the opportunity to do all three. The trainee is not there to simply do the senior colleague’s work for them.
  • Nominate for or appoint to committees. A common warning given to junior professionals is to “protect your time” and this often translates to avoiding committee work. But whether the committee is at the hospital, university, corporate, or professional society level, committee membership can expose the junior professional to other organizational or national leaders and can be a vehicle for invaluable career networking.
  • The person who does the work should be the first name on the manuscript. Too many tenured professors put their name first on any research papers that come out of their lab. This is self-promotion at the cost of their junior colleagues’ reputation building.
  • Credit earned is credit due. When a medical resident is the one who figures out the perplexing rare diagnosis, the attending should publicly credit the resident with the diagnosis rather than taking credit themselves. Same with the committee chairman when a committee member performs some cost savings analysis of hospital operations. Or the research lab director when a PhD student makes some new scientific discovery.
  • Share lectureships. When the fiduciary mentor is asked to give a grand rounds or other lecture, invite the mentee to be a co-presenter for the lecture. It sends the world the message that this mentee is an expert and what they have to say has value.
  • Nominate the mentee for local and national presentations. Professional societies all have their own annual national or regional meetings. The fiduciary mentor nominates mentees to give presentations. For 25 years, I hosted the OSU MedNet continuing medical education webcast and I invited junior faculty physicians to be guest presenters in their chosen area of sub specialization in order to get their name out as emerging experts.
  • Tailor the degree of autonomy to the level of experience of the mentee. In my outpatient clinic, I had medical students, internal medicine residents, and pulmonary fellows who rotated to work with me. Each of these three types of trainees came with different degrees of experience and required different degrees of supervision. The fiduciary mentor neither sets the mentee up for failure by giving them too much autonomy nor holds them back by not giving them enough autonomy.
  • Prepare the mentee for where the field is going to be in the future, not just where it is today. Hockey legend Wayne Gretzky famously said: “I skate to where the puck is going to be, not where it has been.” This is a great lesson in any career, not just hockey. The fiduciary mentor identifies the future needs and demands in the field and prepares mentees to be the experts in those needs and demands. When our hospital was considering purchasing our first surgical robot for the operating room, our Chief of Surgery sent one of the junior general surgeons to spend a couple of weeks at a hospital that had already acquired a surgical robot. When he came back, he instantly became the go-to surgeon for robotic herniorrhaphies and cholecystectomies. Pretty soon, he was giving regional and national lectures in the then-new field of general surgery robotics.
  • Foster expertise. In the research lab, the lab director should identify new side areas of research that the research fellows and doctoral students can explore and develop in order to create new areas of research that they can claim as their own in order to launch their own careers. If a junior physician has an interest in pulmonary vasculitis and there is no current expert in pulmonary vasculitis on the faculty, then figure out how to direct all of the pulmonary vasculitis consults to that junior physician’s clinic. And be sure that the physician is assigned to give pulmonary vasculitis lectures to fellows and residents.
  • Listen. Too many people who think they are mentors ascribe to the old saying that “Children should be seen and not heard.” A mentor cannot be a fiduciary unless he/she listens to the mentee in order to determine what it is that they really want. 90% of internal medicine residents who apply to cardiology fellowships will say that they want to be teachers and researchers – that is what it takes in order to get into a cardiology fellowship. But most cardiology fellows eventually change their mind and actually go into private practice. And when they do change their mind, their future careers would benefit more by additional clinical training and business training rather than performing experiments in a research lab. The fiduciary mentor listens to what the mentee really wants rather than what the mentee thinks the mentor wants to hear.
  • A mentor’s most valuable gift is his or her time. Few things are more impactful to a mentee than one-on-one time with their mentor. Whether that be time spent teaching a laboratory technique, demonstrating a physical examination technique, or reviewing a business document prepared by the mentee, when a mentor gives their time purely for the benefit of the mentee, a true fiduciary role is established.

I carry with me a little piece of every mentor I ever had. I’ve incorporated all of their behaviors, phrases, priorities, and skills into my own persona. And I’ve passed them on to my own mentees over the course of my career. Human civilization has been built by mentors passing on knowledge and skills to their mentees and by doing so, fiduciary mentors create their true legacies.

December 1, 2025

Categories
Medical Economics

What Patients (and doctors) Need To Know About IRMAA

When I turned 65-years-old, I anticipated my healthcare insurance costs would go down as I went on Medicare. After all, I had been paying into Medicare in the way of payroll taxes for decades. But my annual health insurance premiums (medical, vision, and dental) instead went up from $5,736 per year to $6,924 per year. The reason was IRMAA, the Income-Related Monthly Adjustment Amount rule used by Medicare to calculate monthly Part B and Part D premiums.

To understand IRMAA and how it affects Medicare recipients, we first need to understand the basics of the various Medicare Parts:

  • Part A – this covers inpatient hospital care, skilled nursing facilities, hospice, and some home health services. It is free for all Americans over age 65-years-old who have paid payroll taxes for at least 10 years. However, Medicare enrollees are responsible for the cost of various co-pays and deductibles.
  • Part B – this covers outpatient care, physician charges, and medical supplies. It is partially paid for by payroll taxes but Medicare enrollees must also pay a monthly premium.
  • Part C – also called “Medicare Advantage Plans”, seniors eligible for Medicare can opt to enroll in Part C instead of Parts A & B. These plans are administered by commercial health insurance companies that contract with Medicare to cover everything that Medicare Parts A & B cover, with additional coverage for medications and often for dental care, vision care, or fitness centers. They also have deductibles and co-pays but these are typically less than the deductibles and co-pays of traditional Medicare. Think of Part C plans as a bundle of Parts A, B, and D plus a Medigap plan. The downside of these plans is that they have stricter prior authorization requirements for medical services, greater denial of coverage for services, and limit coverage to in-network physicians and hospitals.
  • Part D – these are Medicare drug plans that are administered by commercial health insurance companies. They charge monthly premiums that vary in amount based on the extent of coverage of medications. Part C Medicare Advantage Plans usually incorporate Part D coverage in the plans.
  • Medigap – this is “Medicare supplemental insurance” sold by commercial health insurance companies to help cover the deductibles and co-pays of Parts A & B. They will generally also help cover healthcare costs if hospitalization or skilled nursing facility stays exceed the limit of days covered by Medicare. They can also cover foreign healthcare costs when traveling outside of the U.S. since these costs are not covered by Medicare Parts A & B.

Medicare premiums are complex. Part A is free and has no premiums associated with it but it does come with an annual $1,736 deductible for inpatient hospital care for 2026. Part B has a base monthly premium of $202.90 and has an annual deductible of $283. Part D plan premiums vary among the various commercial insurance companies that offer these plans with each of these plans providing different degrees of coverage for specific medications and different co-pays for medications. Part D plan monthly premiums range from $0 to $123.40 with annual deductibles ranging from $0 to $615. Medigap plan monthly premiums vary among the commercial insurance companies sponsoring Medigap policies and range from $36 to $798 based on age, gender, and health status.

But the base premiums for Medicare Part B and Part D only apply to Medicare enrollees with low annual incomes. The cost of the premiums goes up as enrollee income increases and these additional costs are the Income-Related Monthly Adjustment Amount, or IRMAA. Medicare uses the “modified adjusted gross income” calculated from federal income tax returns to determine the amount of IRMAA. The modified adjusted gross income is calculated by:

  • First, determine your total annal taxable income, found on line 9 of the 1040 income tax form.
  • Next, subtract all of your annual adjustments (deductibles), found on line 10 of the 1040 income tax form.
  • The result is your adjusted gross income, found on line 11 of the 1040 income tax form.
  • Next, calculate the modified adjusted gross income by adding back amounts of certain types of deductions, non-taxable income, and tax credits including:
    • Child tax credit
    • Lifetime learning tax credit
    • American opportunity tax credit
    • Student loan interest deduction
    • Employer-provided adoption benefits
    • Foreign earned income
    • Foreign housing deduction
    • Tax-exempt interest income
    • Non-taxable Social Security benefits
    • IRA contribution deduction
    • U.S. Savings Bond interest

The modified adjusted gross income (MAGI) does not appear on the IRS 1040 income tax form and has to be calculated separately. However, each year, Social Security will calculate your modified adjusted gross income for you, based on your income tax returns from two years previously. Seniors get a letter from Social Security in late November each year notifying them of their modified adjusted gross income. So, letters were sent out this week reporting the 2024 modified adjusted gross income and from that determining the 2026 IRMAA amounts for every Medicare enrollee. The tables below show how IRMA affects monthly premiums for Medicare Part B and Part D.

Single, Head of Household, or Qualifying Surviving Spouse:

2024 MAGI2026 monthly Part B IRMAA2026 monthly Part B premium2026 monthly Part D IRMAA
< $109,000$0$202.90$0
$109,000 – $137,000$81.20$284.10$14.50
$137,000 – $171,000$202.90$405.80$37.50
$171,000 – $205,000$324.60$527.50$60.40
$205,000 – $500,000$446.30$649.20$83.30
> $500,000$487.00$689.90$91.00

Married filing jointly:

2024 MAGI2026 monthly Part B IRMAA2026 monthly Part B premium2026 monthly Part D IRMAA
< $218,000$0$202.90$0
$218,000 – $274,000$81.20$284.10$14.50
$274,000 – $342,000$202.90$405.80$37.50
$342,000 – $410,000$324.60$527.50$60.40
$410,000 – $750,000$446.30$649.20$83.30
> $750,000$487.00$689.90$91.00

Married filing separately:

2024 MAGI2026 monthly Part B IRMAA2026 monthly Part B premium2026 monthly Part D IRMAA
< $109,000$0$202.90$0
$109,000 – $391,000$446.30$649.20$83.30
> $391,000$487.00$689.90$91.00

Because the Medicare Part D premiums vary depending on which Part D plan each Medicare enrollee choses, the total monthly Part D premium will be the base price of the specific Part D plan plus the amount of the Part D IRMAA. Because Medicare Advantage Plans include drug coverage, Medicare recipients who elect to enroll in Medicare Part C will also pay the Part D IRMAA amounts.

IRMAA is not paid to the various commercial insurance companies that sponsor Part D and Part C plans, instead, IRMAA is paid directly to Medicare, along with the usual monthly Medicare Part B premium.

The total amount that any given Medicare enrollee pays for healthcare insurance per year will thus vary based on their annual income, whether or not they purchase a Medigap plan coupled with traditional Medicare, whether they opt for a Part C plan instead of traditional Medicare, and whether they opt for a Part D plan. The least amount paid would be for an individual with a modified adjusted gross income of less than $109,000 who chooses a $0 monthly premium Part D plan and no Medigap plan who would pay $2,435 per year. The highest amount would be for an individual with a modified adjusted gross income of more than $500,000 who opts for the most expensive Part D plan plus the most expensive Medigap plan who would pay $20,428 per year.

Approximately 18% of Medicare enrollees also receive Medicaid and Medicaid will cover some or all of the costs of Part B premiums, Medicare co-pays, Medicare deductibles, and medications. Other government programs that help low-income individuals pay for Medicare premiums, co-pays, deductibles, and medications include the Supplemental Security Income program, Medicare Savings Programs, and the Extra Help program.

Healthcare costs in the United States are the highest in the world and those costs increase as Americans get older. CMS estimates that the total annual cost of healthcare for Americans over age 65-years-old was $22,356 per person in 2020. Because of inflation, those costs have increased to approximately $28,000 today. Even with the IRMAA increases to Medicare premiums, American seniors pay less for their healthcare than they actually spend for health insurance, deductibles, and co-pays after age 65 – all because they are supplemented by workers who are currently paying payroll taxes today.

The additional monthly IRMAA costs that are added to monthly Medicare Part B and Part D premiums often come at a surprise to retirees. For a married couple, this can be many thousands of dollars a year that they had not budgeted to spend in their retirement. As physicians, it is important that we understand IRMAA and educate our patients about its costs before our patients retire in order to avoid unexpected health insurance bills that could jeopardize their retirement plans.

November 24, 2025

Categories
My Strangest Cases

“They’re not dead until you read the sports page”

It was autumn of 1983 and I was a senior medical student doing a rotation with a general internist in private practice at one of the community hospitals in Columbus, Ohio. Dr. Bob Murnane epitomized the old school internist. His office was across the street from the hospital – about 100 feet from the hospital entrance. He admitted his own patients and made hospital rounds early in the morning before his outpatient appointments started at 9:00 AM. He finished up his day with late afternoon rounds on his inpatients.

He was regarded as one of the top internists in the city and consequently, his practice included a who’s who of Columbus citizenry: priests and politicians; celebrities and socialites. But he took care of anyone and everyone, whether rich or poor, famous or not. He took in 2 medical students per month and was one of the most popular elective rotations for the 4th years students at the Ohio State University. What made him such a great teacher was not just his breadth of knowledge, but his wisdom about the practice of medicine and about people in general.

One morning, the other medical student, George, and I arrived at his office at 7:30. Dr. Murnane’s nurse told us that one of his inpatients just had a cardiac arrest and Dr. Murnane had left word for us to come over to the hospital right away. We hurried across the street and ran up the stairs to the nursing unit, expecting a crowd of doctors, nurses, and respiratory therapists at her room doing cardiopulmonary resuscitation.

Instead, the door was closed and the hallway was silent. We knocked on the door and went in. The patient was lying motionless in bed and looking, well… pretty much dead. Dr. Murnane was sitting in a chair at the foot of the bed, reading the sports section of the local newspaper. Without putting the paper down, he said “Come on in boys, and have a seat”. So, George and I sat down and waited. For five minutes, the room was silent except for the rustle of newspaper pages being turned. Finally, Dr. Murnane folded the paper, set it down, and went to the bedside. He looked at his patient and felt for her carotid pulse. After about 30 seconds, he said “OK, now she’s dead”. George and I just looked at each other, with no clue as to what was going on.

After calling the family, entering a death note into the patient’s chart, and filling out her death certificate, Dr. Murnane explained. A few years earlier, one of his inpatients had a cardiac arrest and underwent CPR. Despite chest compressions, Ambu bag ventilation, and multiple doses of epinephrine, the patient never regained a pulse, even though there was weak electrical activity of the heart on the cardiac monitor. In medicine, this is called pulseless electrical activity and implies death. After several minutes of CPR and no pulse, the patient was pronounced dead, his family was notified of his death, he was covered with a sheet, and then transported to the morgue. A half hour later, the morgue attendant got the shock of his life when the patient pulled the sheet off his face, sat up, and asked what was going on. Dr. Murnane had to call the family back and tell them that there was a mistake and the patient was not actually dead.

What had happened was that the respiratory therapist had been a bit overzealous with Ambu bag ventilation (aka, bag-mask ventilation) during CPR. In the chaos and excitement of the cardiac resuscitation efforts, the therapist had been squeezing the Ambu bag too rapidly, putting too much air in the patient’s lungs too quickly. When this happens, a condition called “breath stacking” can occur where there is not enough time for the lungs to exhale one breath before the next breath is given. The lungs get a little more inflated with each breath until the lungs are hyperinflated, increasing the air pressure inside the chest. If that pressure gets too high, venous blood cannot get into the chest, so when the heart beats, there is no blood for it to pump. This can result in the heart having electrical activity but there is no palpable pulse in the peripheral arteries. This phenomenon is more likely to occur in patients with emphysema or severe asthma, whose lungs are already hyperinflated due to air trapping to begin with. The treatment for breath stacking is to continue doing chest compressions but not deliver any breaths by the Ambu bag for 30 seconds or so to allow the lungs to fully deflate and thus to allow for venous blood return to the chest and to the heart.

Ever since his presumably dead patient woke up in the morgue, Dr. Murnane always waited for a period of time after CPR efforts stopped before pronouncing a patient dead. At the end of CPR, he would check to confirm the absence of a pulse and of respirations. He would then sit down and read the sports page of the newspaper and when he had finished reading the sports section, if the patient still had no pulse or respirations, then he would pronounce that patient dead.

At the time, it seemed like another quirky Murnane-ism. But four years later, I gained a whole new appreciation for reading the sports page. I had finished my internal medicine residency and was in my first year of pulmonary and critical care medicine fellowship. At the time, our fellowship program only took one new fellow per year. The first year of fellowship was all clinical inpatient rotations and the second and third years were all research. Since I was the only clinical fellow, I would make rounds in the medical intensive care unit in the mornings and then see pulmonary consults in the afternoons.

One day, we had a patient in the MICU who had a COPD exacerbation with respiratory failure. He was intubated and on a mechanical ventilator. That afternoon, he got progressively hypotensive and bradycardic, eventually resulting in a cardiac arrest. The senior resident in the MICU ran the cardiopulmonary resuscitation efforts and called the critical care attending. After 15 minutes with no pulse, the attending physician pronounced the patient dead. The family had been holding vigil in the MICU waiting room and was brought to the patient’s bedside and told of his death. The attending physician stepped out to allow the family some time. A few minutes later, there were shouts of “Praise the Lord! Praise the Lord!” from the patient’s room. The nurses ran in to see what was going on and found the patient sitting up, wide eyed and with his mouth open. One of the family members had a camera and took the patient’s picture at that moment. A couple of weeks later, that photo was on the cover of one of the supermarket tabloids (I believe it was the National Enquirer) with the caption: “Man returns from the dead at Ohio State University”. The article included the attending physician’s name. The physician then had to change to an unlisted phone number because he got calls all day and all night from people who wanted him to resurrect their dead relatives back to life. For my part, I was just happy that I was elsewhere in the hospital seeing pulmonary consults and not in the MICU that afternoon.

In the four decades after watching Dr. Murnane read the sports page with his dead patient, I’ve participated in hundreds of cardiopulmonary resuscitation efforts. I would always pause ventilation breaths for about 30 seconds when patients were in pulseless electrical activity. I would also always wait a few minutes and re-check for a pulse and respirations after CPR had concluded before notifying family members of their loved one’s death. It took up a little bit of extra time but I never had a patient return from the dead.

October 14, 2025